Related Experiment Video
Updated: Jul 2, 2025


5/6 Nephrectomy Using Sharp Bipolectomy Via Midline Laparotomy in Rats
Published on: April 4, 2025
A basic solution for a complex problem: does treatment of metabolic acidosis slow CKD progression?
Kevin Bodker1, Natalie Freidin1, Nayan Arora2
1Medical University of South Carolina.

Purpose Of This Review:
Metabolic acidosis is frequently encountered in patients with chronic kidney disease (CKD), with increasing prevalence as kidney function worsens. Treating electrolyte disturbances is the sine qua non of Nephrologists, and alkali therapy to normalize serum bicarbonate levels and slow progression of kidney disease has been embedded in clinical practice guidelines for decades on the basis of animal models and controversial clinical trials. This review will critically appraise the literature base for this recommendation and determine whether the available evidence supports this common practice, which is a timely endeavor considering the impending demotion of metabolic acidosis treatment from recommendation to practice point in forthcoming KDIGO guidelines.
Recent Findings:
Earlier, open-label, studies supporting the utility of sodium bicarbonate therapy to slow progression of chronic kidney disease have been challenged by more recent, blinded, studies failing to show benefit on CKD progression. This was further demonstrated in the absence of concomitant sodium administration with the hydrochloric acid binder veverimer, which failed to demonstrate benefit on renal death, end stage kidney disease or 40% reduction in estimated glomerular filtration rate in a large multicenter trial.
Summary:
The current body of literature does not support the routine treatment of metabolic acidosis in patients with CKD and the authors agree with the forthcoming KDIGO guidelines to de-emphasize this common practice.
More Related Videos


Related Concept Videos
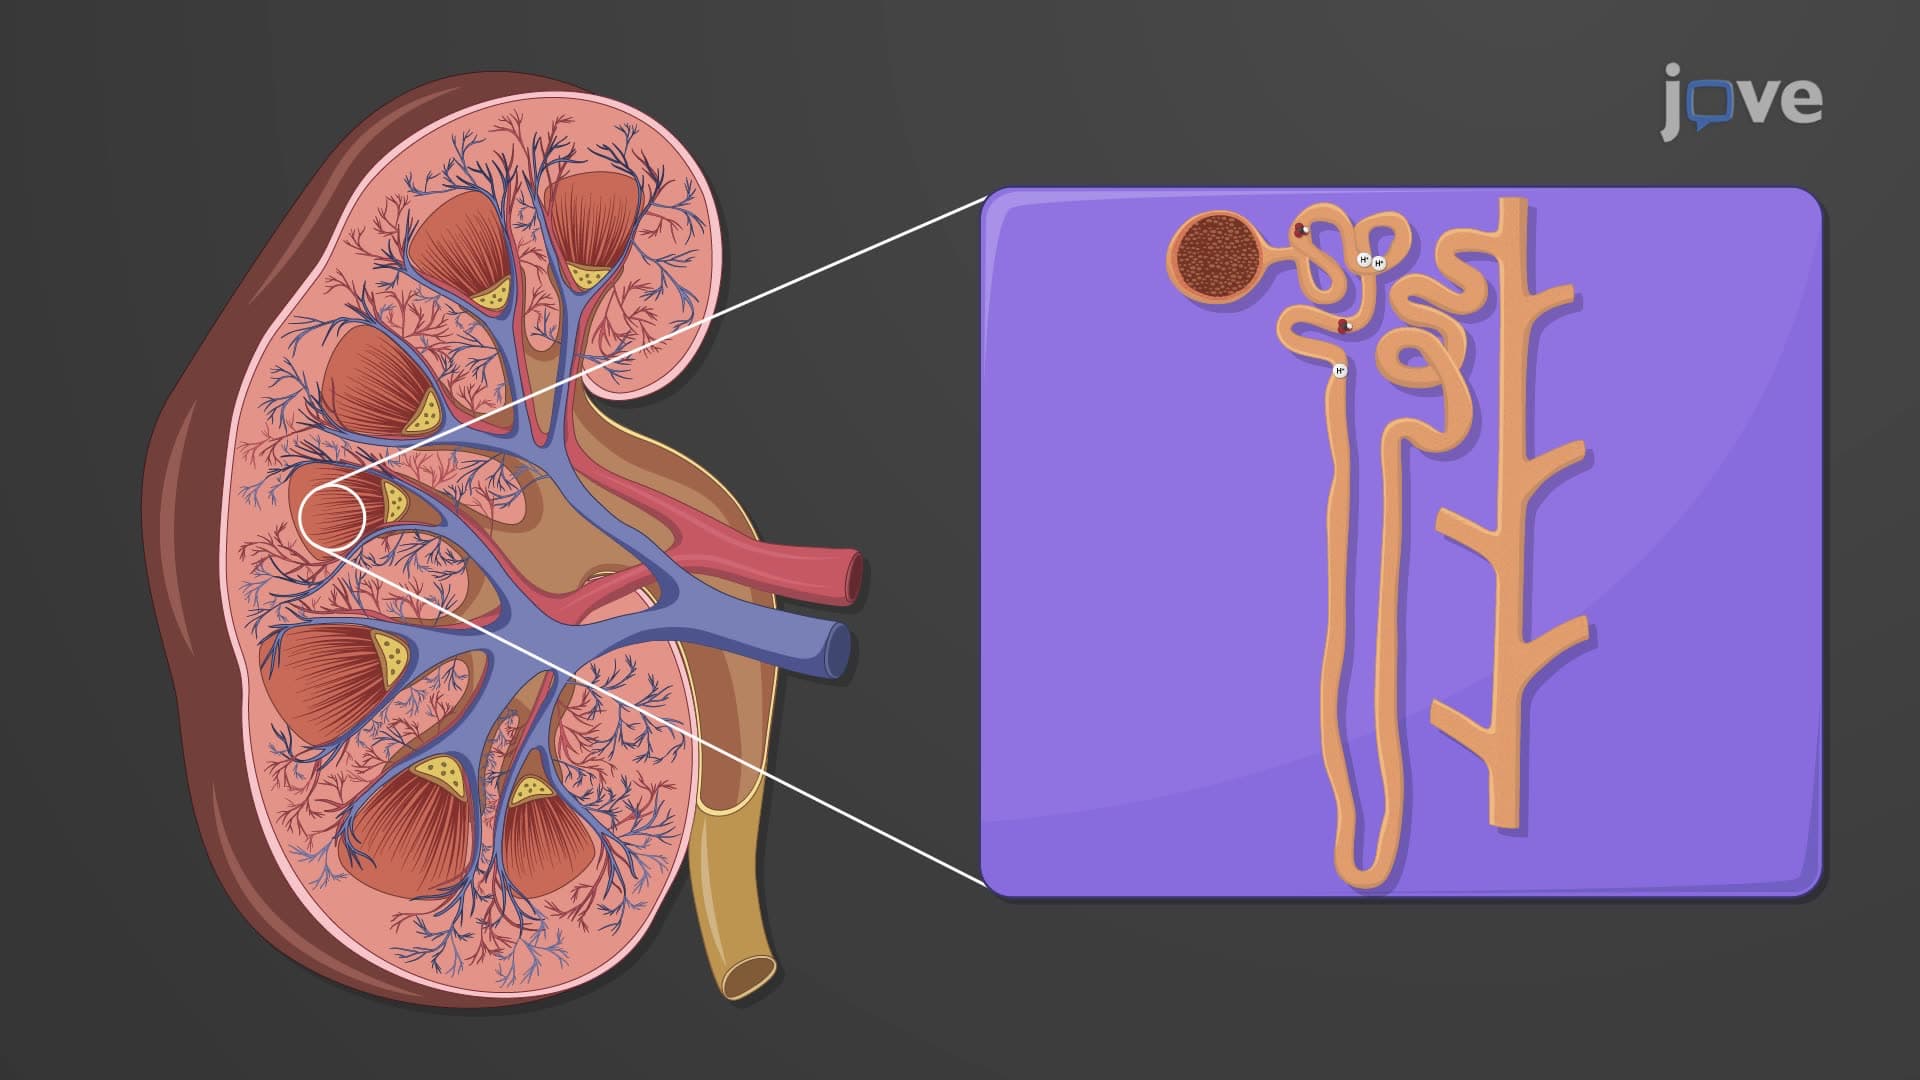 01:29
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System