Related Experiment Video
Updated: Jul 1, 2025

Intraductal Delivery to the Rabbit Mammary Gland
Published on: March 9, 2017
Breast Milk Excretion of Dinalbuphine Sebacate Injection Administered After Cesarean Section
Sung-Ling Tang1,2, Kai-Yi Wang3, Wen-Kai Hsiao3
1Department of Pharmacy Practice, Tri-Service General Hospital, Taipei, Taiwan.

Ensuring the safety of analgesics during lactation is crucial for women of childbearing potential. Available data regarding the transfer of nalbuphine for postoperative acute pain via breast milk are limited to the postmarketing experience. This lactation study aimed to assess nalbuphine and dinalbuphine sebacate concentrations in breast milk from lactating women with postoperative pain treated with dinalbuphine sebacate extended-release injection (150 mg dinalbuphine sebacate/2 mL Naldebain). Breast milk was collected throughout the 5-day posthospitalization interval from 20 mothers injected with one dose of extended-release dinalbuphine sebacate intramuscularly. Maternal safety was assessed during the study period. Nalbuphine was detectable in 71% of milk samples collected from all mothers, whereas dinalbuphine sebacate was undetectable or below the quantitation limit (0.1 ng/mL). The mean nalbuphine concentration in milk was approximately 10.55 ng/mL, with the peak concentration reaching up to 12.7 ng/mL. The mean relative infant dose was 0.39% (coefficient of variation, 65%). The mean pain intensity at rest was reduced to mild pain from Day 2 morning to discharge. Overall, the maternal safety profile was tolerable. The breast milk of women who receive one dose of dinalbuphine sebacate injection postpartum contains low nalbuphine concentration. In addition, dinalbuphine sebacate injection potentially reduces maternal pain intensity during the first postpartum week and offers low toxicity risk among breastfed infants.
Ensuring the safety of analgesics during lactation is crucial for women of childbearing potential. Available data regarding the transfer of nalbuphine for postoperative acute pain via breast milk are limited to the postmarketing experience. This lactation study aimed to assess nalbuphine and dinalbuphine sebacate concentrations in breast milk from lactating women with postoperative pain treated with dinalbuphine sebacate extended-release injection (150 mg dinalbuphine sebacate/2 mL Naldebain). Breast milk was collected throughout the 5-day posthospitalization interval from 20 mothers injected with one dose of extended-release dinalbuphine sebacate intramuscularly. Maternal safety was assessed during the study period. Nalbuphine was detectable in 71% of milk samples collected from all mothers, whereas dinalbuphine sebacate was undetectable or below the quantitation limit (0.1 ng/mL). The mean nalbuphine concentration in milk was approximately 10.55 ng/mL, with the peak concentration reaching up to 12.7 ng/mL. The mean relative infant dose was 0.39% (coefficient of variation, 65%). The mean pain intensity at rest was reduced to mild pain from Day 2 morning to discharge. Overall, the maternal safety profile was tolerable. The breast milk of women who receive one dose of dinalbuphine sebacate injection postpartum contains low nalbuphine concentration. In addition, dinalbuphine sebacate injection potentially reduces maternal pain intensity during the first postpartum week and offers low toxicity risk among breastfed infants.
More Related Videos

Related Concept Videos
 01:22
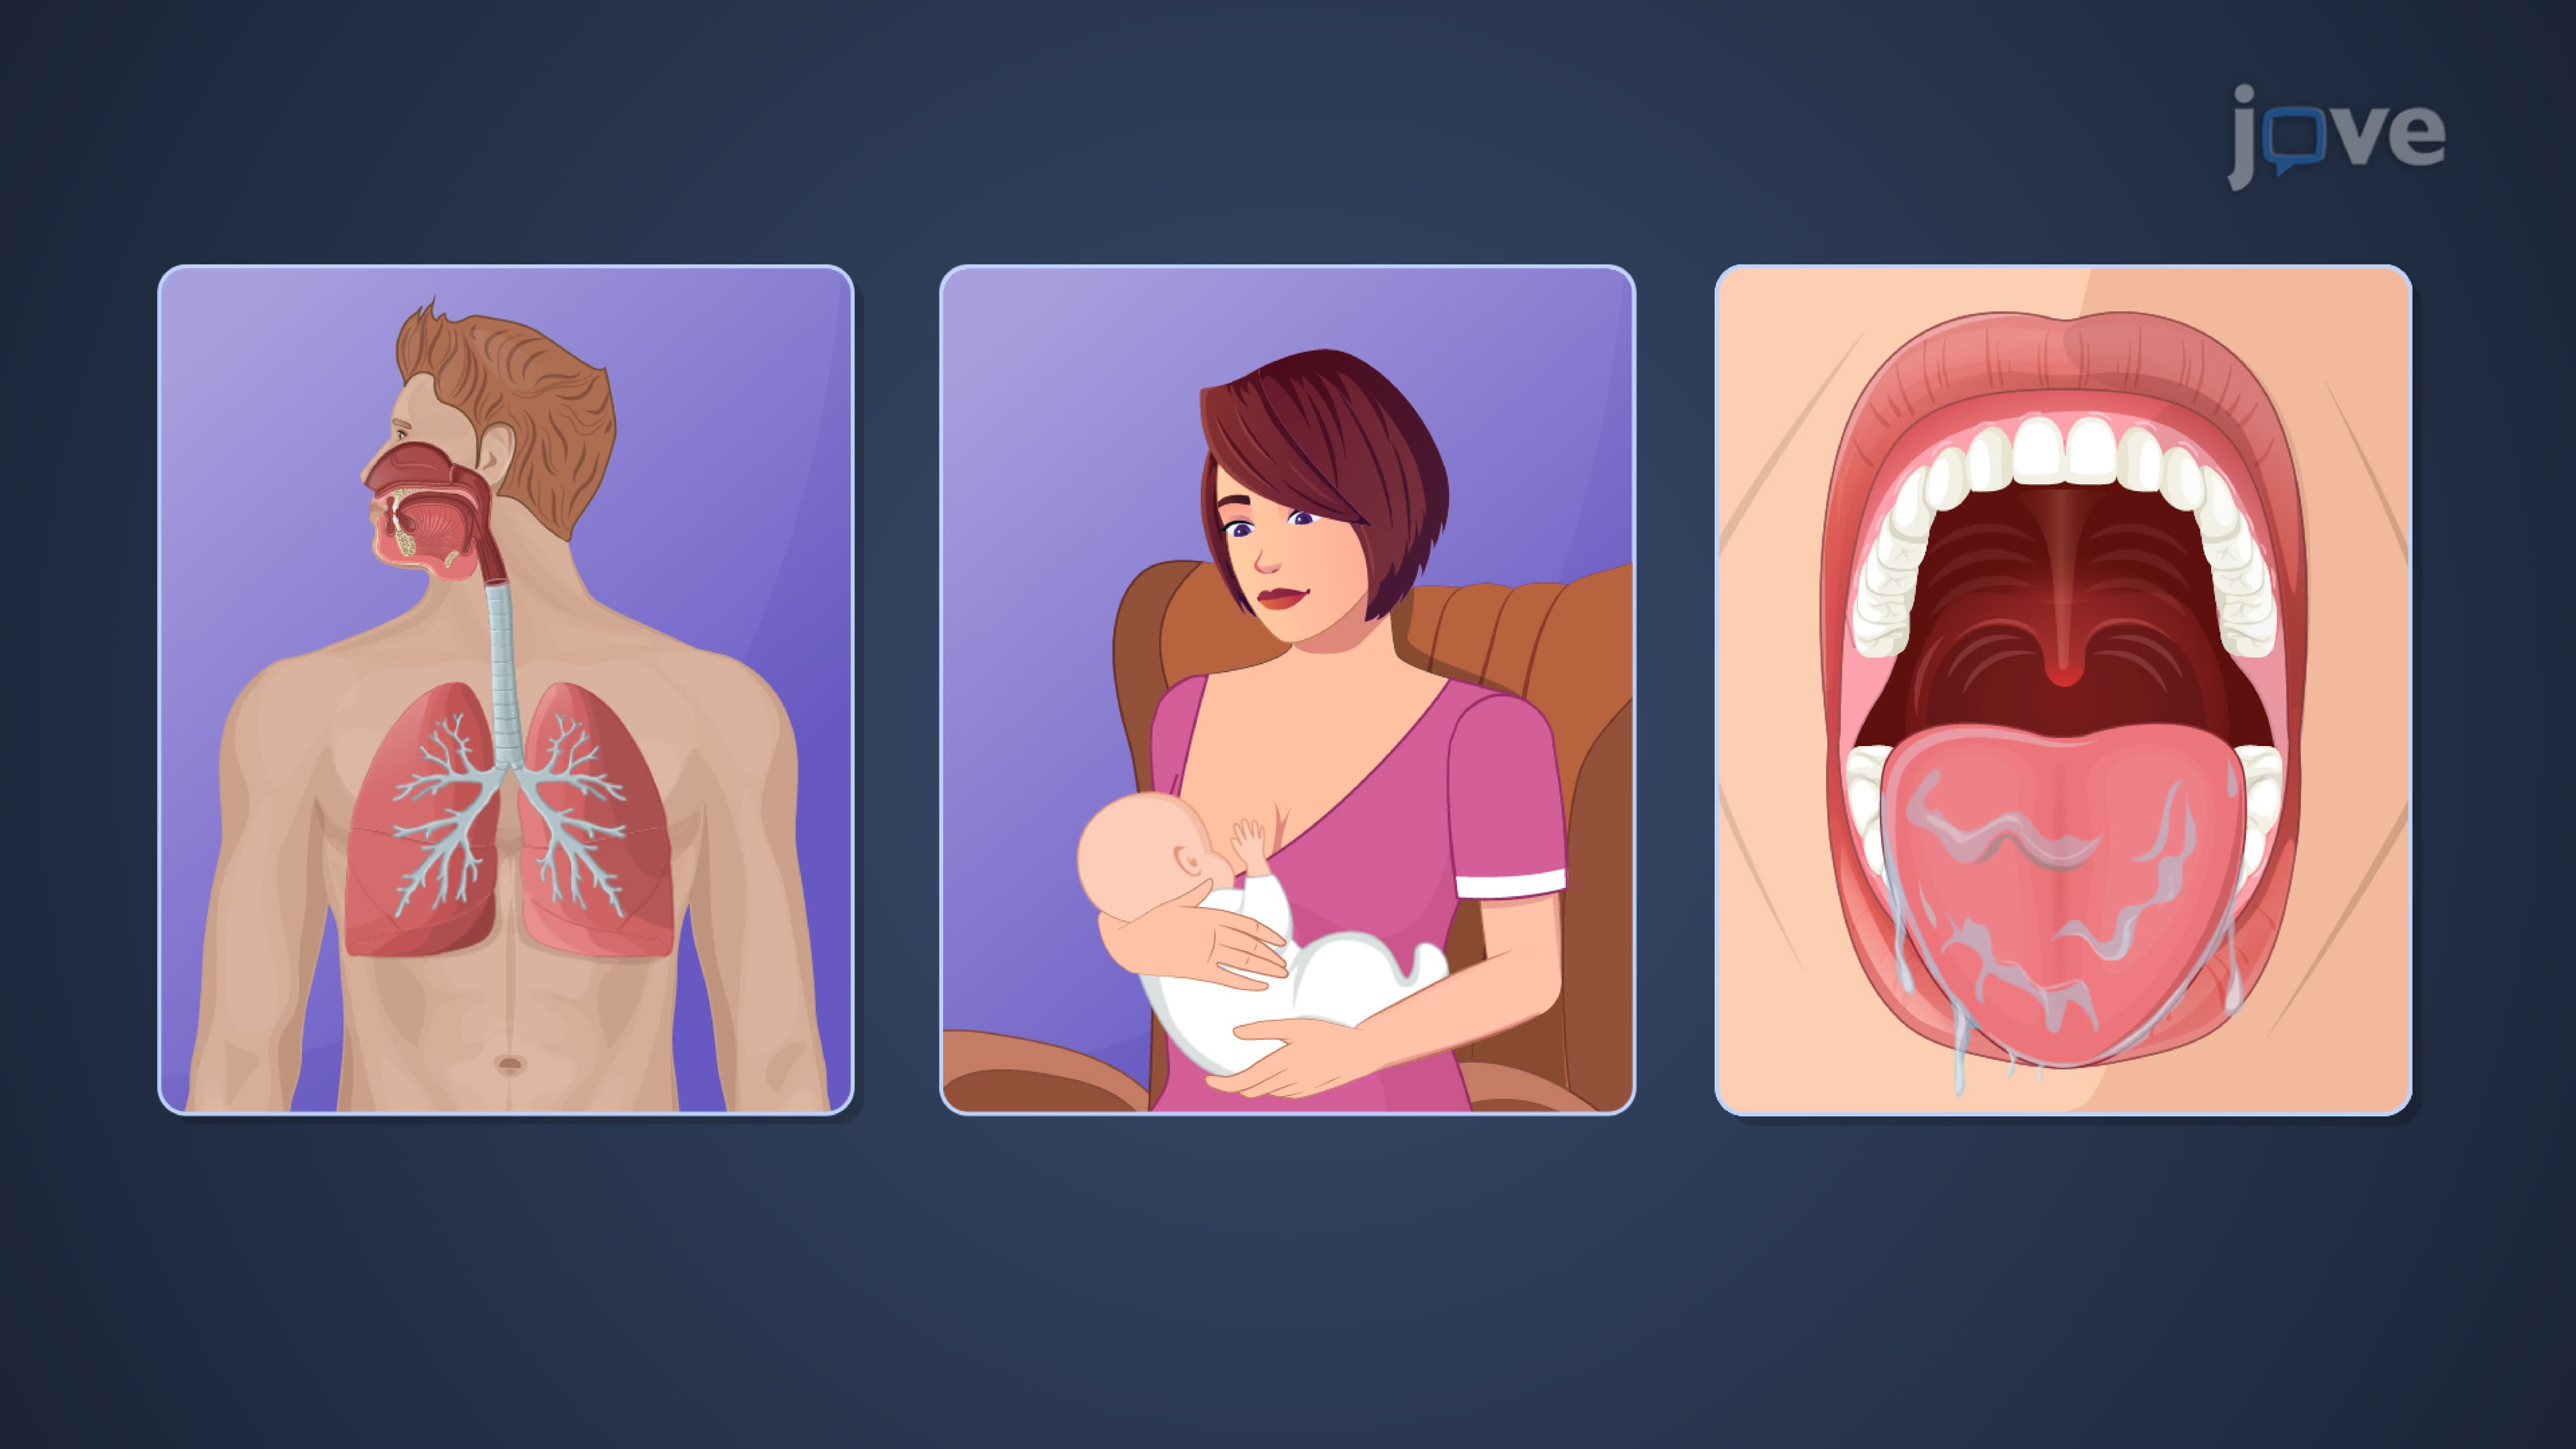
Drug Excretion: Pulmonary and Glandular Routes
Drugs can also be excreted in breast milk, which is crucial for breastfeeding infants. The...
 01:10
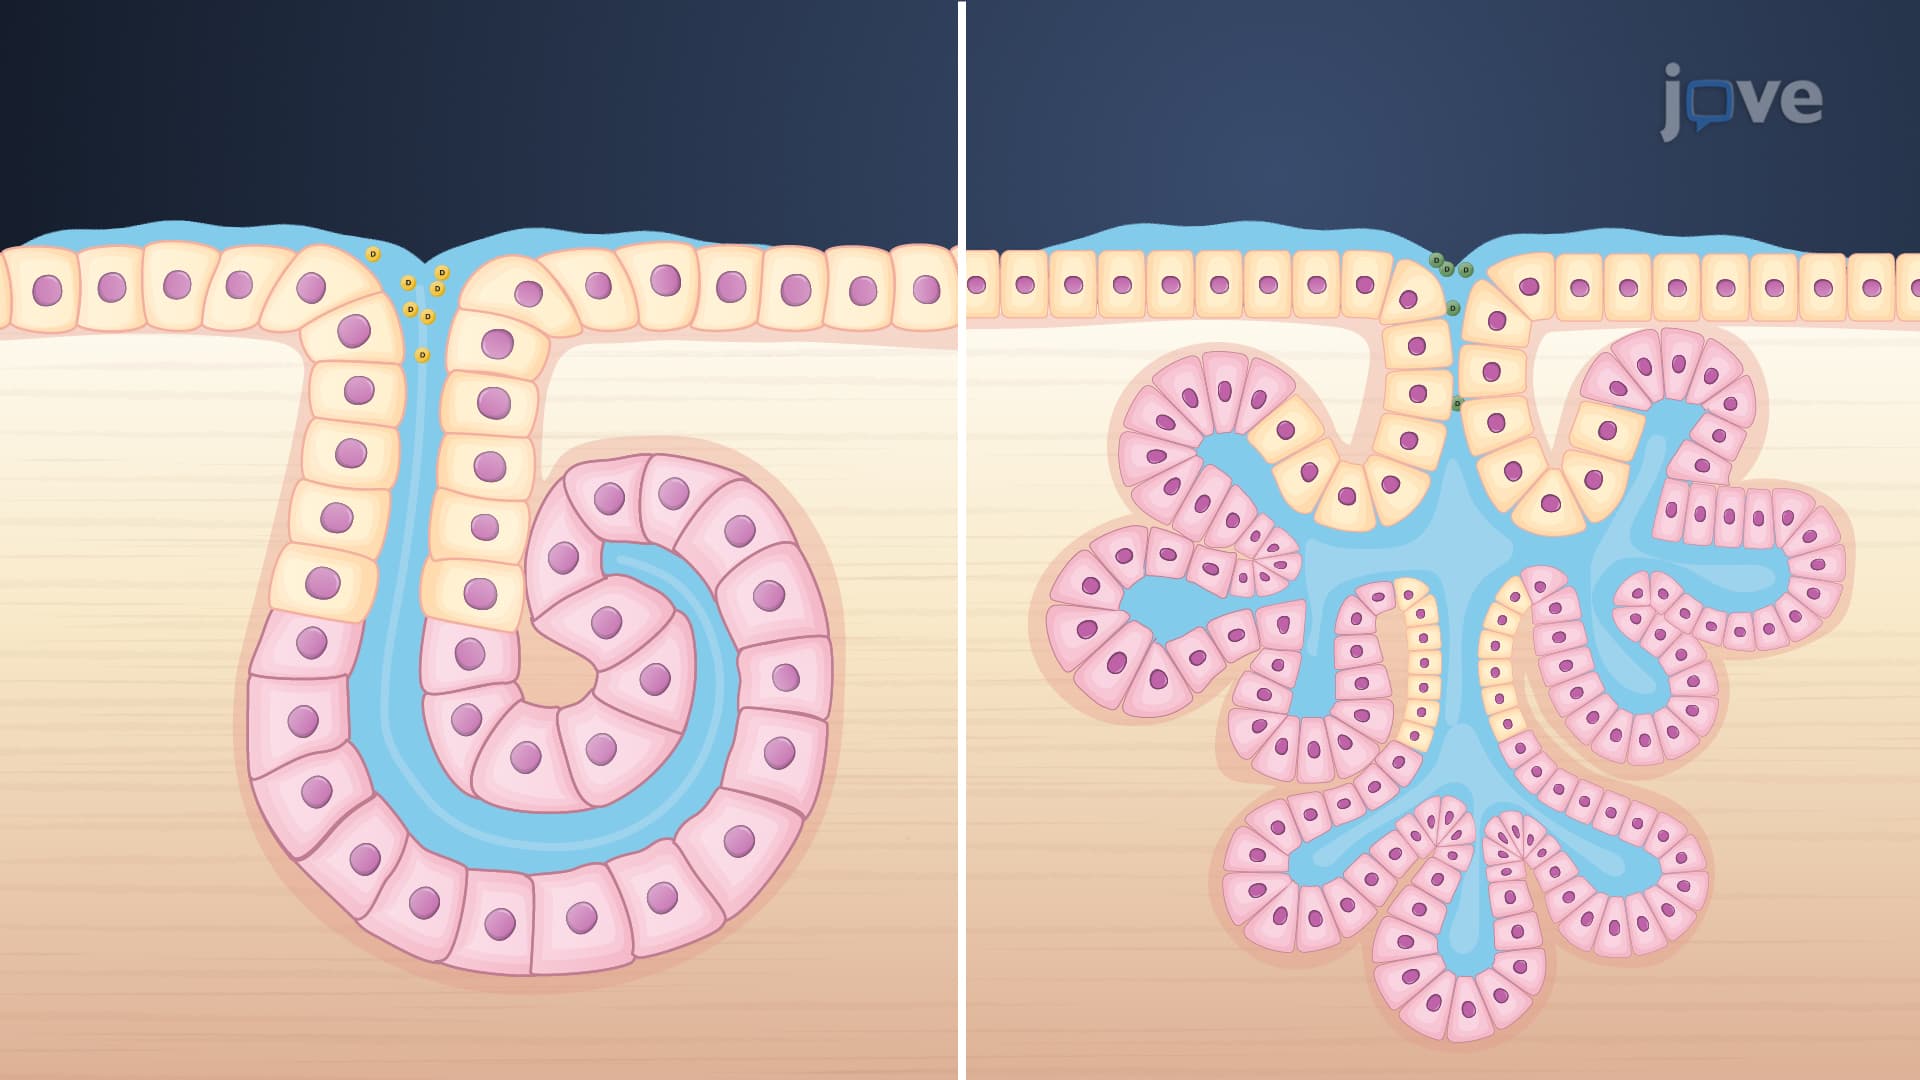
Drug Excretion: Miscellaneous Routes
 01:23
Drug Elimination: Non-Renal Routes
 01:18
Drug Elimination: Overview
Excretion refers to removing a drug from the body, either in its unchanged form or as its metabolites. Nonvolatile and polar drugs are primarily excreted through the kidneys, with other pathways including bile, sweat, saliva, and milk. Volatile drugs such as anesthetic gases are excreted via the...
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...