Related Experiment Video
Updated: Jul 1, 2025
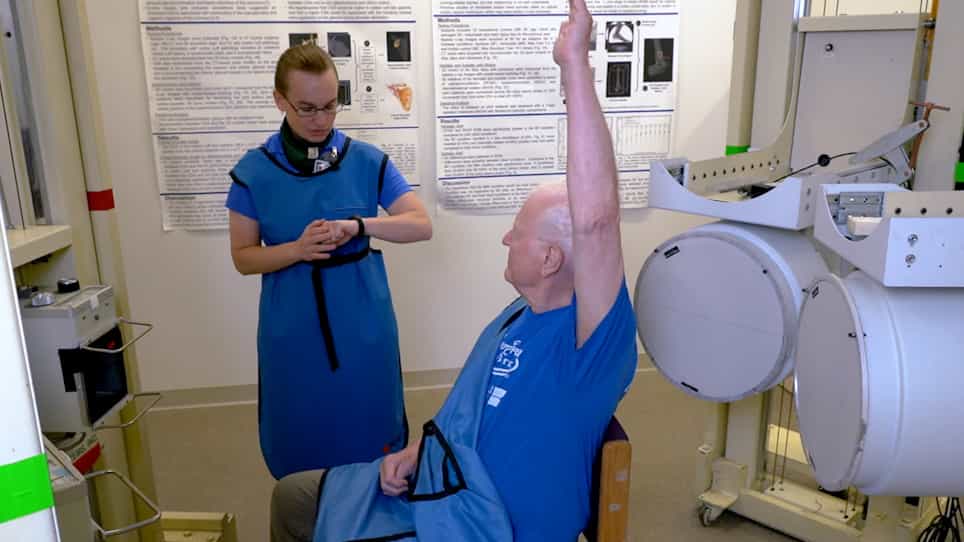

Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
Cost-effectiveness of shoulder arthroplasty for osteoarthritis and rotator cuff tear arthropathy. An economic
Tapio Flinkkilä1, Marko Vähäkuopus1, Kai Sirniö1
1Oulu University Hospital and MRC Oulu, Surgery, Kajaanintie 50, 90029 Oulu, Finland.

Introduction:
This study aimed to assess cost-effectiveness of shoulder arthroplasty for osteoarthritis (OA) and rotator cuff tear arthropathy (CTA) from the perspective of a publicly funded health care system using patient data, health utilities and costs from a real-world situation.
Hypothesis:
Our hypothesis was that arthroplasty for OA is more cost-effective than for CTA.
Material And Methods:
We gathered a cohort of patients with 153 anatomic total shoulder arthroplasty (TSA) for OA and 107 reverse shoulder arthroplasty (RSA) for CTA between years 2016-2020 at a university hospital. Short-term (mean 2.8years) shoulder function, health utilities and costs were obtained from prospectively collected data, and a Markov cohort simulation was carried out to assess lifetime cost-utility. The primary outcome measures were change in 15D score to calculate gain in quality-adjusted life years (QALYs) and change in Western Ontario osteoarthritis score of the shoulder (WOOS).
Results:
Both TSA and RSA restored shoulder function well, WOOS improvement was 59.7 (95% CI: 56.2-63.2) and 55.8 (95% CI: 50.4-61.2), respectively. The cost/QALY gained was 20,846.82 € for TSA and 38,711.90 € for RSA. The cost-utility was not remarkable sensitive to costs, discounting of future costs or estimated revision rates. However, the cost-effectiveness was very sensitive to change in 15D health utility scores and thus QALY gain, especially for RSA patients.
Discussion:
Shoulder arthroplasty restores shoulder function well in both OA and CTA. In health economic terms, RSA is less cost-effective than TSA in an everyday setting, mainly due to inferior improvement of health-related quality-of-life and reduced life expectancy of CTA patients.
Level Of Evidence:
III; case series.

