Related Experiment Video
Updated: Jul 1, 2025


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Gestational vitamin D and offspring fracture risk: do associations persist into mid adolescence?
Mia A Percival1, Kara B Anderson2, Julie A Pasco2,3,4,5
1Deakin University, IMPACT, The Institute for Mental and Physical Health and Clinical Translation, School of Medicine, Geelong, VIC, 3220, Australia. mia.percival@research.deakin.edu.au.

Background:
Previous studies report that maternal vitamin D exposure during pregnancy is associated with offspring later-life bone health. A study in the Vitamin D in Pregnancy (VIP) cohort reported sexually dimorphic effects of maternal 25-hydroxyvitamin-D (25(OH)D) and offspring fracture profiles at 10 years of age. We, therefore, aimed to determine associations between maternal 25(OH)D status and offspring fracture risk at 16 years of age in this cohort.
Methods:
In total, 475 mother-child pairs were recruited to the VIP study in southeastern Australia. Maternal serum samples were obtained at recruitment (<16 weeks' gestation) and/or 28-32 weeks' gestation and analysed for 25(OH)D. Radiologically-confirmed incident fractures in children were ascertained from date of birth (2002-2004) until July 16, 2019. Cox proportional hazard models were used to determine associations between maternal 25(OH)D and childhood fracture risk, and final models included maternal age at recruitment, offspring sex, birth weight, gestation length and season of 25(OH)D sample.
Results:
Data were available for 400 children (mean age 16.1 years). There were 122 (30.5%) children who sustained at least one fracture. Higher maternal 25(OH)D (per 10 nmol/L) in early gestation was associated with a decreased fracture risk in boys (HR 0.87; 95% CI: 0.77, 0.99); the pattern was reversed in girls (HR 1.10; 95% CI 1.00, 1.22). At late gestation, higher maternal 25(OH)D was associated with an increased fracture risk in girls (HR 1.14; 95% CI: 1.04, 1.24).
Conclusions:
While our findings must be interpreted within the constraints of our limitations, we report that the contradictory risk profiles observed at early childhood in this cohort remain in adolescence.
More Related Videos
 03:19
Author Spotlight: Studying the Impact of Maternal Dietary Deficiencies on Long-Term Offspring Health Outcomes
Published on: June 28, 2024
 04:24
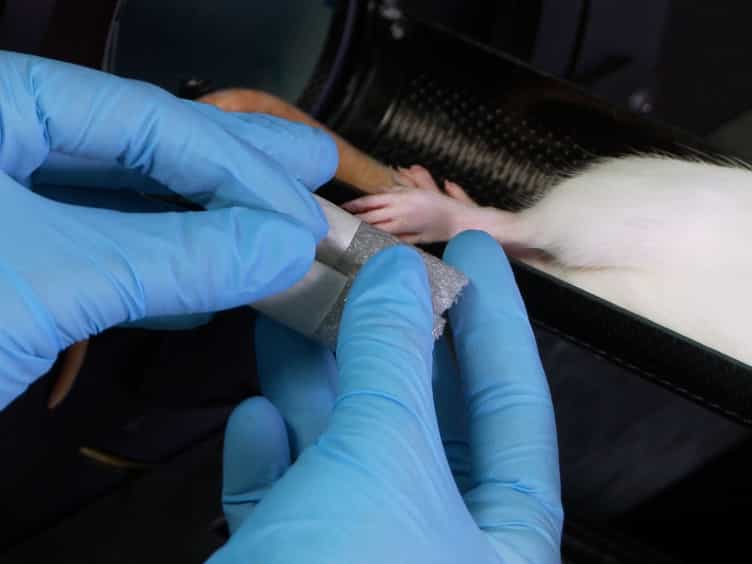
Proper Positioning and Restraint of a Rat Hind Limb for Focused High Resolution Imaging of Bone Micro-architecture Using In Vivo Micro-computed Tomography
Published on: November 22, 2017
Related Concept Videos
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:22
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...