Related Experiment Video
Updated: Jul 18, 2026

Magnetic Resonance Imaging Quantification of Pulmonary Perfusion using Calibrated Arterial Spin Labeling
Published on: May 30, 2011
Rest and exercise-stress estimated pulmonary capillary wedge pressure using real-time free-breathing cardiovascular
Sören J Backhaus1, Alexander Schulz2, Torben Lange2
1Department of Cardiology, Campus Kerckhoff of the Justus-Liebig-University Giessen, Kerckhoff-Clinic, Bad Nauheim, Germany; German Center for Cardiovascular Research (DZHK), Partner Site Rhine-Main, Bad Nauheim, Germany.

Background:
Identification of increased pulmonary capillary wedge pressure (PCWP) by right heart catheterization (RHC) is the reference standard for the diagnosis of heart failure with preserved ejection fraction (HFpEF). Recently, cardiovascular magnetic resonance (CMR) imaging estimation of PCWP at rest was introduced as a non-invasive alternative. Since many patients are only identified during physiological exercise-stress, we hypothesized that novel exercise-stress CMR-derived PCWP emerges superior compared to its assessment at rest.
Methods:
The HFpEF-Stress Trial prospectively recruited 75 patients with exertional dyspnea and diastolic dysfunction who then underwent rest and exercise-stress RHC and CMR. HFpEF was defined according to PCWP (overt HFpEF ≥15 mmHg at rest, masked HFpEF ≥25 mmHg during exercise-stress). CMR-derived PCWP was calculated based on previously published formula using left ventricular mass and either biplane left atrial volume (LAV) or monoplane left atrial area (LAA).
Results:
LAV (rest/stress: r = 0.50/r = 0.55, p < 0.001) and LAA PCWP (rest/stress: r = 0.50/r = 0.48, p < 0.001) correlated significantly with RHC-derived PCWP while numerically overestimating PCWP at rest and underestimating PCWP during exercise-stress. LAV and LAA PCWP showed good diagnostic accuracy to detect HFpEF (area under the receiver operating characteristic curve (AUC) LAV rest 0.73, stress 0.81; LAA rest 0.72, stress 0.77) with incremental diagnostic value for the detection of masked HFpEF using exercise-stress (AUC LAV rest 0.54 vs stress 0.67, p = 0.019, LAA rest 0.52 vs stress 0.66, p = 0.012). LAV but not LAA PCWP during exercise-stress was a predictor for 24 months hospitalization independent of a medical history for atrial fibrillation (hazard ratio (HR) 1.26, 95% confidence interval 1.02-1.55, p = 0.032).
Conclusion:
Non-invasive PCWP correlates well with the invasive reference at rest and during exercise stress. There is overall good diagnostic accuracy for HFpEF assessment using CMR-derived estimated PCWP despite deviations in absolute agreement. Non-invasive exercise derived PCWP may particularly facilitate detection of masked HFpEF in the future.
More Related Videos
 08:35
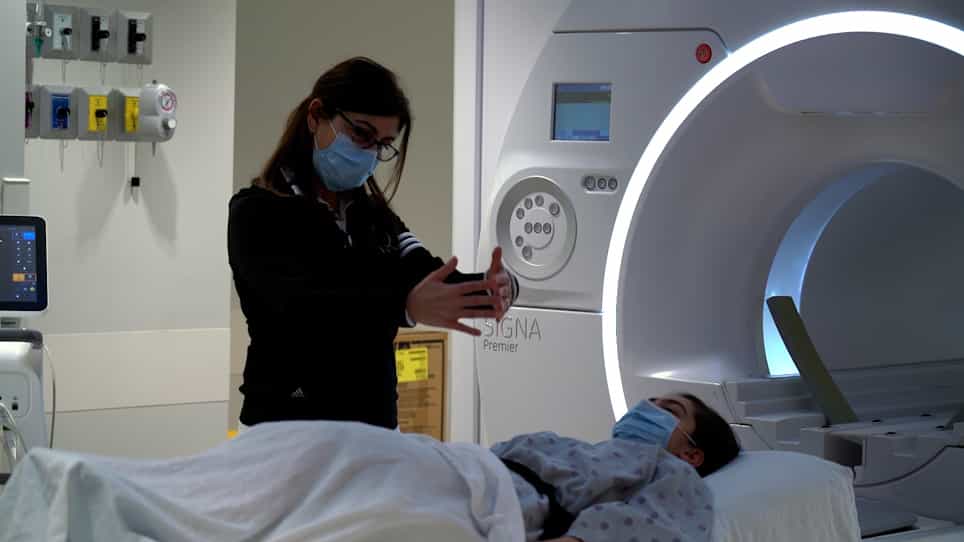
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
 05:07
Author Spotlight: Optimized Lung MRI Protocol with Computationally Efficient Reconstruction Methods
Published on: September 6, 2024
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:26
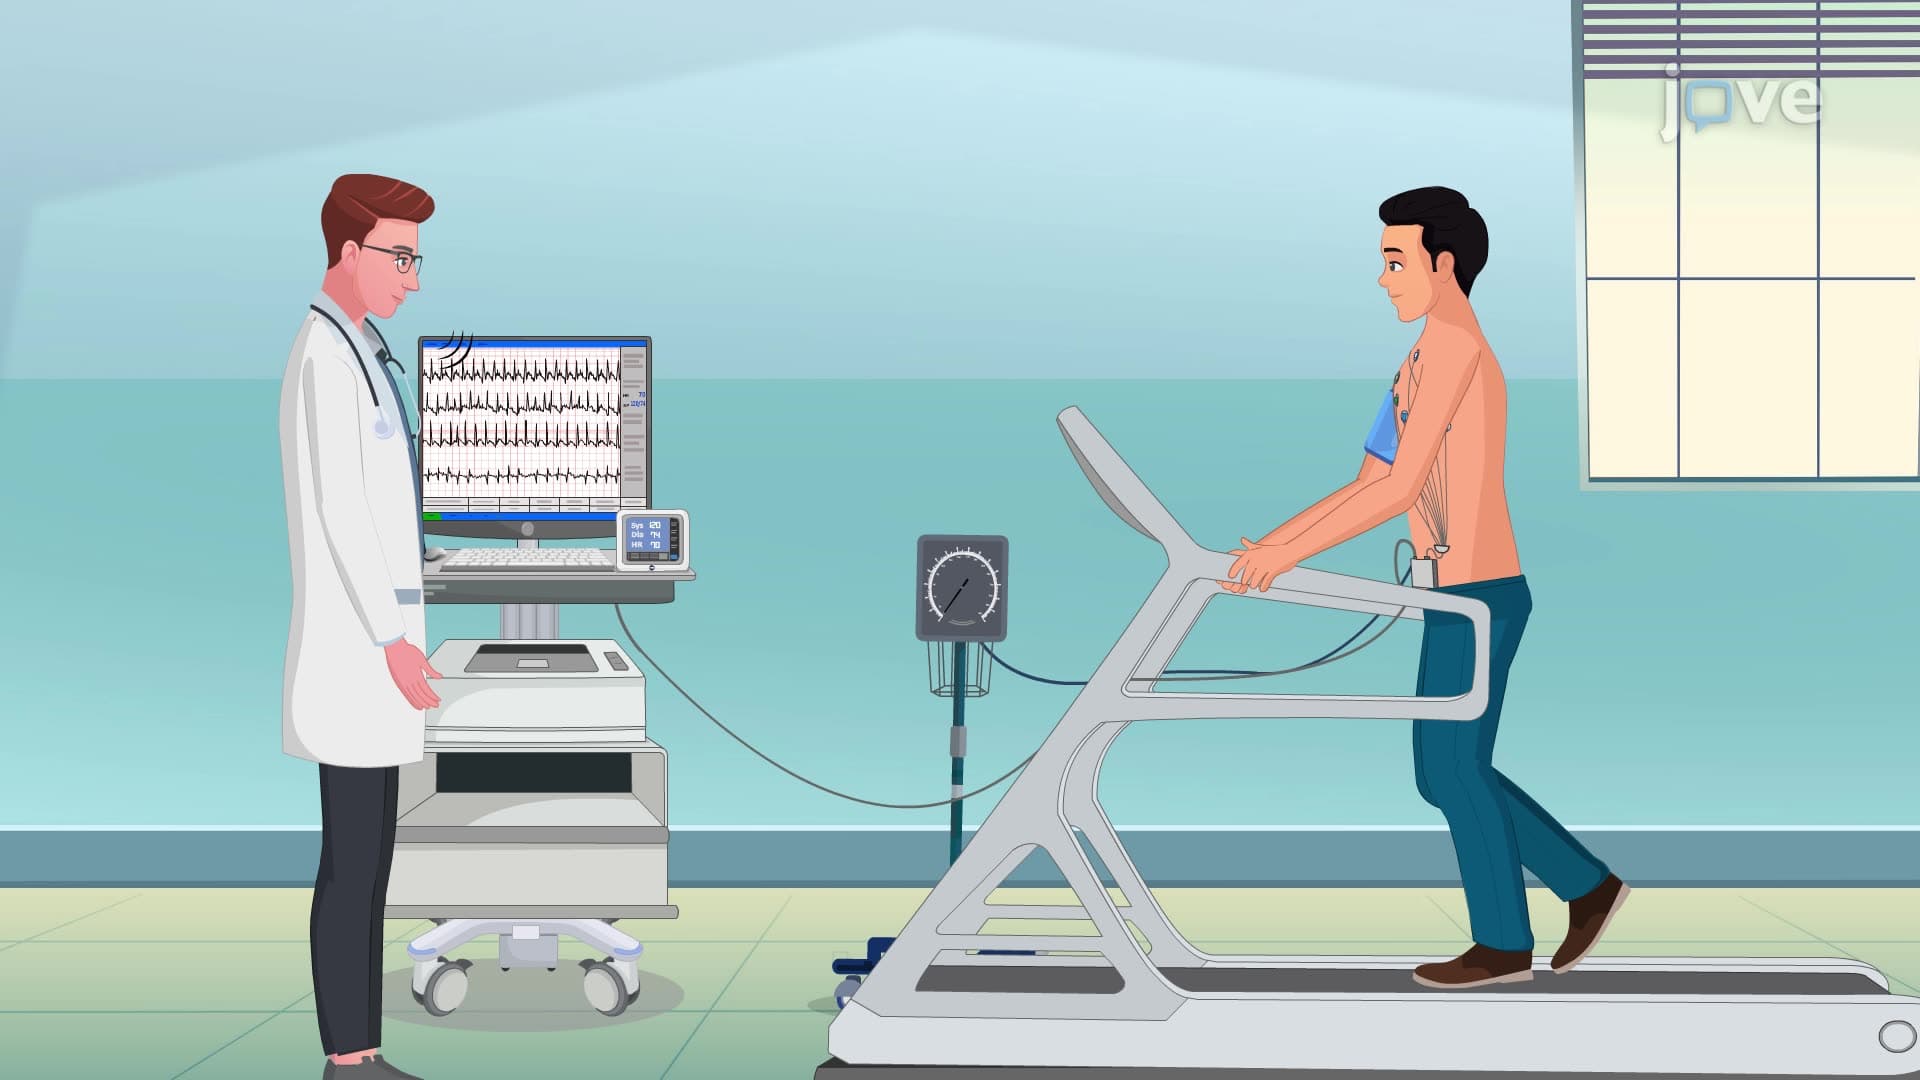
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes