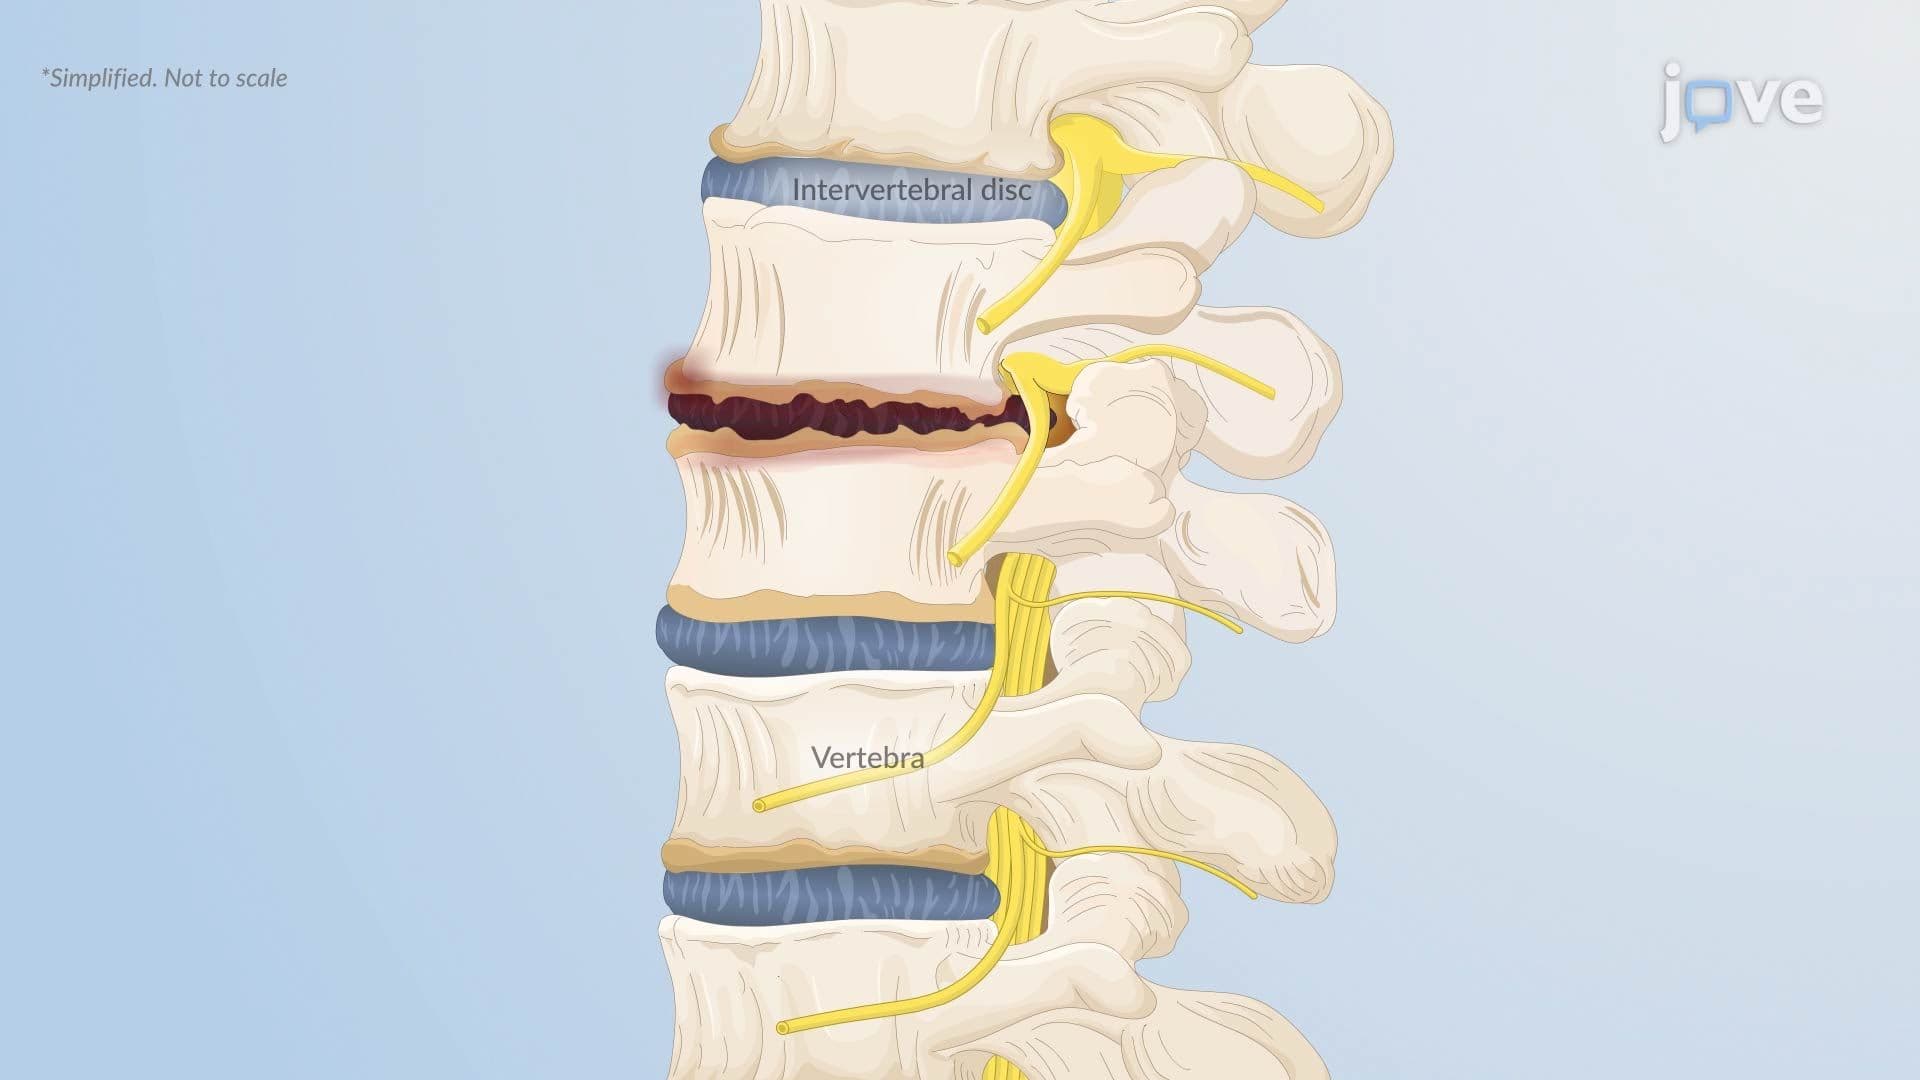
Related Experiment Video
Updated: May 5, 2026

Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Dural ectasia with cauda equina syndrome, a rare case report
Tumwesige R Kondo1, Mathias S Ncheye2, Happiness R Massawe2
1Department of Orthopedics and Traumatology, Kilimanjaro Christian Medical Centre, Moshi, Tanzania; Kilimanjaro Christian Medical University College, Moshi, Tanzania.

Introduction And Importance:
Dural ectasia, which is often idiopathic, is seen both in patients with neurofibromatosis and Marfan's syndrome. In neurofibromatosis, the ectasia is most often seen in the thoracic region but can occur at any point along the dura. A complication such as cauda equina syndrome is usually rare.
Clinical Presentation:
A 48 year old male complaining of recurrent throbbing headache, for 3 years, 2 years ago he developed progressively lower back pain, associated with numbness and tingling sensation of the lower limbs. A year ago he experienced defecation and urinary incontinence. On further questioning the patient reported to have first degree relative with neurofibromatosis. On examination he has multiple café au laite on the trunk, back and left arm, and plexiform on the left palm, mild right deviation on thoracic region on the back. Lower limb muscle power grade 4/5 bilaterally, sensation was intact. Laboratory work up Full blood counts, electrolytes, renal and liver function tests were normal, MRI of the lumbar spine demonstrate L3/L4 and L4/l5 mild disc bulge with no significant narrowing of the primary canal and no evidence of existing nerve root impingement, increase antero-posterior diameter of dura sac involving L5-S1, with a Dural Sac Diameter of S1 increased compared to that of L4 with mild scalloping of lower lumbar vertebra and pronounced at S1 vertebral body. A diagnosis of cauda equina syndrome and dural ectasia secondary to neurofibromatosis was rendered. Lumbar peritoneal shunting, was reached as a surgical treatment for this patient, but due to inadequate and unavailability of the required shunting equipment, the patient was managed conservatively with anti- inflammatory medications, lumbar CSF tapping, genital hygiene and counselling. 3 months of follow up, the patient was able to walk, with power 5/5 to both lower limbs, however fecal and urine incontinence persisted.
Discussion:
this case was particularly unusual due to the combination of cauda equina syndrome and dural ectasia, Dural ectasia is seen with various conditions including Marfan syndrome, Ehlers-syndrome, neurofibromatosis 1, Ankylosing spondylitis, trauma, scoliosis or tumors it may also have no clear cause. In most cases patients with dural ectasia are asymptomatic few may present with low back pain, radicular pain in the buttocks or legs and headache and rarely caudal equina syndrome. The management of dura ectasia may be conservative for asymptomatic patient and for a symptomatic patient surgery such as stabilization, marsupialization and lumbar peritoneal shunt.
Conclusion:
Dural ectasia with cauda equina syndrome are rarely complication of neurofibromatosis. Familiarity with its classic imaging and clinical features as described in this case report can help its early detection and management.
More Related Videos
 05:17
Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
 04:33
Spinal Hernia Repair and Cauda Equina Repositioning After Lumbar Decompression under Three-Dimensional Microscopy: A Case Report and Literature Review
Published on: November 8, 2024