
Pneumothorax After Superior Plating of Clavicle Fractures: Are the Concerns Warranted?
Abhishek Ganta1, Sara Solasz, Nina Fisher
1From the Department of Orthopedic Surgery, Division of Orthopedic Trauma Surgery, NYU Langone Orthopedic Hospital, NYU Langone Health, New York, NY (Ganta, Solasz, Fisher, Leucht, Konda, and Egol), and Department of Orthopaedic Surgery, Jamaica Hospital Medical Center, Richmond Hill, NY (Konda, and Egol).

Purpose:
The primary goal of this study was to determine the anatomic relationship between the clavicle and the apical lung segment. The secondary goal was to determine the incidence of pneumothorax (PTX) in patients who underwent clavicle ORIF to analyze the utility of postoperative chest radiographs.
Methods:
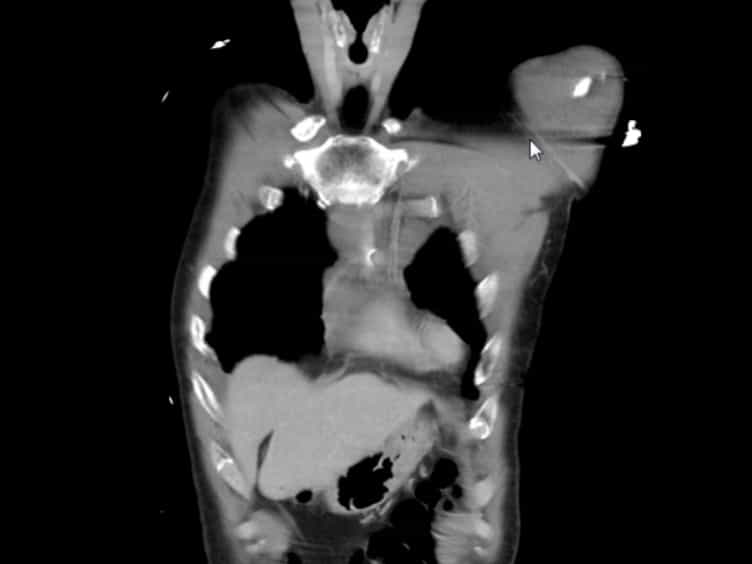
Six hundred thirty-one patients with a midshaft clavicle fracture who underwent superior plating at a single institution were identified. Forty-two patients had a CT scan of the chest. Three points on the uninjured clavicle were defined: 2 cm from the medial end of the clavicle, the mid-point of the clavicle, and 2 cm from the lateral end of the clavicle. At each point, the distance from both the inferior cortex and the superior cortex of the clavicle to the apical lung segment was measured. All 631 patients who underwent Open Reduction and Internal Fixation had a postoperative chest radiograph to evaluate implant placement, restoration of clavicular length, and presence of PTX.
Results:
From the lateral end of the clavicle, the mean distance of the lung was 60.0 ± 14.9 mm (20.1 to 96.1 mm) from the inferior cortex of the clavicle. At the mid-point, the mean distance of the lung was 32.3 ± 7.2 mm (20.4 to 45.5 mm) from the inferior cortex of the clavicle. At the medial end, the mean distance of the lung was 18.0 ± 5.5 mm (8.1 to 28.9 mm) from the inferior cortex of the clavicle. A review of postoperative radiographs for all 631 patients revealed none (0%) with a postoperative iatrogenic PTX.
Conclusion:
The risk of injury is minimal in all three zones. Postoperative chest radiographs after clavicle fracture repair to rule out PTX are unnecessary.
More Related Videos

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:13
Pleura of the Lungs