Related Experiment Video
Updated: Jul 1, 2025


Bladder Smooth Muscle Strip Contractility as a Method to Evaluate Lower Urinary Tract Pharmacology
Published on: August 18, 2014
Adreno-Muscarinic Synergy of Contractile Responses From Human Hyperplastic Prostate
Ben T Blake-James1, Basu Chakrabarty2, Christopher H Fry2
1Division of Surgery & Interventional Science, University College London, London, UK.

Purpose:
Adreno-muscarinic synergy, a supra-additional contractile response to simultaneous application of α-adrenoreceptor and muscarinic receptor agonists, is a feature of several lower urinary tract regions that have dual sympathetic and parasympathetic innervation. We tested the hypothesis that synergy is also a feature of prostate tissue obtained from men with benign prostatic enlargement.
Methods:
Isolated tissue strips were dissected from prostate 'chips', collected after transurethral prostate resection procedures for in vitro experiments, to measure isometric tension at 36°C.
Results:
Added separately to the superfusate, phenylephrine and carbachol generated contractions with mean pEC50 (-log10EC50) values of 5.36 and 5.58, respectively, although phenylephrine maximal responses were about six-fold greater. In the presence of carbachol, the mean phenylephrine pEC50 was significantly increased to 5.84 and maximal response increased by 28%; overall, a significant synergistic response was demonstrated. The synergistic response was reduced by muscarinic receptor antagonists, most potently by the M3-selective agent 4-DAMP (1,1-dimethyl-4-diphenylacetoxypiperidinium iodide), and less so by M2 and M1-selective inhibitors gallamine and pirenzepine, but with an overall profile indicating M3/M2 mediation of the synergistic response. The magnitude of the synergistic response was variable between prostate chips that provided isolated preparations suggesting regional heterogenicity, although their zonal origin could not be determined.
Conclusion:
These experiments show that adreno-muscarinic contractile synergy is a feature of human hyperplastic prostate tissue. This has implications for the use of a combination therapy of α-blockers and anti-muscarinic agent to relieve secondary symptoms associated with benign prostatic hyperplasia, at least in men who can tolerate antimuscarinics without a risk of retention.
More Related Videos

Related Concept Videos
 00:59
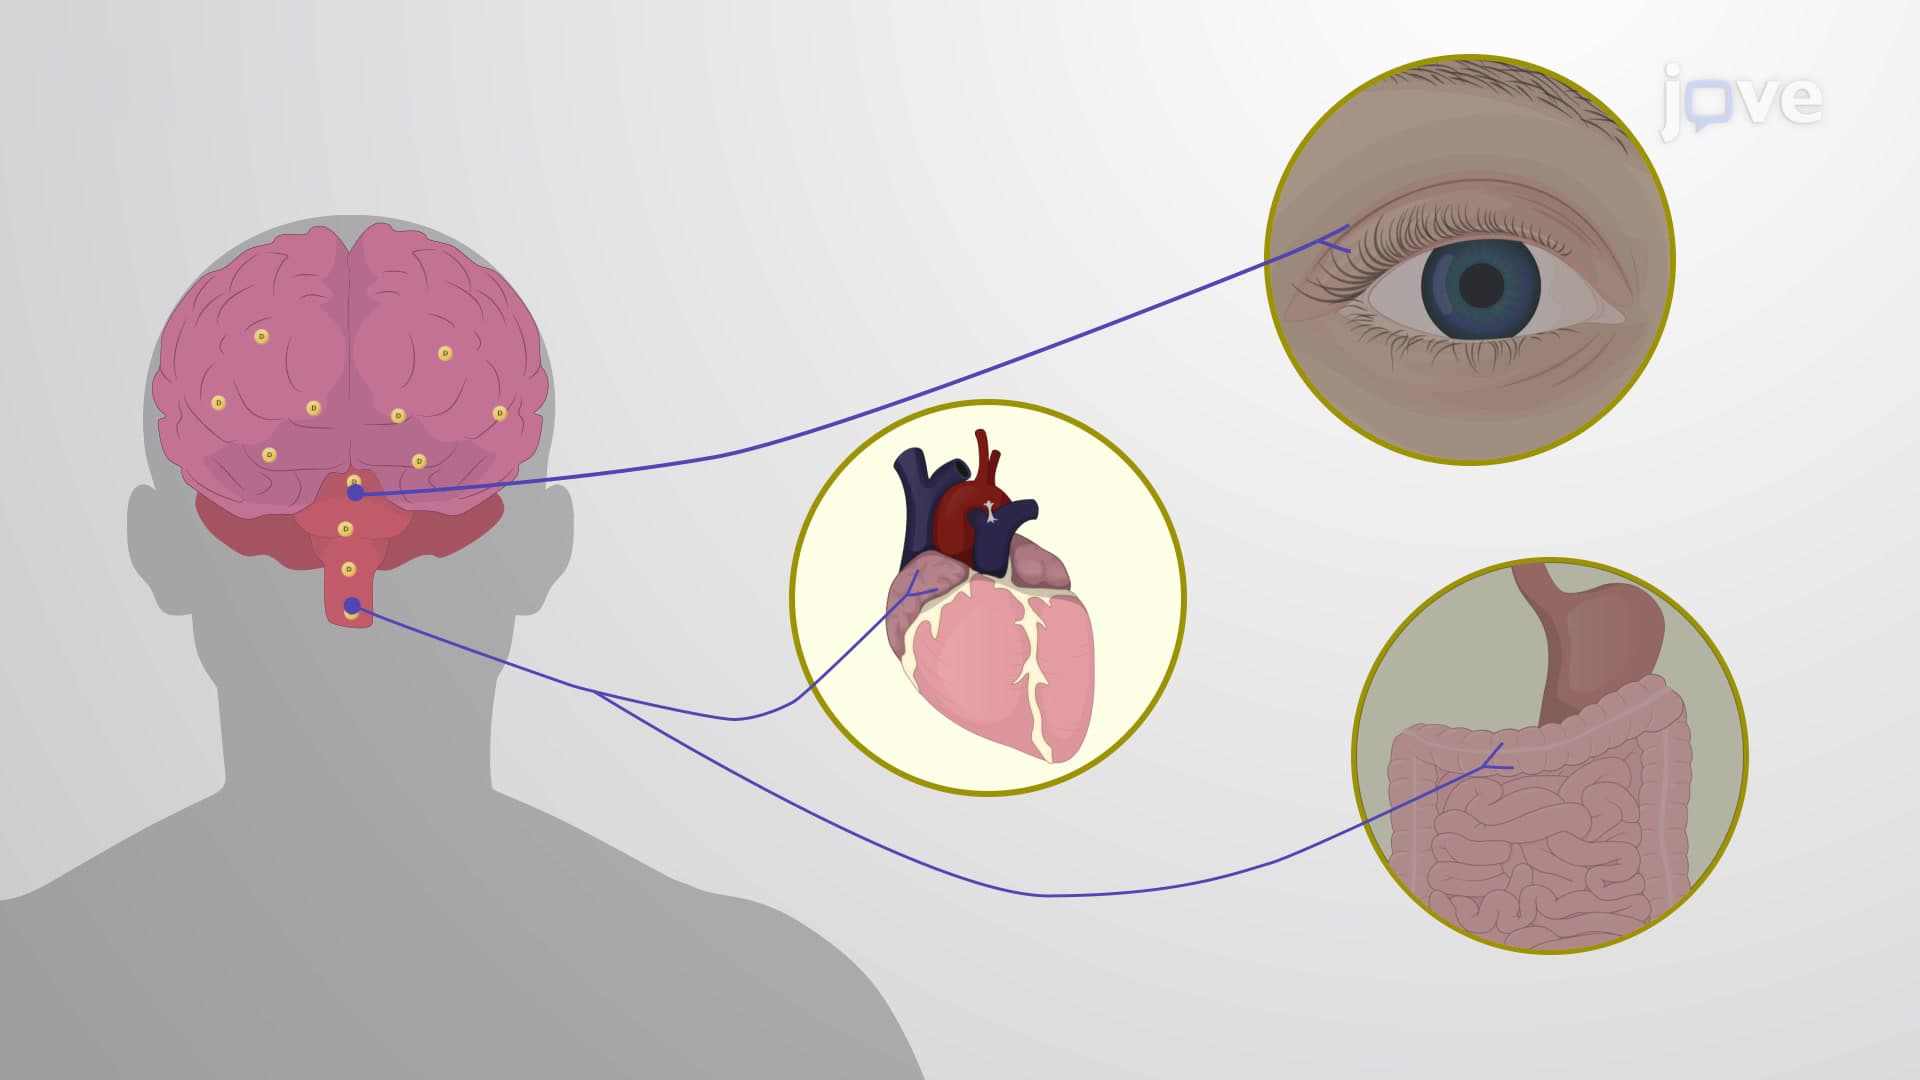
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:31
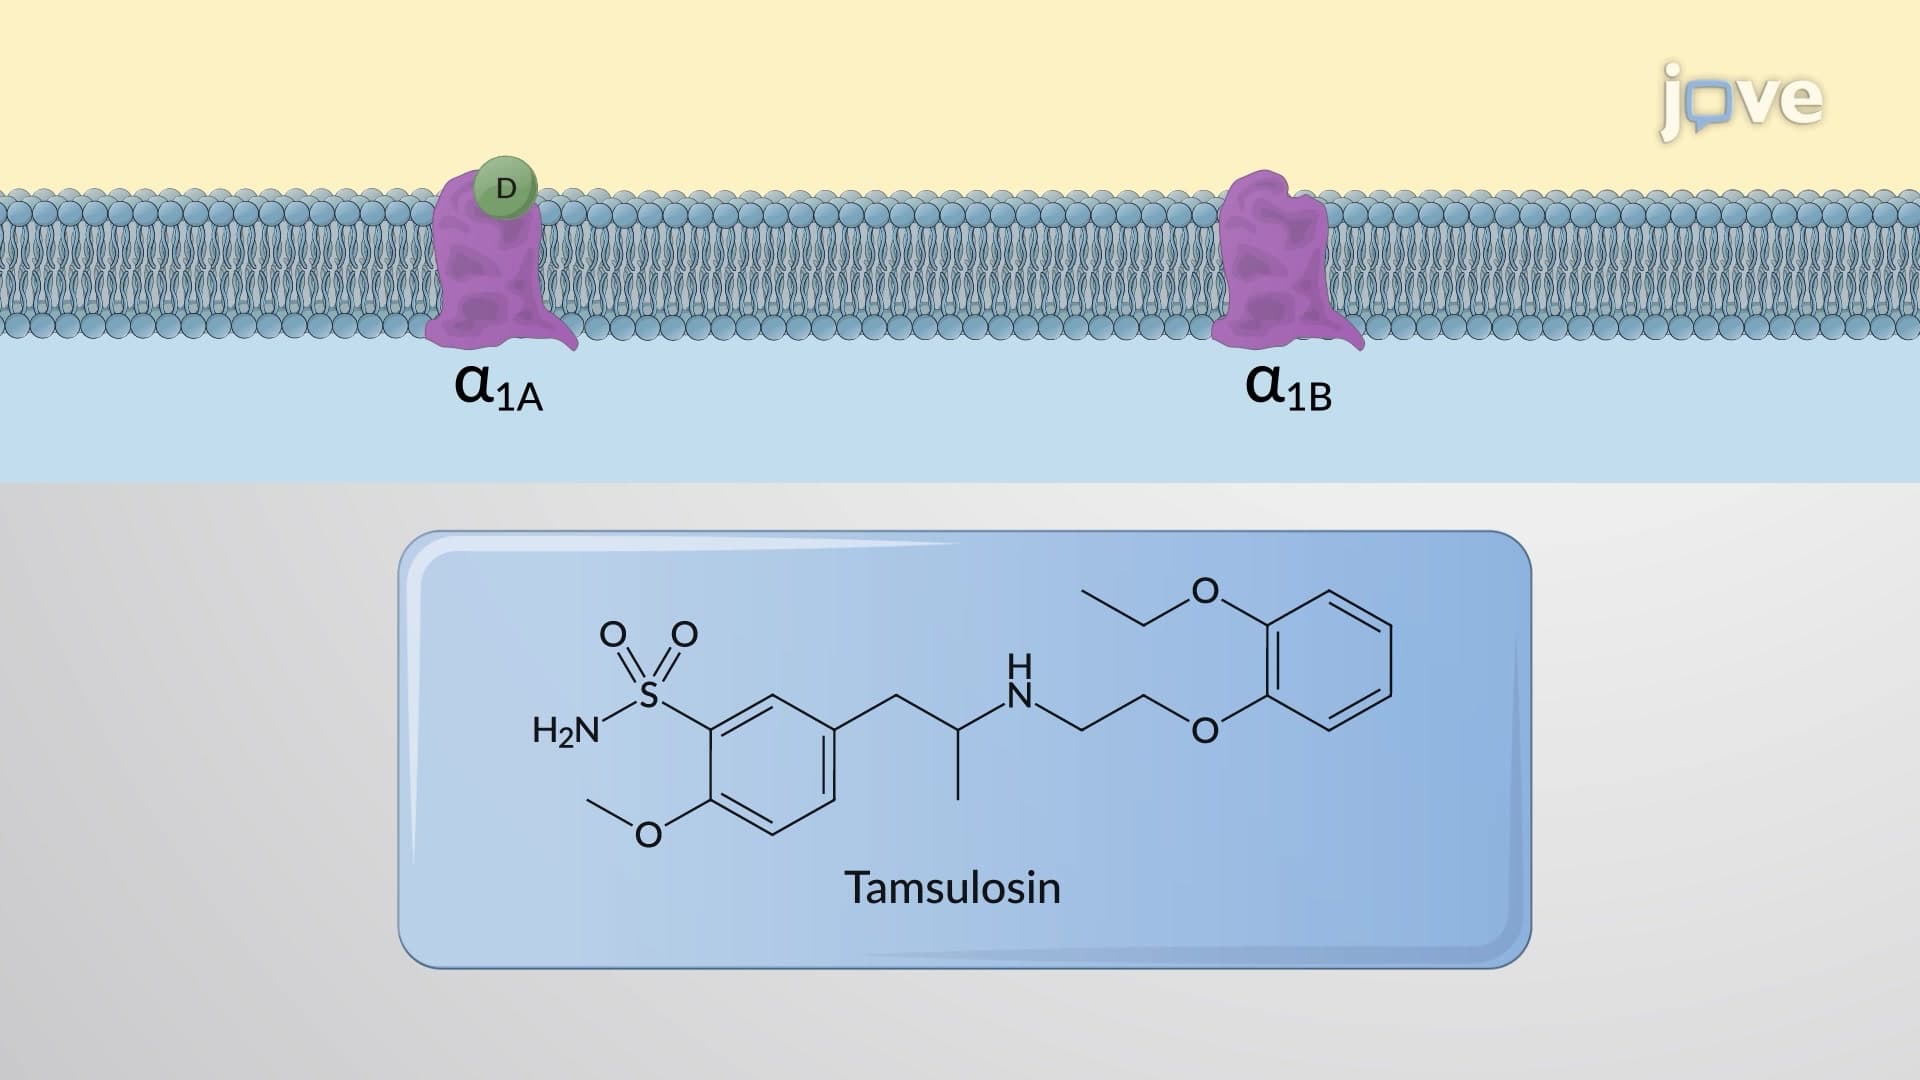
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:26
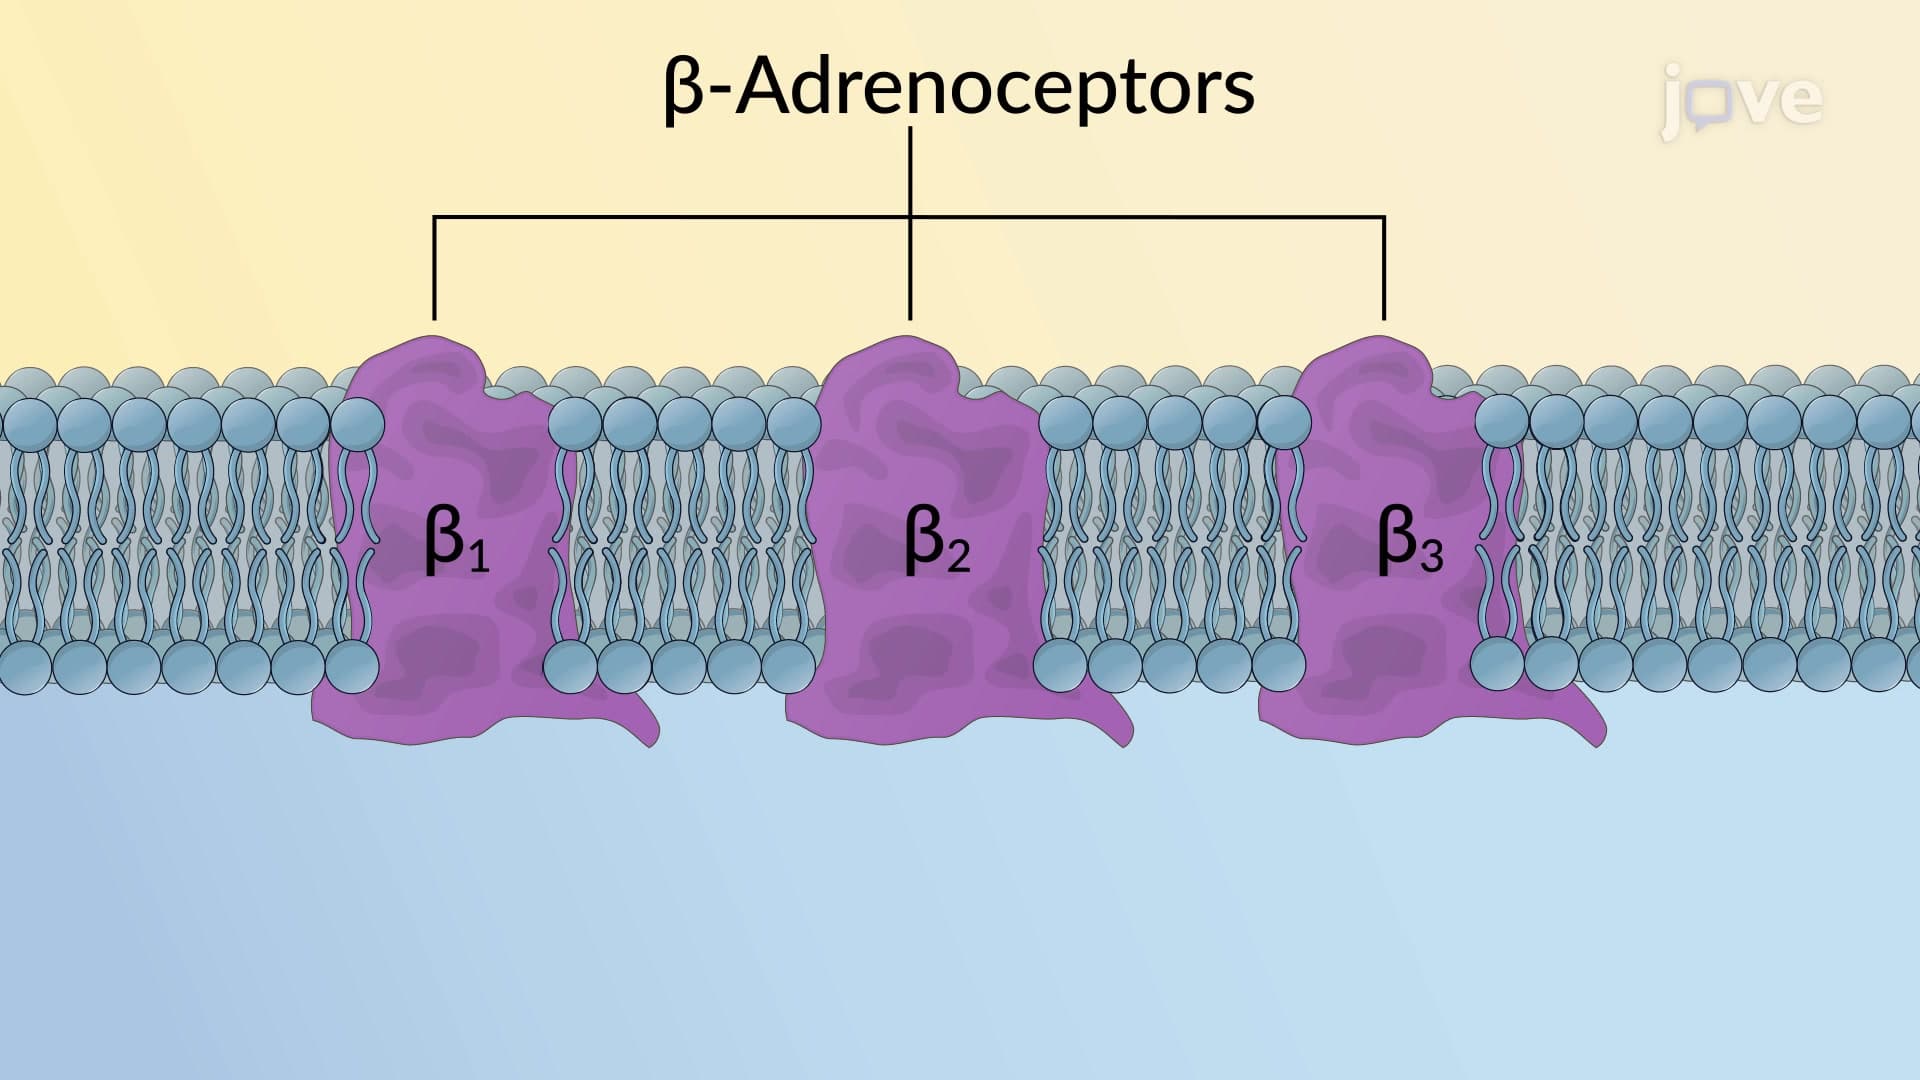
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:25
Cholinergic Receptors: Muscarinic
The subtypes M1, M3, and M5 couple with the Gq subunit and activate the phospholipase C (PLC) activity, mobilizing intracellular Ca2+....
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:28
Cholinergic Antagonists: Pharmacological Actions
Gastrointestinal Effects: Antimuscarinics reduce gut contractions, increase gastric emptying, and slow intestinal transit. They partly inhibit gastric acid secretion...