Related Experiment Video
Updated: Jul 1, 2025
Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Oblique anterior column realignment with a mini-open posterior column osteotomy for minimally invasive adult spinal
Zach Pennington1, Nolan J Brown2, Seyedamirhossein Pishva3
11Department of Neurologic Surgery, Mayo Clinic, Rochester, Minnesota.

Background:
Adult spinal deformity (ASD) occurs from progressive anterior column collapse due to disc space desiccation, compression fractures, and autofusion across disc spaces. Anterior column realignment (ACR) is increasingly recognized as a powerful tool to address ASD by progressively lengthening the anterior column through the release of the anterior longitudinal ligament during lateral interbody approaches. Here, we describe the application of minimally invasive ACR through an oblique antepsoas corridor for deformity correction in a patient with adult degenerative scoliosis and significant sagittal imbalance.
Observations:
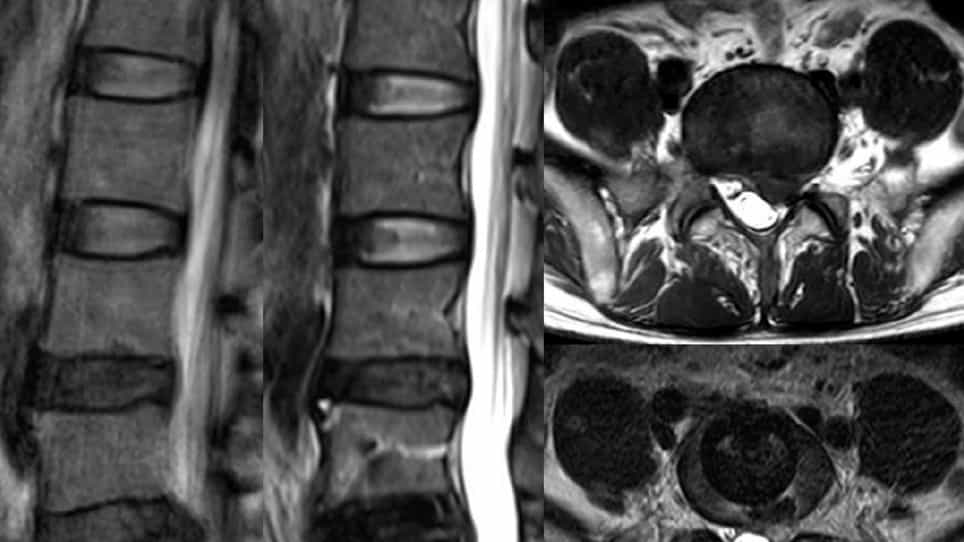
A 65-year-old female with a prior history of L4-5 transforaminal lumbar interbody fusion and morbid obesity presented with refractory, severe low-back and lower-extremity pain. Preoperative radiographs showed significant sagittal imbalance. Computed tomography showed a healed L4-5 fusion and a vacuum disc at L3-4 and L5-S1, whereas magnetic resonance imaging was notable for central canal stenosis at L3-4. The patient was treated with a first-stage L5-S1 lateral anterior lumbar interbody fusion with oblique L2-4 ACR. The second-stage posterior approach consisted of a robot-guided minimally invasive T10-ilium posterior instrumented fusion with a mini-open L2-4 posterior column osteotomy (PCO). Postoperative radiographs showed the restoration of her sagittal balance. There were no complications.
Lessons:
Oblique ACR is a powerful minimally invasive tool for sagittal plane correction. When combined with a mini-open PCO, substantial segmental lordosis can be achieved while eliminating the need for multilevel PCO or invasive three-column osteotomies.