Related Experiment Video
Updated: Jul 1, 2025
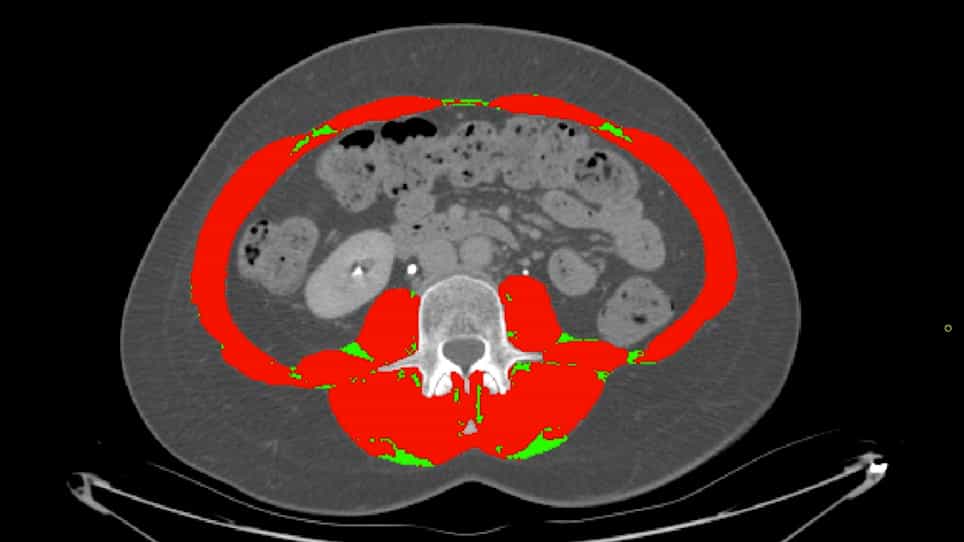

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Sarcopenia assessed using a questionnaire can predict in-hospital mortality in older patients with pulmonary
Masayoshi Kakiuchi1, Tatsuro Inoue2, Hikaru Kobayashi1
1Department of Rehabilitation, Kobe City Nishi-Kobe Medical Center, 5-7-1, Kojidai, Nishi-ku, Kobe-shi, Hyogo-ken, 651-2273, Japan.

Background & Aims:
Pulmonary tuberculosis is a severe disease with a high mortality rate. However, whether sarcopenia is a risk factor for in-hospital mortality remains unclear. The SARC-F (five items: strength, assistance in walking, rising from a chair, climbing stairs, and falls) is a questionnaire developed to screen for sarcopenia. This study aimed to determine whether the high risk of sarcopenia, assessed using the SARC-F questionnaire, affects in-hospital mortality in older patients with pulmonary tuberculosis.
Methods:
This was a retrospective, observational study. We included patients with active pulmonary tuberculosis aged ≥65 years who required inpatient treatment between 30 April 2021 and 30 November 2022. We assessed sarcopenia using SARC-F, and SARC-F ≥ 4 points at admission was defined as a high risk of sarcopenia. The primary outcome was all-cause mortality during hospitalisation. We extracted information on age, sex, body mass index, comorbidities, blood and biochemical tests, modified Glasgow Prognostic Score, calf circumference, geriatric nutritional risk index, physiotherapy, and length of hospital stay from medical records.
Results:
We included 147 patients (mean age: 83.0 ± 7.8 years; males: 61.9%). Ninety-three (63.3%) patients had a high risk of developing sarcopenia. Patients with a high risk of sarcopenia were significantly older (mean: 85.0 ± 7.1 years), had a lower body mass index (median: 18.1 kg/m2, range: 16.1-20.5 kg/m2), had a higher modified Glasgow Prognostic Score (median: 2, range: 2-2), and had a lower calf circumference (mean: 26.8 ± 3.6 cm), had a lower geriatric nutritional risk index (mean: 72.2 ± 12.9) than those without high-risk sarcopenia. More patients with a high risk of sarcopenia underwent physiotherapy (93.5%) than those without high-risk sarcopenia (P < 0.01, all). Kaplan-Meier survival curves showed that patients with a high risk of sarcopenia had significantly lower overall survival than those without high-risk sarcopenia (log-rank test, P = 0.001). Logistic regression analysis for in-hospital mortality showed that a high risk of sarcopenia significantly affected in-hospital mortality (odds ratio [OR]: 6.425, 95% confidence interval [CI]: 1.399-47.299). In addition, logistic regression analysis for each item of SARC-F showed that assistance in walking (OR: 3.931, 95% CI: 1.816-9.617) and rising from a chair (OR: 2.458, 95% CI: 1.235-5.330) significantly affected in-hospital mortality.
Conclusion:
A high risk of sarcopenia, as assessed using SARC-F at admission, was a risk factor for in-hospital mortality in older patients with pulmonary tuberculosis. Among the SARC-F items, assistance in walking and rising from a chair were the risk factors for in-hospital mortality.

Related Concept Videos
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:30
Pneumonia III: Complications and Assessment
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...