Related Experiment Video
Updated: Jun 30, 2025
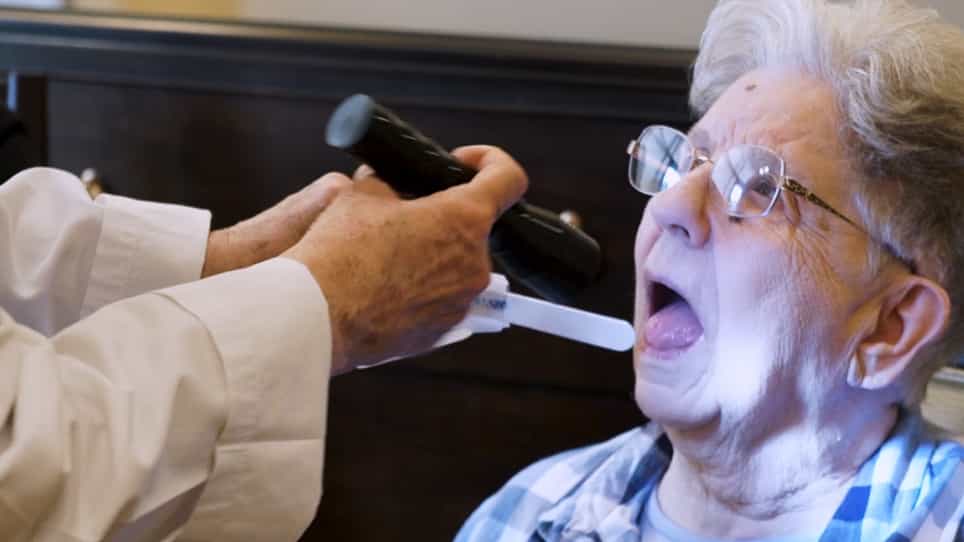

Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Social Disadvantage and Multimorbidity Including Oral Conditions in the United States
A Mirza1, R G Watt1, A Heilmann1
1Department of Epidemiology and Public Health, University College London, London, UK.

Abstract:
Existing studies on multimorbidity have largely excluded oral diseases in multimorbidity prevalence estimates. The reason behind this is somewhat unclear, as chronic oral conditions are highly prevalent, affecting over half the global population. To address this gap, we examined the relationship between social disadvantage and multimorbidity, stratifying by the inclusion and exclusion of oral conditions. For participants aged 30 y and over (n = 3,693), cross-sectional analysis was carried out using the US National Health and Nutrition Survey (2013-2014). Multimorbidity was defined as having 2 or more chronic conditions. Five medical conditions were examined: diabetes, asthma, arthritis, cardiovascular disease, and depression, as well as 4 oral health conditions: caries, periodontal disease, number of teeth, and edentulousness. Education and income poverty ratio were selected as measures of social disadvantage. Multimorbidity prevalence estimates according to social disadvantage were analyzed on an absolute and relative scale using inverse probability treatment weighting (IPTW), adjusting for age, sex, and ethnicity. The inclusion of oral health conditions in the assessment of multimorbidity increased the overall prevalence of multimorbidity from 20.8% to 53.4%. Findings from IPTW analysis demonstrated clear social gradients for multimorbidity estimates stratified by the exclusion of oral conditions. Upon inclusion of oral conditions, the prevalence of multimorbidity was higher across all social groups for both education and income. Stratifying by the inclusion of oral conditions, the mean probability of multimorbidity was 27% (95% confidence interval [CI], 23%-30%) higher in the low-education group compared to the high-education group. Similarly, the mean probability of multimorbidity was 44% (95% CI, 40%-48%) higher in the low-income group. On a relative scale, low education was associated with a 1.52 times (95% CI, 1.44-1.61) higher prevalence of multimorbidity compared to high education. Low income was associated with a 2.18 (95% CI, 1.99-2.39) higher prevalence of multimorbidity. This novel study strongly supports the impact of chronic oral conditions on multimorbidity prevalence estimates.


Related Concept Videos
 01:18
Factors Affecting Illness
For instance, risk factors are connected to illness,...
 01:26
Assessment of the Mouth
Mouth Inspection
The inspection begins with visually examining the mouth for symmetry, color, and size.
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:21
Dimensions of Health and Illness
 01:20
Lifestyle Factors and Health
Benefits of Physical Activity
Physical activity, whether through structured exercise or casual activities like walking, biking, or dancing, is a cornerstone of a...
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...