Related Experiment Video
Updated: Jun 30, 2025
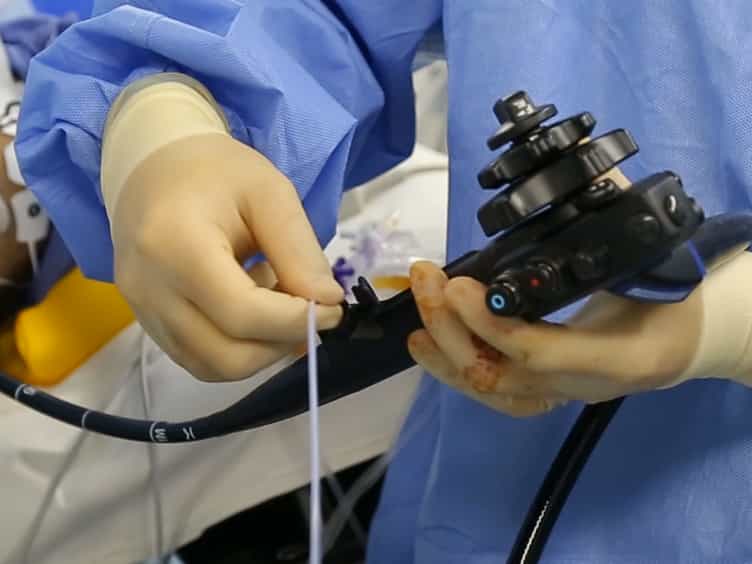

Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
How-I-do-it: laparoscopic intragastric submucosal dissection (LISD) for gastric and gastro-oesophageal junction early
Maira Farrukh1, Barbara Braden2, Bruno Sgromo3
1Digestive Endoscopy Unit, G. Bernabeo Hospital, Ortona, Italy. maira.farrukh@yahoo.it.

Purpose:
Laparoscopic intragastric submucosal dissection (LISD) is a novel approach to the resection of gastric lesion that are not amenable to conventional endoscopic approaches. The technique permits favourable access to lesions situated at the cardia and angular notch of the stomach, enables en-bloc resection of large areas of tissue, and can prevent the need of formal gastrectomy or oesophagectomy in selected patients.
Methods:
All cases were deemed suitable for LISD by a multidisciplinary team panel following endoscopic assessment (using white light enhancement, chromoendoscopy and magnification endoscopy) that was integrated when needed with EUS, CT scan or PET scan. The surgical technique consisted in a 3-port laparoscopic approach; after establishment of pneumoperitoneum, three gastrotomies were performed to enable port insertion into the stomach. Following establishment of stable pneumogastrium, the area of interest was identified, submucosal hyaluronic acid injection performed to provide a cushion in the plane of dissection, and the excision area was circumferentially marked with cautery. Resection was completed using cautery hook, along a plane parallel to the muscolaris propria. After the specimen was extracted in a retrieval bag, intracorporeal single layer running suture closure of gastrotomies was performed. The abdominal wall closed by layers and tap block performed along with local anaesthetic injection on skin incision. Measures were taken to ensure correct orientation of resected specimens prior to fixation.
Results:
During the study period that spans from 2014 and 2022, a total of 11 patients underwent LISD for limited lesions of the stomach, 10 were located at gastro-oesophageal junction and one at the angular incisura. Four patients were female, seven males. The median age was 74 (46-79) years. R0 resection rate was 54.5%. Mean operative time was 109 min with very low blood loss (10 ml). Mortality rate was 0%, no immediate major complications (Grade II-V Clavien Dindo), including haemorrhage or perforation, occurred in these cases. Two patients developed dysphagia later that was successfully treated with endoscopic balloon dilatations. Median hospital stay was 3 days and median oral intake was on day 1 post-procedural.
Conclusions:
Laparoscopic intragastric submucosal dissection is shown to be a safe and effective intervention for the treatment of early gastric cancers in selected patients having undergone deemed not amenable for endoscopic submucosal resection for their technically challenging location. Its application can serve as route to avoid formal surgery and the associated morbidity.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: