Related Experiment Video
Updated: Jun 30, 2025
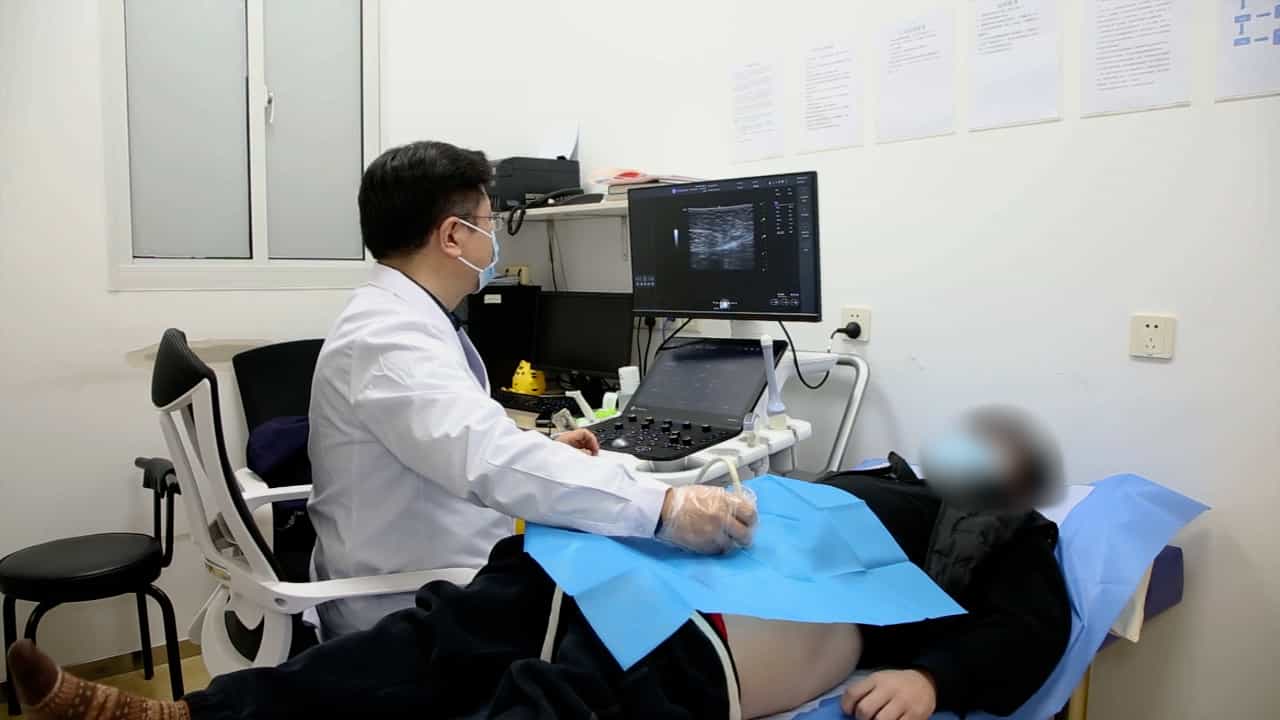

Combined Supine and Standing Imaging for Varicocele: An Improved Diagnostic Approach
Published on: November 22, 2024
[Impact of the Reflux Origin on the Clinical Stage and Surgical Decision in Primary Varicose Veins]
Christoph Wilmanns1, Ulrich Zechner2,3, Paul Karl Walter4
1Klinik für Gefäß-, endovaskuläre und Thoraxchirurgie, Schön Klinik Rendsburg, Rendsburg, Deutschland.

Abstract:
Reflux and recirculation in primary varicose veins are not yet completely understood, and the contribution of perforator veins is dual.Reflux origin was assessed as junctional (JP, reflux of the greater saphenous junction or groin recurrences) with/without suspect perforator veins (SPV), or perforator phenotype (PP, reflux from SPV only or for statistical purposes from the small saphenous vein). Flow direction and intensity were recorded under Valsalva (JP) or as spontaneous/under distal compression/decompression (SPV) and weighted with one/two points as reflux/reentry, respectively, in the case of SPV. We compared the origin and extent of axial reflux and diameter/flow direction of SPV with the clinical stage by multivariate analysis.Of 107 limbs, 68 presented with JP, 49 combined with SPV, and 39 with PP. CEAP C3-C6 was associated with the presence of SPV (JP and PP) in 45/65 (11/22) limbs with primaries (recurrences) or in 3/16 (0/4), p < 0.01 (p = 0.01), without SPV. C4-C6 at first manifestation, however, was more frequent in JP and axial reflux below the knee in 14/39 limbs (p = 0.01) or above the knee in 3/11 (p = 0.12) compared with PP (5/31). SPV flow at first manifestation was reentry in the case of JP and axial reflux below the knee (estimate -1.62, p = 0.02) or above the knee (0.29, p = 0.81) compared with PP, but diameter of the most dilated perforator vein was higher in the case of JP and axial reflux above the knee (estimate 0.20, p < 0.01) or below the knee (0.04, p = 0.30) compared with PP. Predominant SPV flow was reentry/reflux during peripheral compression/decompression, respectively (p = 0.009).The data suggest that the reflux origin and extent of axial reflux are associated with diameter/flow direction of SPV and clinical stage in primary varicose veins.
More Related Videos

Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...