Related Experiment Video
Updated: Jun 29, 2025
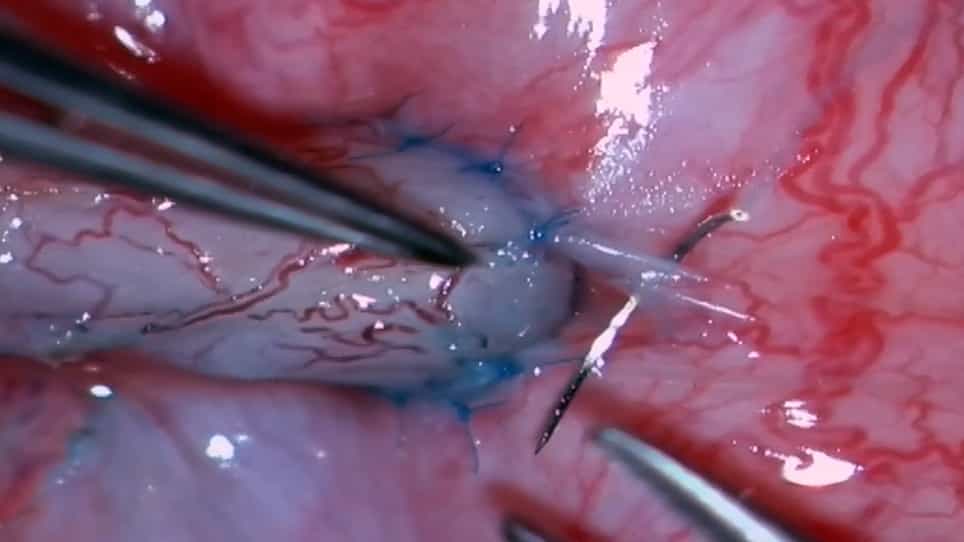

Vessel-Sparing Microsurgical Longitudinal Intussusception Vasoepididymostomy to Treat Epididymal Obstructive Azoospermia
Published on: May 27, 2022
Prevalence and clinical implications of biochemical hypogonadism in patients with nonobstructive azoospermia
Arnold P P Achermann1,2, Sandro C Esteves1,2,3
1ANDROFERT, Andrology and Human Reproduction Clinic, Campinas, São Paulo, Brazil.

Objective:
To investigate the prevalence and clinical implications of biochemical hypogonadism in infertile men with nonobstructive azoospermia (NOA).
Design:
Cohort study.
Setting:
University-affiliated tertiary center for male reproductive health.
Patients:
767 consecutive normogonadotropic or hypergonadotropic patients with NOA undergoing infertility evaluation from 2014 to 2021.
Intervention:
Patients aged 23-55 years underwent comprehensive clinical, hormonal, genetic, semen analysis, and histopathology evaluations and were classified on the basis of predefined baseline follicle-stimulating hormone (12 IU/L) and total testosterone (350 ng/dL) serum levels cutpoints into four groups: hypergonadotropic hypogonadal, hypergonadotropic eugonadal, normogonadotropic hypogonadal, and normogonadotropic eugonadal. All patients were naïve regarding previous sperm retrieval (SR) or hormonal therapy use.
Main Outcome Measures:
The period prevalence of biochemical hypogonadism, defined as testosterone levels of <350 ng/dL, and the distribution of patients per group were computed. The associations between hypogonadism, clinical factors, and SR success were evaluated using multivariable logistic regression analyses. Adjusted relative risks (aRRs) and 95% confidence intervals (CIs) were estimated to assess the association between SR and patient classification.
Results:
The overall period prevalence of biochemical hypogonadism was 80.8% (95% CI 77.9%-83.4%). The prevalence of patients by group was hypergonadotropic hypogonadal (42.4%, 38.9%-45.9%), normogonadotropic hypogonadal (38.5%; 35.1%-41.9%), hypergonadotropic eugonadal (8.3%; 6.6%-10.5%), and normogonadotropic eugonadal (10.8%; 8.8%-13.2%). Reduced testicular volume and lower estradiol levels were associated with an increased likelihood of hypogonadism. Paternal age was also an independent predictor, with higher age linked to an increased likelihood of hypogonadism. Hypogonadism was less likely in patients with germ cell maturation arrest and more likely in those with Sertoli cell-only. Patients with hypergonadotropic hypogonadism had lower SR success than normogonadotropic eugonadal counterparts (aRR 0.611; 95% CI 0.398-0.855). In the subset of hypogonadal men, hypergonadotropic patients had lower SR success than normogonadotropic participants (aRR 0.632; 0.469-0.811).
Conclusion:
The prevalence of biochemical hypogonadism among men with NOA is substantial. Hypogonadism is associated with testicular volume, estradiol levels, age, and histopathology patterns. This condition impacts SR success and emphasizes the need for improved care for men with NOA.

Related Concept Videos
 01:23
Infertility in Males
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra....
 01:28
Infertility in Females
Endometriosis, a condition characterized by abnormal growth of...
 01:41
Spermatogenesis
 02:07
Oogenesis
 01:28
Menopause