Related Experiment Video
Updated: Jun 29, 2025
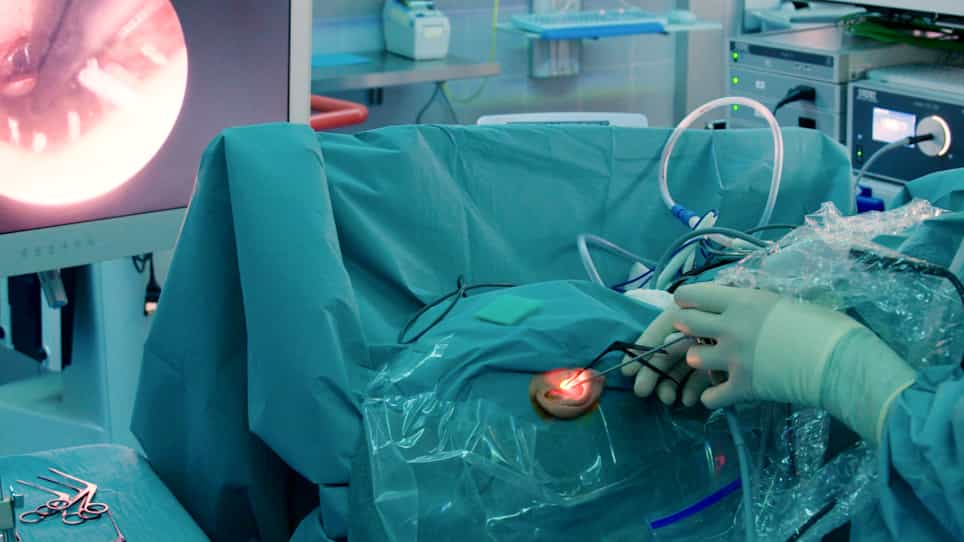
Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
The Role of Endoscopic Assistance in Surgery for Pediatric Cholesteatoma in Reducing Residual and Recurrent Disease
Nader Nassif1, Luca Oscar Redaelli de Zinis1,2
1Department of Otolaryngology Head and Neck Surgery, Children Hospital, 25100 Brescia, Italy.

Insights
This study on pediatric acquired cholesteatoma surgery found that while overall relapse rates are high, endoscopic assistance significantly reduces residual disease. Surgical approach impacts recurrence, with canal wall-down tympanomastoidectomy showing lower rates.
Area of Science:
- Otolaryngology
- Pediatric Surgery
- Surgical Oncology
Background:
- Acquired cholesteatoma in children poses challenges for complete eradication.
- Long-term outcomes vary significantly based on surgical technique.
- Understanding recurrence and residual disease patterns is crucial for optimizing pediatric cholesteatoma management.
Purpose of the Study:
- To evaluate long-term recurrent and residual disease after pediatric acquired cholesteatoma surgery.
- To compare outcomes across different surgical approaches: canal wall-up tympanomastoidectomy (CWUT), transcanal exclusive endoscopic approach (TEEA), and canal wall-down tympanomastoidectomy (CWDT).
- To assess the impact of endoscopic assistance on surgical outcomes.
Main Methods:
- Retrospective analysis of 71 interventions in 67 pediatric patients.
- Surgical approaches included CWUT (with/without endoscopy), TEEA, and CWDT.
- Kaplan-Meier method used to estimate long-term disease relapse, recurrence, and residual rates.
Main Results:
- Overall 12-year cholesteatoma relapse rate was 47±6%, with recurrence at 28±6% and residual disease at 26±5%.
- Relapse rates varied by approach: CWDT (33±11%), CWUT (60±9%), TEEA (40±11%). Recurrence rates were CWDT (0%), CWUT (42±9%), TEEA (32±11%).
- Endoscopic assistance significantly reduced residual disease (9±5% with vs. 42±8% without), but did not impact recurrence rates.
Conclusions:
- CWDT remains a viable option for extensive cholesteatomas.
- TEEA is recommended for smaller cholesteatomas to minimize morbidity.
- Endoscopic assistance is beneficial for reducing residual disease in CWUT, aiding complete cholesteatoma removal in pediatric patients.
Abstract:
The primary aim of this study was to evaluate long-term recurrent and residual disease after surgery for acquired cholesteatoma in children according to surgical approach. A total of 71 interventions performed on 67 pediatric patients were included in the study. Canal wall-up tympanomastoidectomy (CWUT) was performed in 31 ears (13 with endoscopic assistance), a transcanal esclusive endoscopic approach (TEEA) was used in 22, and canal wall-down tympanomastoidectomy (CWDT) was performed in 18. Overall, the cholesteatoma relapse rate estimated by the Kaplan-Meier method was 47 ± 6% at 12 years; the recurrent cholesteatoma rate was 28 ± 6% and the residual cholesteatoma rate was 26 ± 5%. The relapse rate according to surgical approach was 33 ± 11% for CWDT, 60 ± 9% for CWUT, and 40 ± 11% for TEEA (p = 0.04). The difference for recurrent disease was no recurrent disease for CWDT, 42 ± 9% for CWUT, and 32 ± 11% for TEEA (p = 0.01). The residual disease rate was significantly reduced with endoscopy: 42 ± 8% without endoscopy vs. 9 ± 5% with (p = 0.003). CWDT can still be considered in primary surgery in case of extensive cholesteatomas and small mastoid with poor pneumatization. TEEA can be recommended for small cholesteatoma not extending to the mastoid to reduce morbidity. Endoscopic assistance seems useful to reduce residual disease in CWUT, whereas it does not have a significant impact on preventing recurrent disease.
Related Concept Videos
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: