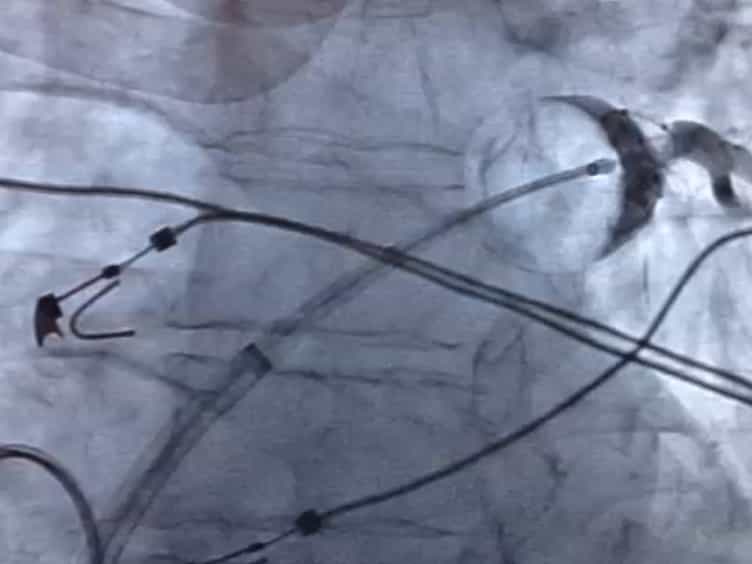

Ultra-Low-Temperature Cryoablation for Ventricular Tachycardia: An Early Single-Centre Report of Acute Results
Paula Sanchez-Somonte1,2, Atul Verma1, Luiz-Gustavo Bravosi Da Rosa1
1Division of Cardiology, McGill University Health Centre, McGill University, Montréal, Québec, Canada.

Background:
Endocardial catheter ablation for ventricular tachycardia (VT) may fail because of the inability to deliver transmural lesions. Ultra-low-temperature cryoablation (ULTC) uses near-critical nitrogen and can generate temperatures as low as -196 °C. We report a series of 18 patients who underwent ULTC at the McGill University Health Centre (MUHC), representing the largest single-centre experience to date.
Methods:
Eighteen patients with monomorphic drug-refractory VT underwent VT ablation with ULTC at our institution as part of the first-in-human CryoCure-VT trial (NCT04893317). After voltage map, the mapping catheter was replaced with the ULTC catheter, and lesions were applied over a fixed duration of time (60-180 seconds), followed by a 60-second thaw and another application at the original duration (freeze-thaw-freeze). Duration of ablation time was selected depending on the wall thickness of the left ventricle monitored with intracardiac echo to achieve tissue depths of 4.5 to 7.5 mm.
Results:
Baseline left ventricular ejection fraction was 32%, mean age 71 years, 94% were male. A total of 32 sustained VTs were induced in 16 of 18 patients. A total of 177 cryoablation lesions were delivered (9.8 lesions per patient). Of the 16 patients with inducible VT, 15 (94%) were rendered noninducible postablation, and 1 was inducible only for a nonclinical VT. Complications included 1 pericardial effusion that required drainage. From 18 patients, 16 (89%) were discharged within the first 24 hours postablation.
Conclusions:
ULTC is feasible and permits acute control of monomorphic VT during VT ablation procedures in drug-refractory patients.
More Related Videos
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
 06:25
Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
Related Concept Videos
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Introduction Cardiac Emergencies
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy