

A Single High-Sensitivity Cardiac Troponin T Strategy for Ruling Out Myocardial Infarction
Patrik Gilje1, Moman A Mohammad1, Andreas Roos2,3
1Lund University, Skåne University Hospital, Department of Cardiology, Lund, Sweden.

Insights
A higher threshold of 9 ng/L for high-sensitivity cardiac troponin T (hs-cTnT) can safely rule out acute myocardial infarction (AMI) in emergency department patients. This approach identifies more low-risk individuals than current methods, improving efficiency in diagnosing chest pain.
Area of Science:
- Cardiology
- Emergency Medicine
- Biomarker Research
Background:
- Ruling out acute myocardial infarction (AMI) in the emergency department (ED) presents diagnostic challenges.
- Current guidelines suggest using high-sensitivity cardiac troponin T (hs-cTnT) levels below 5 ng/L or 6 ng/L at presentation to exclude AMI.
- The need for more efficient and accurate diagnostic thresholds for AMI in the ED is recognized.
Purpose of the Study:
- To determine if a higher hs-cTnT threshold can be safely employed for ruling out AMI in the ED.
- To evaluate the negative predictive value (NPV) of elevated hs-cTnT concentrations for AMI and all-cause death.
- To compare the effectiveness of a higher hs-cTnT threshold against existing thresholds.
Main Methods:
- A derivation cohort of 24,973 ED patients with chest pain was analyzed.
- The highest 0-hour hs-cTnT concentration achieving an NPV of ≥99.5% for AMI/30-day all-cause death was identified.
- Validation was performed in two independent cohorts totaling 132,021 and 1167 ED chest pain patients.
Main Results:
- A 0-hour hs-cTnT threshold of <9 ng/L demonstrated an NPV of 99.6% for the primary endpoint.
- This <9 ng/L cutoff identified 59.7% of patients as low risk, significantly higher than the <5 ng/L (35.8%) and <6 ng/L (43.9%) cutoffs.
- Similar performance was observed in validation cohorts, with improved efficacy in specific subgroups like those with later hs-cTnT measurement or non-high-risk profiles.
Conclusions:
- A 0-hour hs-cTnT cutoff of <9 ng/L safely rules out AMI and 30-day death in a majority of chest pain patients.
- This higher threshold represents a more effective strategy for identifying low-risk patients compared to current <5 ng/L and <6 ng/L cutoffs.
- The study provides evidence for optimizing AMI rule-out protocols in the emergency department.
Background:
Ruling out acute myocardial infarction (AMI) in the emergency department (ED) is challenging. Studies have shown that a high-sensitivity cardiac troponin T (hs-cTnT) <5 ng/L or <6 ng/L at presentation (0 h) can be used to rule out AMI. The objective of this study was to identify whether an even higher hs-cTnT threshold can be used for a safe rule out of AMI in the ED.
Methods:
The derivation cohort consisted of 24,973 ED patients with a primary complaint of chest pain. In this cohort, we identified the highest concentration of 0 h hs-cTnT that corresponded to a negative predictive value (NPV) of ≥99.5% for the primary endpoint of AMI/all-cause death within 30 days and the secondary endpoint of all-cause death within one year. The results were validated in two cohorts consisting of 132,021 and 1167 ED chest pain patients.
Results:
The 0 h hs-cTnT threshold corresponding to a NPV of ≥99.5% for the primary endpoint was <9 ng/L (NPV: 99.6% and 95% CI: 99.5-99.7). This cutoff provided a sensitivity of 96.2% (95% CI: 95.2-97.1) and identified 59.7% of the patients as low risk compared to 35.8% and 43.9% with a 0 h hs-cTnT <5 ng/L and <6 ng/L, respectively. The results were similar in the validation cohorts and seemed to perform even better in patients where the 0 h hs-cTnT was measured >3 h after symptom onset and in those with a nonischemic ECG and nonhigh risk history.
Conclusions:
A 0 h hs-cTnT cutoff of <9 ng/L safely rules out AMI/death within 30 days in a majority of chest pain patients and is a more effective strategy than the currently recommended <5 ng/L and <6 ng/L cutoffs. This trial is registered with NCT03421873.
More Related Videos
 10:12
A Sensitive and Specific Quantitation Method for Determination of Serum Cardiac Myosin Binding Protein-C by Electrochemiluminescence Immunoassay
Published on: August 8, 2013
 09:23
Using Extraordinary Optical Transmission to Quantify Cardiac Biomarkers in Human Serum
Published on: December 13, 2017
Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:26
Exercise Stress Test
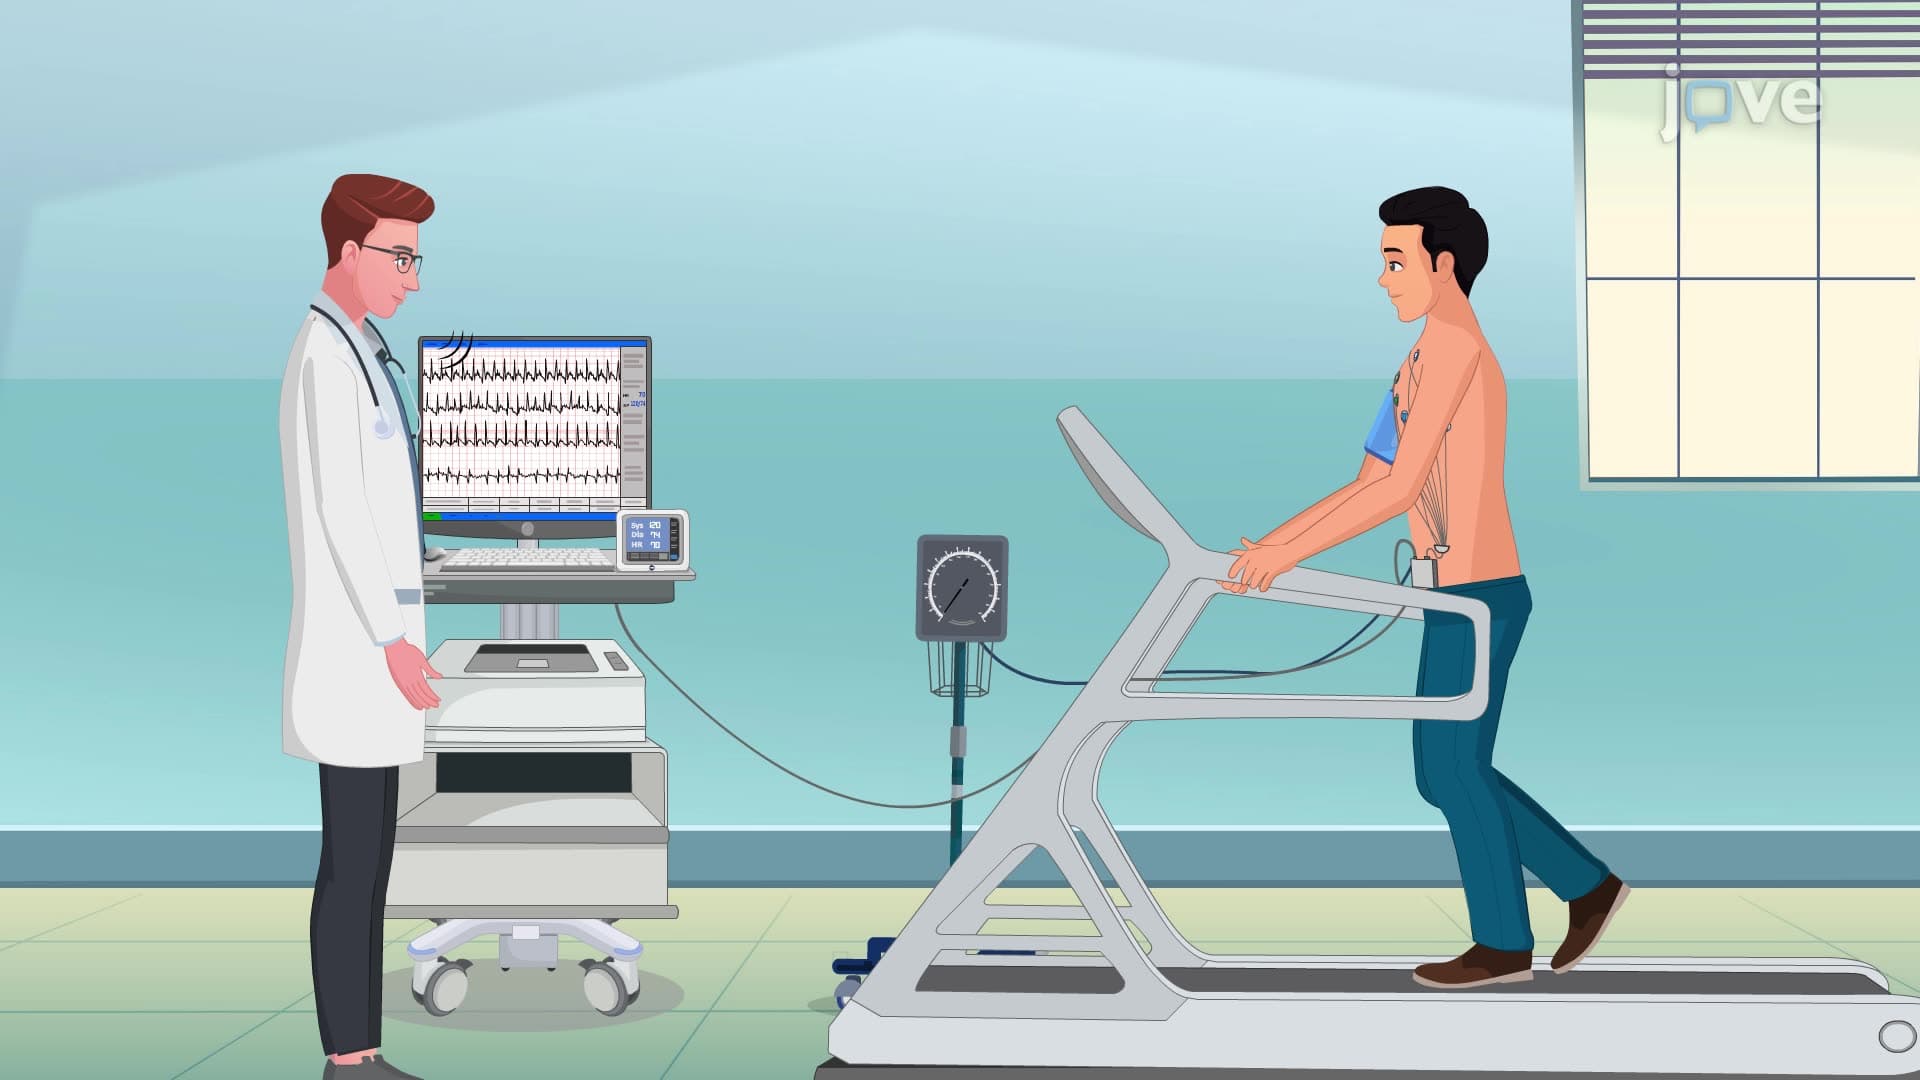
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes