Related Experiment Video
Updated: Jun 29, 2025


Competitive Transplants to Evaluate Hematopoietic Stem Cell Fitness
Published on: August 31, 2016
Lesson learned in pediatric haploidentical transplantation in a low-resource environment: delivering melphalan IV and
Valentine Jiménez-Antolinez1, Julia Colunga-Pedraza1, Andrés Gómez-De León1
1Facultad de Medicina y Hospital Universitario "Dr. José Eleuterio González", Universidad Autónoma de Nuevo León, Monterrey, Mexico.

Insights
Modifying the conditioning regimen for pediatric haplo-HSCT significantly reduced primary graft failure (PGF). Switching from busulfan to melphalan and adding TBI improved patient survival rates in hematologic malignancy cases.
Area of Science:
- Pediatric Hematology
- Transplant Immunology
- Oncology
Background:
- Primary graft failure (PGF) is a critical complication following hematopoietic stem-cell transplant (HSCT), particularly in pediatric patients with hematologic malignancies.
- Previous reports indicated PGF incidence in haplo-HSCT ranging from 0% to 30%, but our institution observed a 35% incidence in 2018.
- This high PGF rate necessitated a review and modification of the conditioning regimen.
Purpose of the Study:
- To evaluate the impact of conditioning regimen modifications on the incidence of primary graft failure (PGF) in pediatric haplo-HSCT recipients.
- To assess the effect of these changes on overall survival rates in this patient population.
Main Methods:
- A single-center, prospective, pre-post study design was employed, analyzing consecutive pediatric patients (<16 years) with hematologic malignancies undergoing haplo-HSCT from January 2015 to December 2022.
- Patients were divided into two groups: G1 (n=26) received a myeloablative conditioning regimen (Flu/Cy/Bu) before September 2018, and G2 (n=36) received a reduced-intensity regimen (Flu/Cy/Mel/TBI2) after September 2018.
- Key modifications included switching from busulfan to melphalan and incorporating TBI when feasible.
Main Results:
- The incidence of PGF was significantly reduced from 35% (9 out of 26 patients) in G1 to 0% in G2 (p < 0.001).
- Overall survival at 12 months improved from 63% in G1 to 85% in G2 (p=0.007), and at 24 months from 47% to 70% respectively.
- Median follow-up was 15.9 months for G1 and 24.8 months for G2.
Conclusions:
- Modifications to the conditioning regimen, specifically replacing busulfan with melphalan and adding TBI, effectively eliminated primary graft failure in pediatric haplo-HSCT.
- These regimen changes have led to significant improvements in overall survival for pediatric patients with hematologic malignancies undergoing haplo-HSCT.
- The findings support the optimization of conditioning protocols to enhance outcomes in pediatric HSCT.
Abstract:
Objectives: Primary graft failure (pGF) after hematopoietic stem-cell transplant is associated with considerable morbidity and mortality. The incidence in haplo-HSCT has been reported to be between 0% and 30%. In 2018, we identified a pGF incidence of 35% in our pediatric haplo-HSCT recipients with hematologic malignancies, which motivated us to enact changes to the conditioning regimen.Methods: We performed a single-center prospective, pre-post study of consecutive patients under 16 years with hematologic malignancies, from January 2015 to December 2022 who received a haplo-HSCT. Twenty-six pediatric patients received a haplo-HSCT before September 2018 (G1) and 36 patients after (G2). The main conditioning regimen for G1 was myeloablative with Flu/Cy/Bu, and for G2 the main regimen was reduced intensity Flu/Cy/Mel/TBI2.Results: Nine patients (35%) in G1 had primary graft failure, while in G2 there were no patients with pGF. The median follow-up for G1 was 15.9 months, and for G2 was 24.8 months, with an estimated overall survival at 12 months of 63% (95% CI 47-76) versus 85% (95% CI 73-93), and at 24 months of 47% (95% CI 31-64) versus 70% (95% CI 54-82) respectively (p = .007).Conclusion: After September 2018 conditioning regimen modifications were implemented with the objective of reducing primary failure, consisting mainly of switching from busulfan to melphalan as the alkylating agent of choice, and adding, when clinically possible TBI. Primary failure has been significantly reduced in our institution since then.
More Related Videos
 11:55
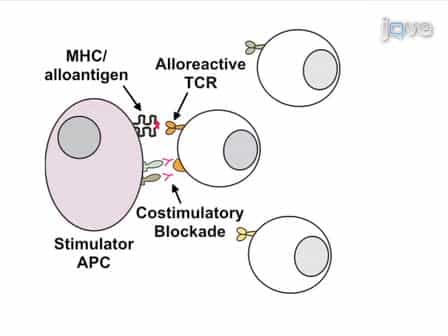
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
 08:05
Bone Marrow Transplantation Platform to Investigate the Role of Dendritic Cells in Graft-versus-Host Disease
Published on: March 17, 2020
Related Concept Videos
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...