Related Experiment Video
Updated: Jun 29, 2025


E-Patient Counseling Trial E-PACO: Computer Based Education versus Nurse Counseling for Patients to Prepare for Colonoscopy
Published on: August 1, 2019
Implementation of an intervention aimed at deprescribing benzodiazepines in a large US healthcare system using
Tammy M Le1, Scott Campbell2, Alexa Andraos2
1David Geffen School of Medicine, Los Angeles, California, USA.

Objectives:
Long-term benzodiazepine use is common despite known risks. In the original Eliminating Medications Through Patient Ownership of End Results (EMPOWER) Study set in Canada, patient education led to increased rates of benzodiazepine cessation. We aimed to determine the effectiveness of implementing an adapted EMPOWER quality improvement (QI) initiative in a US-based healthcare system.
Design:
We used a pre-post design with a non-randomised control group.
Setting:
A network of primary care clinics.
Participants:
Patients with ≥60 days' supply of benzodiazepines in 6 months and ≥1 risk factor (≥65 years of age, a concurrent high-risk medication prescribed or a diazepam equivalent daily dose ≥10) were eligible.
Intervention:
In March 2022, we engaged 22 primary care physicians (PCPs), and 308 of their patients were mailed an educational brochure, physician letter and flyer detailing benzodiazepine risks; the control group included 4 PCPs and 291 of their patients.
Primary And Secondary Measures:
The primary measure was benzodiazepine cessation by 9 months. We used logistic regression and a generalised estimating equations approach to control for clustering by PCP, adjusting for demographics, frailty, number of risk factors, and diagnoses of arthritis, depression, diabetes, falls, and pain.
Results:
Patients in the intervention and control groups were comparable across most covariates; however, a greater proportion of intervention patients had pain-related diagnoses and depression. By 9 months, 26% of intervention patients (81 of 308) had discontinued benzodiazepines, compared with 17% (49 of 291) of control patients. Intervention patients had 1.73 greater odds of benzodiazepine discontinuation compared with controls (95% CI: 1.09, 2.75, p=0.02). The unadjusted number needed to treat was 10.5 (95% CI: 6.30, 34.92) and the absolute risk reduction was 0.095 (95% CI: 0.03 to 0.16).
Conclusions:
Results from this non-randomised QI initiative indicate that patient education programmes using the EMPOWER brochures have the potential to promote cessation of benzodiazepines in primary care.


Related Concept Videos
 01:14
CNS Depressants: Barbiturates and Benzodiazepines
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...
 01:28
Depressants
Alcohol is a common depressant that can induce a sense of relaxation and reduced inhibition at low doses. Contrary to its occasional...
 01:29
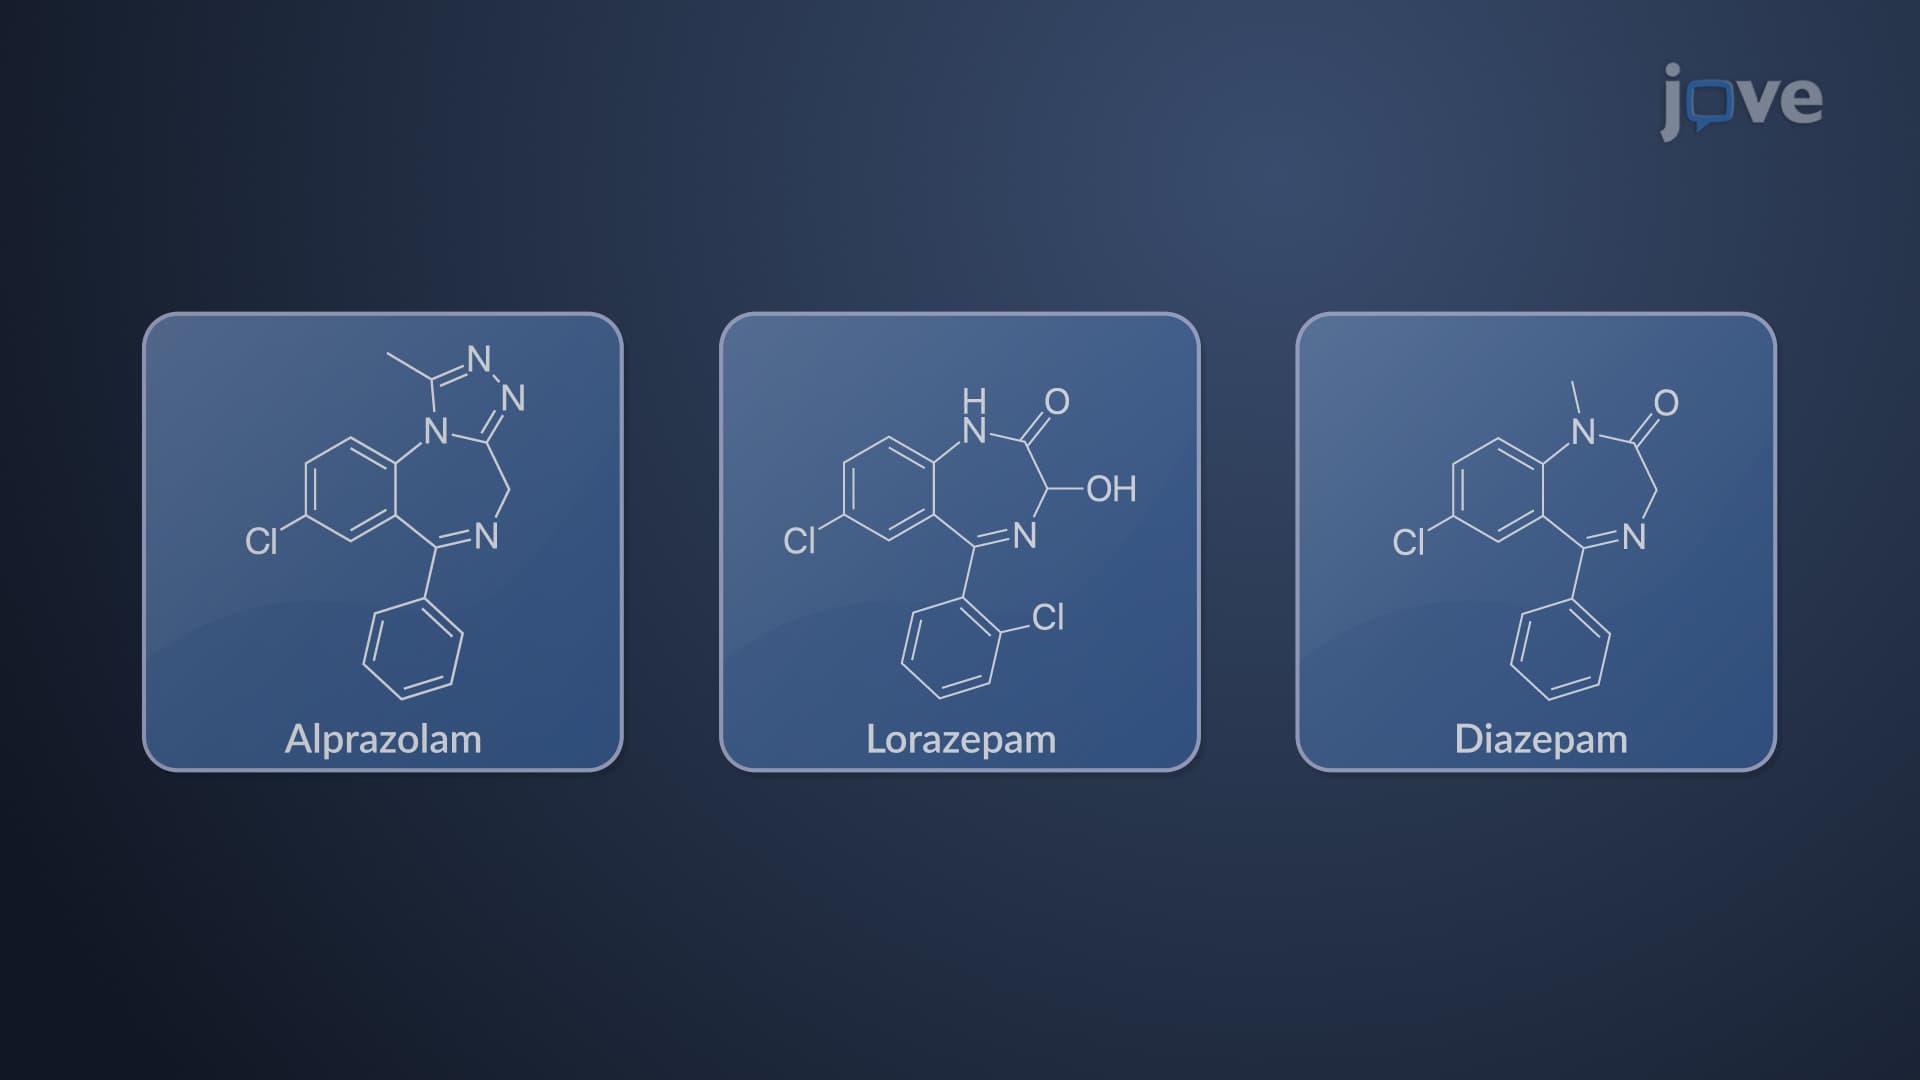
Anxiolytic Drugs: Benzodiazepines and Buspirone
 01:23
Sedatives and Hypnotics: Overview
Sedative-hypnotics are categorized into barbiturates, benzodiazepines (BZDs), and non-benzodiazepines or Z-drugs. These drugs work by suppressing central nervous system activity, and this suppression is dose-dependent. Older sedative medications, like barbiturates, follow a linear curve in...
 01:20
Sedatives and Hypnotics Drugs: Barbiturates