Related Experiment Video
Updated: Jun 29, 2025

Surgical Placement of Catheters for Long-term Cardiovascular Exercise Testing in Swine
Published on: February 9, 2016
The cardiovascular changes underlying a low cardiac output with exercise in patients with type 2 diabetes mellitus
Per Lav Madsen1,2,3, Casper Sejersen3,4, Michael Nyberg5
1Department Cardiology, Herlev-Gentofte Hospital, Copenhagen University, Copenhagen, Denmark.

Abstract:
The significant morbidity and premature mortality of type 2 diabetes mellitus (T2DM) is largely associated with its cardiovascular consequences. Focus has long been on the arterial atheromatosis of DM giving rise to early stroke and myocardial infarctions, whereas less attention has been given to its non-ischemic cardiovascular consequences. Irrespective of ischemic changes, T2DM is associated with heart failure (HF) most commonly with preserved ejection fraction (HFpEF). Largely due to increasing population ages, hypertension, obesity and T2DM, HFpEF is becoming the most prevalent form of heart failure. Unfortunately, randomized controlled trials of HFpEF have largely been futile, and it now seems logical to address the important different phenotypes of HFpEF to understand their underlying pathophysiology. In the early phases, HFpEF is associated with a significantly impaired ability to increase cardiac output with exercise. The lowered cardiac output with exercise results from both cardiac and peripheral causes. T2DM is associated with left ventricular (LV) diastolic dysfunction based on LV hypertrophy with myocardial disperse fibrosis and significantly impaired ability for myocardial blood flow increments with exercise. T2DM is also associated with impaired ability for skeletal muscle vasodilation during exercise, and as is the case in the myocardium, such changes may be related to vascular rarefaction. The present review discusses the underlying phenotypical changes of the heart and peripheral vascular system and their importance for an adequate increase in cardiac output. Since many of the described cardiovascular changes with T2DM must be considered difficult to change if fully developed, it is suggested that patients with T2DM are early evaluated with respect to their cardiovascular compromise.
More Related Videos

Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
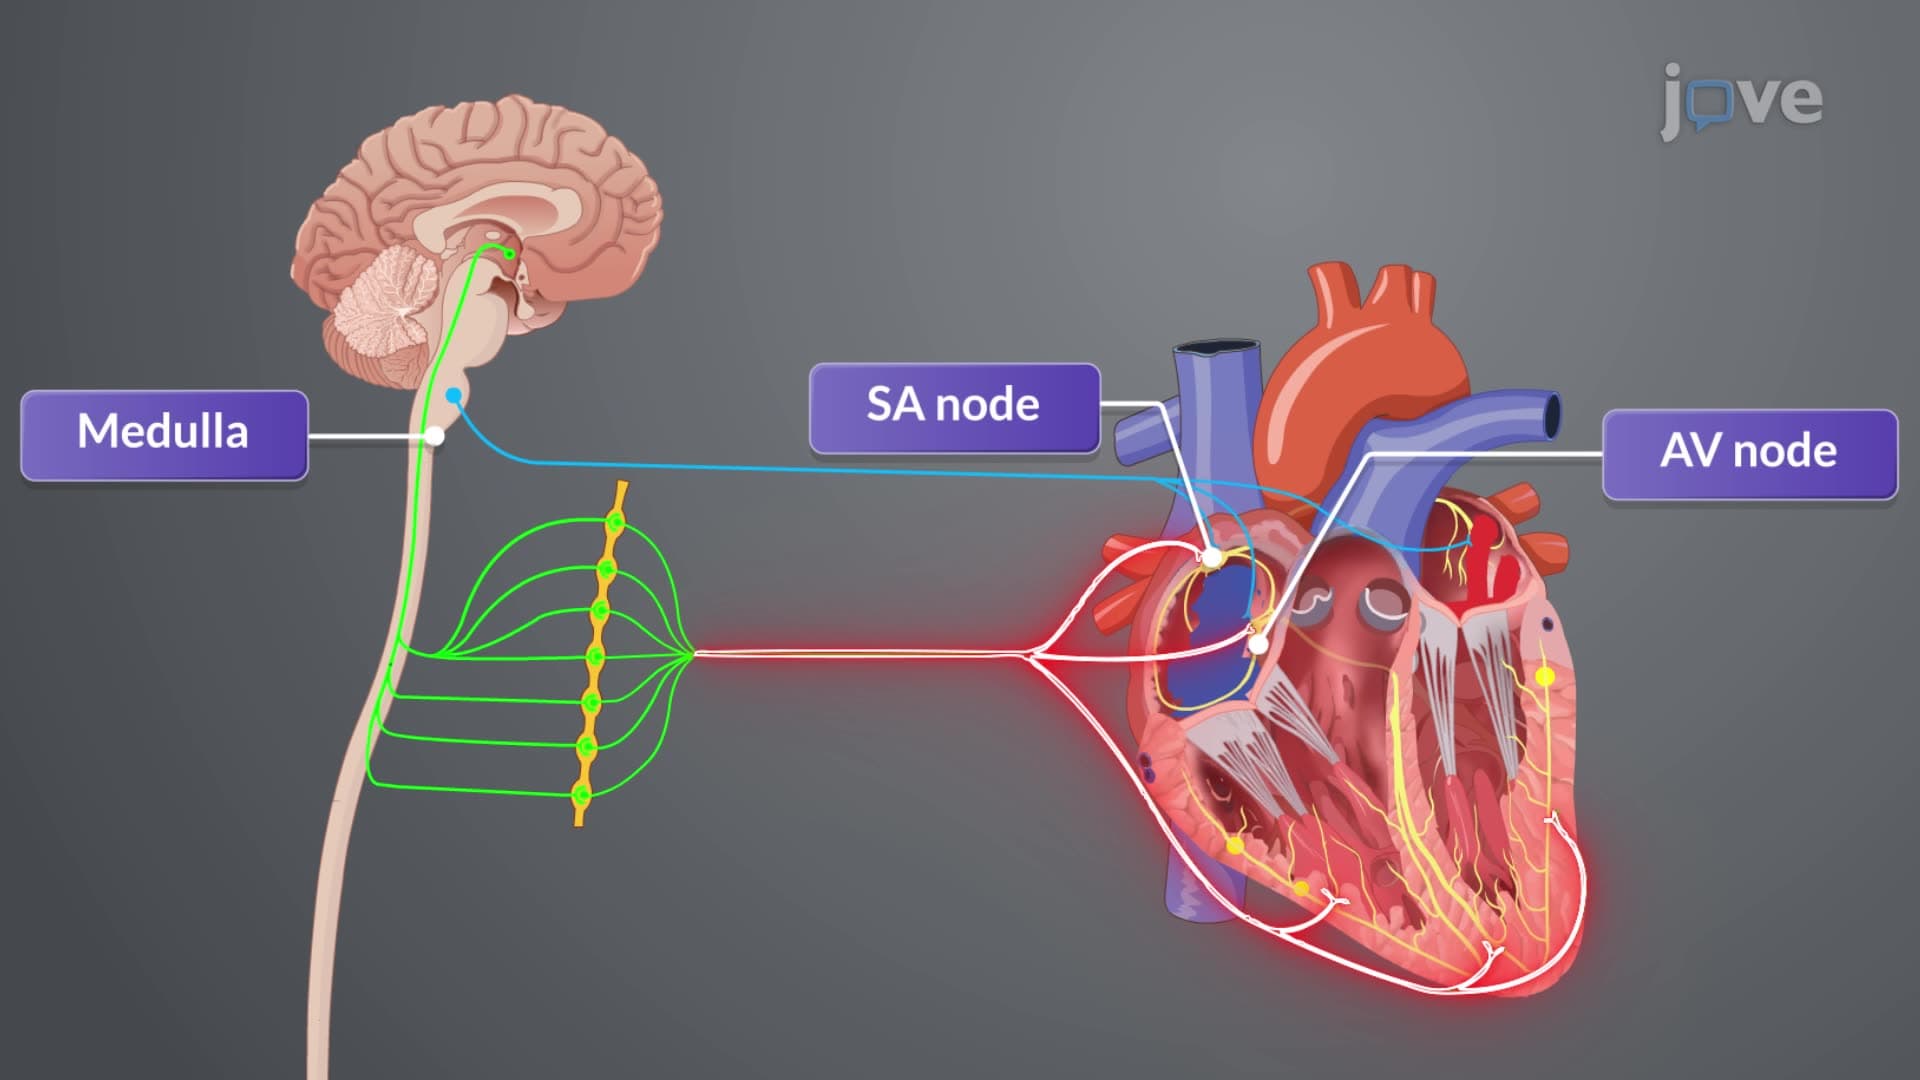
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...