Related Experiment Video
Updated: Jun 29, 2025


Use of Enzymatic Biosensors to Quantify Endogenous ATP or H2O2 in the Kidney
Published on: October 12, 2015
How renal toxins respond to renal function deterioration and oral toxic adsorbent in pH-controlled releasing capsule
Wen-Sheng Liu1,2,3,4,5, Shih-Shin Liang6,7, Mei-Mei Cheng8
1Division of Nephrology, Department of Medicine, Taipei City Hospital, Taipei, Taiwan.

Abstract:
The number of patients with chronic kidney disease (CKD) is increasing. Oral toxin adsorbents may provide some value. Several uremic toxins, including indoxyl sulfate (IS), p-cresol (PCS), acrolein, per- and poly-fluoroalkyl substances (PFAS), and inflammation markers (interleukin 6 [IL-6] and tumor necrosis factor [TNF]-alpha) have been shown to be related to CKD progression. A total of 81 patients taking oral activated charcoal toxin adsorbents (AC-134), which were embedded in capsules that dissolved in the terminal ileum, three times a day for 1 month, were recruited. The renal function, hemoglobulin (Hb), inflammation markers, three PFAS (PFOA, PFOS, and PFNA), and acrolein were quantified. Compared with the baseline, an improved glomerular filtration rate (GFR) and significantly lower acrolein were noted. Furthermore, the CKD stage 4 and 5 group had significantly higher concentrations of IS, PCS, IL-6, and TNF but lower levels of Hb and PFAS compared with the CKD Stage 3 group at baseline and after the intervention. Hb was increased only in the CKD Stage 3 group after the trial (p = .032). Acrolein did not differ between the different CKD stage groups. Patients with improved GFR (responders) (about 77%) and nonresponders had similar baseline GFR. Responders had higher acrolein and PFOA levels throughout the study and a more significant reduction in acrolein, indicating a better digestion function. Both the higher PFOA and lower acrolein may be related to improved eGFR (and possibly to improvements in proteinuria, which we did not measure. Proteinuria is associated with PFAS loss in the urine), AC-134 showed the potential to improve the GFR and decrease acrolein, which might better indicate renal function change. Future studies are needed with longer follow-ups.
Insights
Oral activated charcoal (AC-134) may improve kidney function in chronic kidney disease (CKD) patients by reducing uremic toxins like acrolein. Some patients showed improved glomerular filtration rate (GFR) and hemoglobin levels.
Area of Science:
- Nephrology
- Toxicology
- Gastroenterology
Background:
- Chronic kidney disease (CKD) prevalence is rising globally.
- Uremic toxins (indoxyl sulfate, p-cresol, acrolein, PFAS) and inflammation markers (IL-6, TNF-alpha) are linked to CKD progression.
- Oral toxin adsorbents offer a potential therapeutic avenue for managing CKD.
Purpose of the Study:
- To evaluate the efficacy of oral activated charcoal (AC-134) in improving renal function and reducing uremic toxins in CKD patients.
- To assess the impact of AC-134 on hemoglobin levels, inflammation markers, and specific toxins (PFAS, acrolein).
- To explore correlations between baseline patient characteristics, toxin levels, and treatment response.
Main Methods:
- A prospective study involving 81 CKD patients treated with AC-134 capsules for one month.
- Measurements included renal function (GFR), hemoglobin, inflammation markers, PFAS (PFOA, PFOS, PFNA), and acrolein.
- Patients were stratified by CKD stage (3, 4, 5) and response (responders vs. non-responders based on GFR improvement).
Main Results:
- AC-134 treatment led to a significant improvement in glomerular filtration rate (GFR) and a reduction in acrolein levels.
- CKD stage 4 and 5 patients exhibited higher uremic toxins (IS, PCS, IL-6, TNF) and lower hemoglobin and PFAS compared to stage 3.
- Responders showed higher baseline acrolein and PFOA, with a greater reduction in acrolein, suggesting improved digestive function and potential links to eGFR.
- Hemoglobin increased significantly only in the CKD Stage 3 group post-intervention.
Conclusions:
- Oral AC-134 demonstrates potential in improving GFR and decreasing acrolein, serving as a potential indicator of renal function changes in CKD.
- Higher PFOA and lower acrolein levels may be associated with improved eGFR.
- Further research with longer follow-up periods is warranted to confirm these findings and explore proteinuria associations.
More Related Videos
 08:50
5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
 07:11
Surgical Techniques for Catheter Placement and 5/6 Nephrectomy in Murine Models of Peritoneal Dialysis
Published on: July 19, 2018
Related Concept Videos
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Renal Drug Excretion: Overview
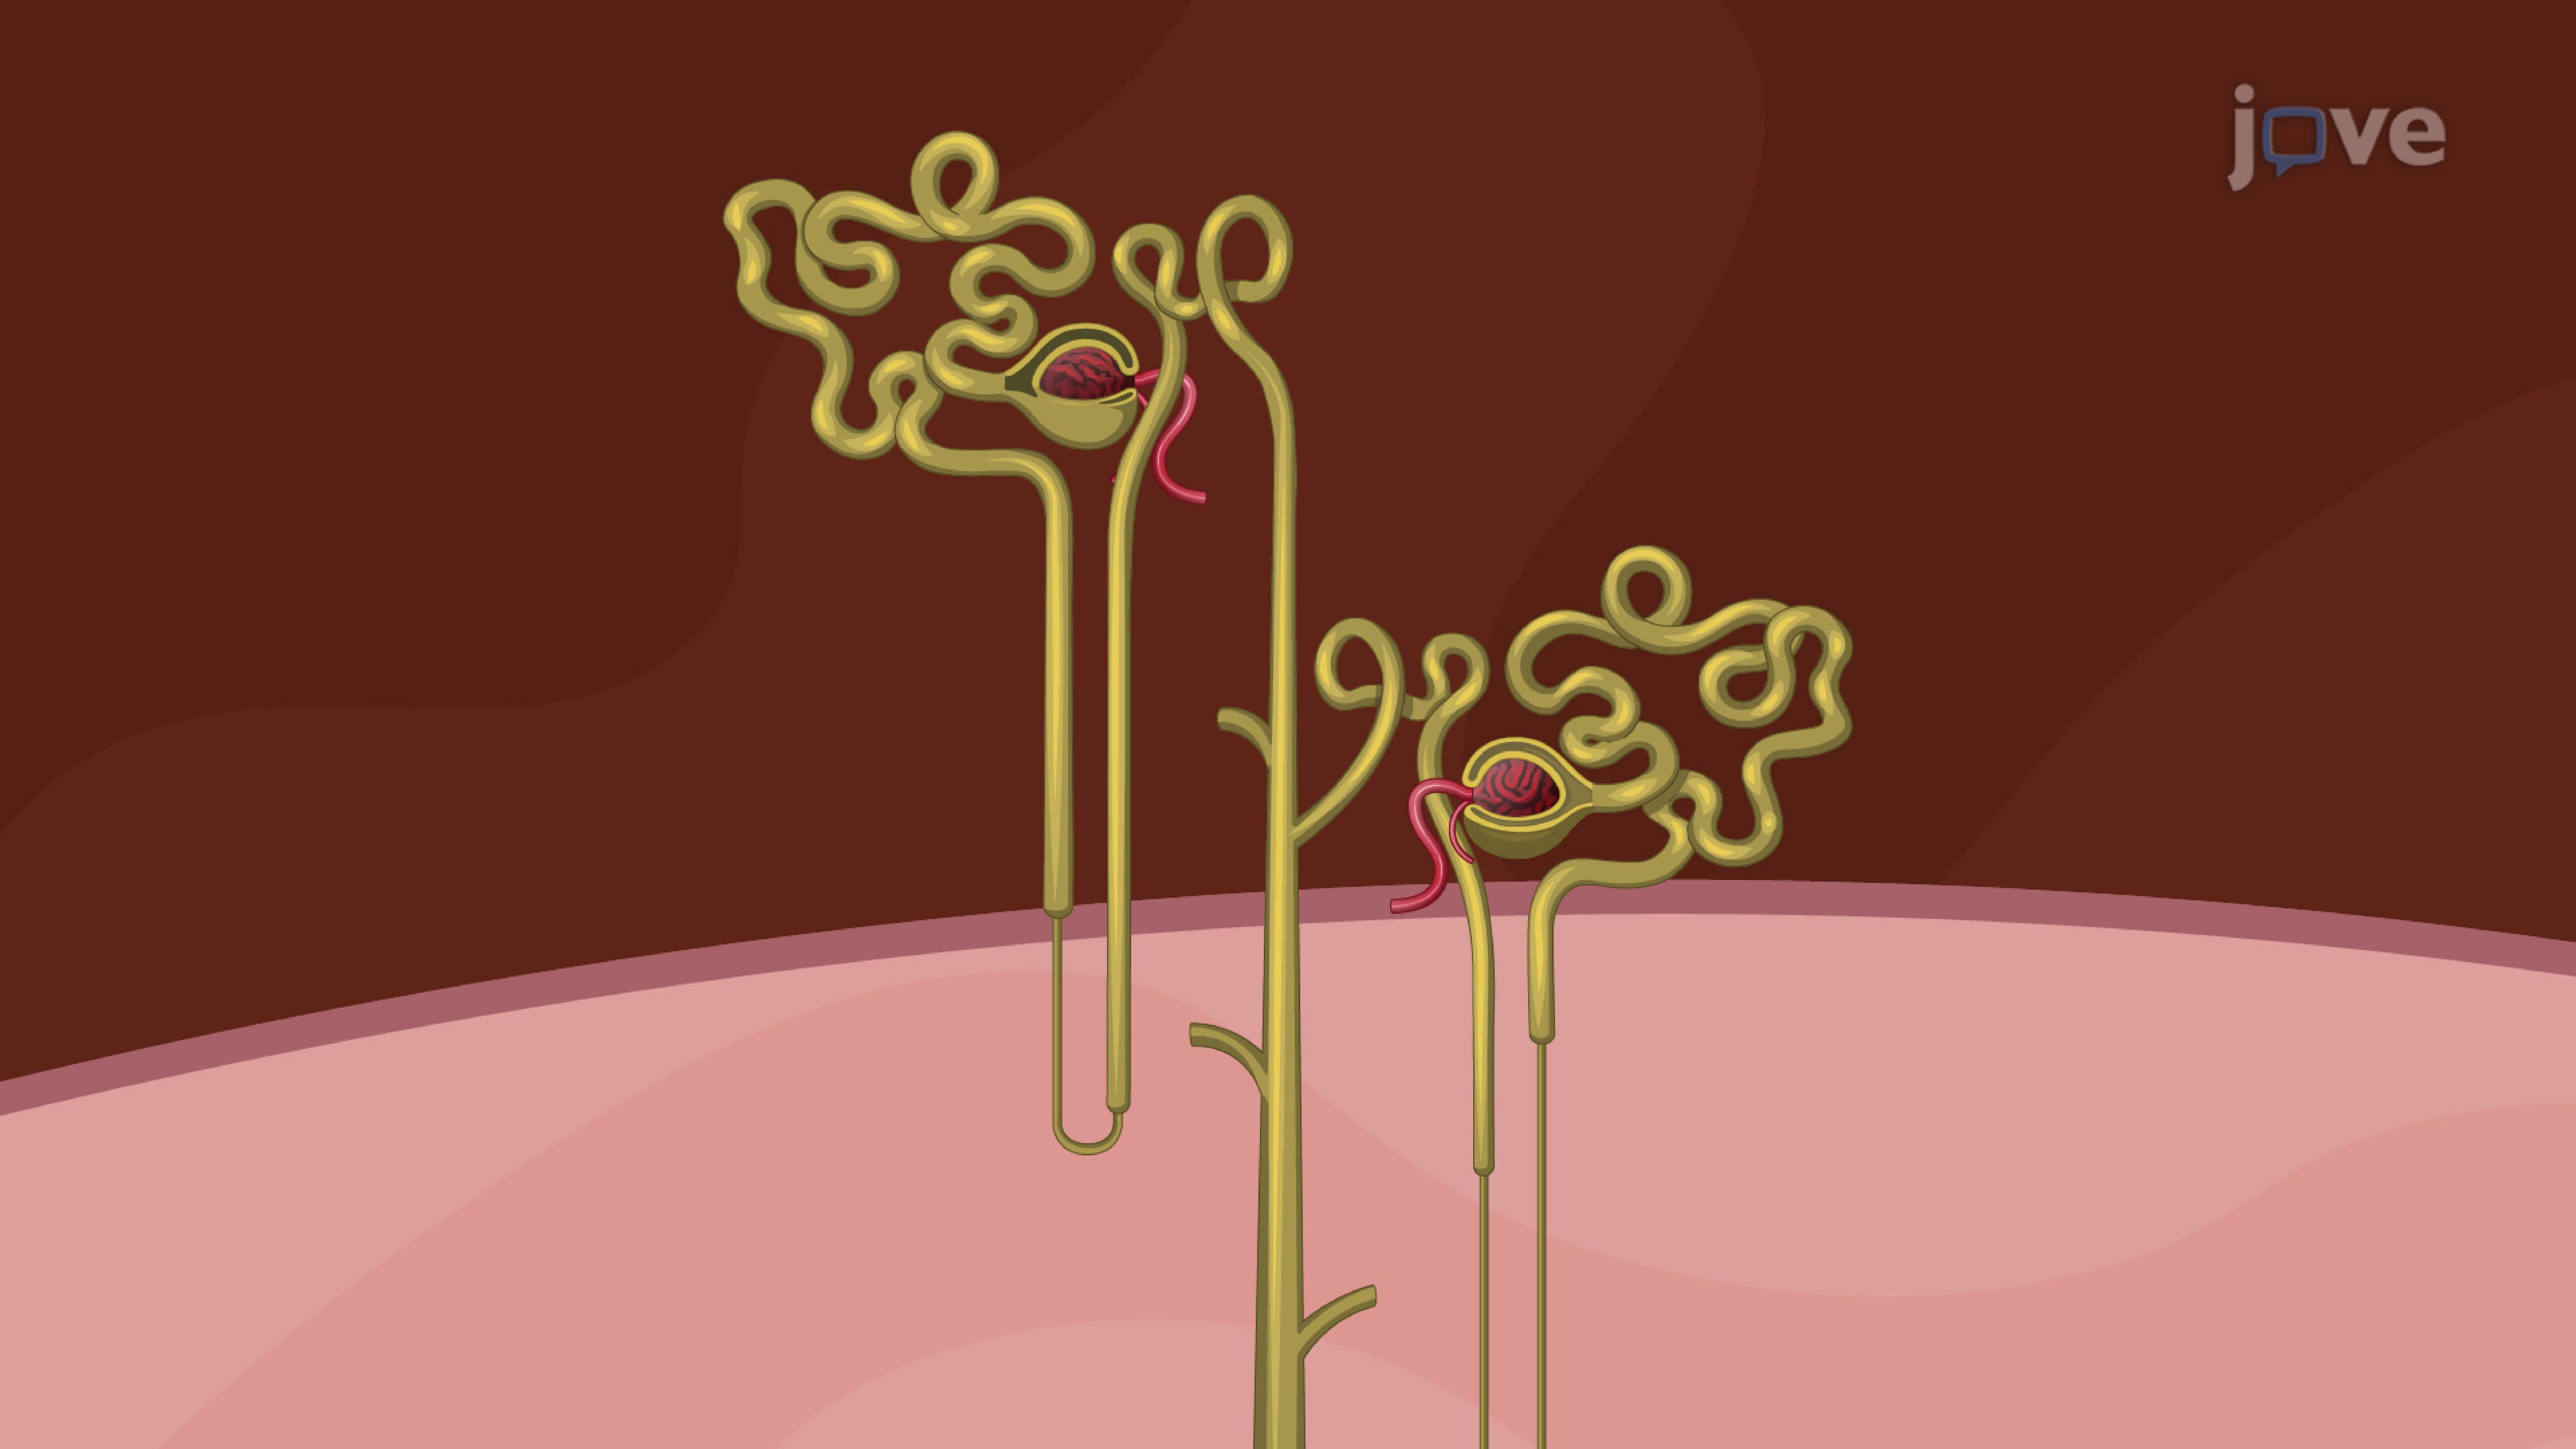
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...