Related Experiment Video
Updated: Jun 29, 2025
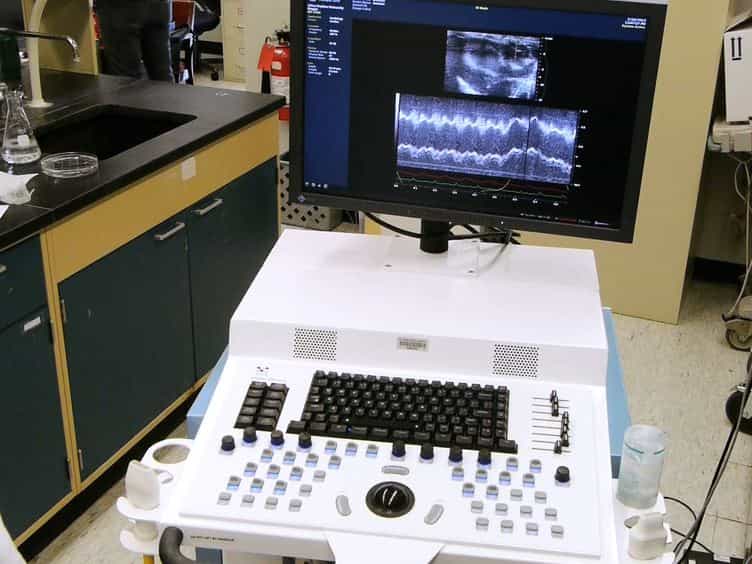

Measuring Ascending Aortic Stiffness In Vivo in Mice Using Ultrasound
Published on: December 2, 2014
Non-invasive assessment of left ventricular filling pressure in aortic stenosis
Hiroyuki Aoyagi1, Hiroyuki Iwano2,3, Yoji Tamaki1
1Department of Cardiovascular Medicine, Faculty of Medicine and Graduate School of Medicine, Hokkaido University, Sapporo, Japan.

Insights
The VMT score effectively predicts elevated left ventricular filling pressure in aortic stenosis patients, improving diagnostic accuracy over standard algorithms. This echocardiographic tool offers a valuable alternative for managing these patients.
Area of Science:
- Cardiology
- Echocardiography
- Cardiovascular Imaging
Background:
- Accurate assessment of left ventricular (LV) filling pressure (FP) is crucial for managing aortic stenosis (AS) patients.
- Standard methods for predicting LV FP in AS are often limited by mitral annular calcification and left ventricular hypertrophy.
- This study evaluates a novel echocardiographic scoring system for LV FP prediction in AS.
Purpose of the Study:
- To test the predictive ability of a new algorithm for elevated LV FP in AS patients.
- To assess a visually assessed time difference between mitral and tricuspid valve opening (VMT) score for predicting LV FP.
- To improve diagnostic accuracy for LV FP in AS using echocardiography.
Main Methods:
- 116 patients with moderate AS underwent right heart catheterization and echocardiography.
- Mean pulmonary artery wedge pressure (PAWP) served as the invasive measure of LV FP.
- The VMT score was calculated based on the timing of mitral and tricuspid valve opening, with adjustments for inferior vena cava dilation.
Main Results:
- The standard algorithm showed low specificity and positive predictive value for elevated PAWP.
- The VMT score (≥2) demonstrated good performance in predicting elevated PAWP (sensitivity 59%, specificity 90%, PPV 59%).
- An alternative algorithm incorporating tricuspid regurgitation velocity and VMT scores significantly improved predictive ability.
Conclusions:
- The VMT score is a practical tool for assessing AS patients.
- Integrating the VMT score enhances the diagnostic accuracy of guideline-recommended algorithms for LV FP.
- The VMT score offers a valuable non-invasive method for managing AS patients.
Background:
The assessment of left ventricular (LV) filling pressure (FP) is important for the management of aortic stenosis (AS) patients. Although, it is often restricted for predict LV FP in AS because of mitral annular calcification and a certain left ventricular hypertrophy. Thus, we tested the predictive ability of the algorithm for elevated LV FP in AS patients and also applied a recently-proposed echocardiographic scoring system of LV FP, visually assessed time difference between the mitral valve and tricuspid valve opening (VMT) score.
Methods:
We enrolled consecutive 116 patients with at least moderate AS in sinus rhythm who underwent right heart catheterization and echocardiography within 7 days. Mean pulmonary artery wedge pressure (PAWP) was measured as invasive parameter of LV FP. LV diastolic dysfunction (DD) was graded according to the ASE/EACVI guidelines. The VMT score was defined as follows: time sequence of opening of mitral and tricuspid valves was scored to 0-2 (0: tricuspid valve first, 1: simultaneous, 2: mitral valve first). When the inferior vena cava was dilated, one point was added and VMT score was finally calculated as 0-3.
Results:
Of the 116 patients, 29 patients showed elevated PAWP. Ninety patients (93%) and 67 patients (63%) showed increased values for left atrium volume index (LAVI) and E/e', respectively when the cut-off values recommended by the guidelines were applied and thus the algorism predicted elevated PAWP with a low specificity and positive predictive value (PPV). VMT ≥ 2 predicted elevated PAWP with a sensitivity of 59%, specificity of 90%, PPV of 59%, and negative predictive value of 89%. An alternative algorithm that applied tricuspid regurgitation velocity and VMT scores was tested, and its predictive ability was markedly improved.
Conclusion:
VMT score was applicable for AS patients. Alternative use of VMT score improved diagnostic accuracy of guideline-recommended algorism.

Related Concept Videos
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.