Related Experiment Video
Updated: Jun 29, 2025


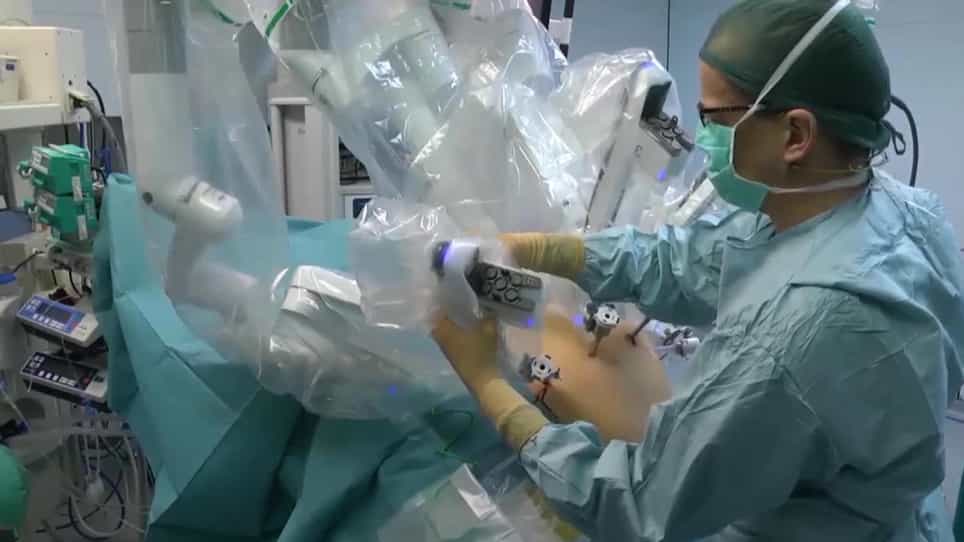
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Robotic beyond total mesorectal excision for locally advanced rectal cancers: Perioperative and oncological outcomes
Jim S Khan1, Guglielmo Niccolò Piozzi2, Philippe Rouanet3
1Department of Colorectal Surgery, Portsmouth Hospitals University NHS Trust, Portsmouth, UK; University of Portsmouth, Portsmouth, UK.

Background:
Around 20% of rectal tumors are locally advanced with invasion into adjacent structures at presentation. These may require surgical resections beyond boundaries of total mesorectal excision (bTME) for radicality. Robotic bTME is under investigation. This study reports perioperative and oncological outcomes of robotic bTME for locally advanced rectal cancers.
Materials And Methods:
A multicentre, retrospective analysis of prospectively collected robotic bTME resections (July 2015-November 2020). Demographics, clinicopathological features, short-term outcomes, recurrences, and survival were investigated.
Results:
One-hundred-sixty-eight patients (eight centres) were included. Median age and BMI were 60.0 (50.0-68.7) years and 24.0 (24.4-27.7) kg/m2. Female sex was prevalent (n = 95, 56.8%). Fifty patients (29.6%) were ASA III-IV. Neoadjuvant chemoradiotherapy was given to 125 (74.4%) patients. Median operative time was 314.0 (260.0-450.0) minutes. Median estimated blood loss was 150.0 (27.5-500.0) ml. Conversion to laparotomy was seen in 4.8%. Postoperative complications occurred in 77 (45.8%) patients; 27.3% and 3.9% were Clavien-Dindo III and IV, respectively. Thirty-day mortality was 1.2% (n = 2). R0 rate was 92.9%. Adjuvant chemotherapy was offered to 72 (42.9%) patients. Median follow-up was 34.0 (10.0-65.7) months. Distant and local recurrences were seen in 35 (20.8%) and 15 patients (8.9%), respectively. Overall survival (OS) at 1, 3, and 5-years was 91.7, 82.1, and 76.8%. Disease-free survival (DFS) at 1, 3, and 5-years was 84.0, 74.5, and 69.2%.
Conclusion:
Robotic bTME is technically safe with relatively low conversion rate, good OS, and acceptable DFS in the hands of experienced surgeons in high volume centres. In selected cases robotic approach allows for high R0 rates during bTME.