Related Experiment Video
Updated: Jun 29, 2025


Post-Myocardial Infarction Heart Failure in Closed-chest Coronary Occlusion/Reperfusion Model in Göttingen Minipigs and Landrace Pigs
Published on: April 17, 2021
Beta-Blockers after Myocardial Infarction and Preserved Ejection Fraction
Troels Yndigegn1, Bertil Lindahl1, Katarina Mars1
1From the Department of Cardiology, Clinical Sciences, Lund University, and Skåne University Hospital, Lund (T.Y., D.E.), the Department of Medical Sciences, Uppsala University (B.L., C.H., J.S.), and Uppsala Clinical Research Center (B.L., C.H., O.Ö.), Uppsala, the Department of Clinical Science and Education, Division of Cardiology, Karolinska Institutet, Södersjukhuset (K.M., R.H.), the Department of Clinical Sciences, Danderyd Hospital, Karolinska Institutet (P.H., T.J.), and the Heart and Lung Patients Association (P.J.), Stockholm, the Departments of Cardiology (J.A.) and Health, Medicine, and Caring Sciences (J.A., P.K.), Linköping University, Linköping, the Division of Cardiology, Skaraborgs Sjukhus, Skövde (L.B.), the Division of Cardiology and Emergency Medicine, Centralsjukhuset Karlstad, Karlstad (O.H., T.K.), the Department of Internal Medicine, Ryhov County Hospital, Jönköping (P.K.), and the Department of Cardiology, Sahlgrenska University Hospital, and the Institute of Medicine, Department of Molecular and Clinical Medicine, Sahlgrenska Academy University of Gothenburg, Gothenburg (A.R.-F.) - all in Sweden; Green Lane Cardiovascular Service, Auckland City Hospital, Auckland, New Zealand (J.B.); the Department of Cardiology, Institute of Clinical Medicine, University of Tartu, Tartu, and the Center of Cardiology, North Estonia Medical Center, Tallinn - both in Estonia (T.M.); and the George Institute for Global Health, University of New South Wales, Sydney (J.S.).

Insights
Beta-blocker treatment after myocardial infarction in patients with preserved ejection fraction did not reduce the risk of death or new heart attacks. This finding contrasts with earlier studies in different patient populations.
Area of Science:
- Cardiology
- Clinical Trials
- Pharmacology
Background:
- Previous studies showing beta-blocker benefits post-myocardial infarction (MI) often involved patients with larger MIs and predated modern treatments.
- Current evidence may not directly apply to contemporary MI patients receiving advanced therapies like percutaneous coronary intervention and high-intensity statins.
Purpose of the Study:
- To evaluate the efficacy of long-term beta-blocker treatment in patients with acute myocardial infarction and preserved left ventricular ejection fraction (LVEF).
- To assess the impact of beta-blockers on the composite endpoint of all-cause death or new myocardial infarction in this specific patient group.
Main Methods:
- A parallel-group, open-label trial randomized 5020 patients with acute MI and LVEF ≥50% to receive long-term beta-blockers (metoprolol or bisoprolol) or no beta-blocker.
- The primary endpoint was a composite of death from any cause or new myocardial infarction, with a median follow-up of 3.5 years.
Main Results:
- No significant difference in the primary endpoint was observed between the beta-blocker group (7.9%) and the no-beta-blocker group (8.3%), with a hazard ratio of 0.96 (95% CI, 0.79 to 1.16).
- Secondary endpoints, including all-cause death, cardiovascular death, myocardial infarction, and hospitalizations for atrial fibrillation or heart failure, also showed no significant benefit from beta-blocker treatment.
- Safety endpoints, such as bradycardia, heart block, hypotension, syncope, pacemaker implantation, and hospitalizations for respiratory conditions or stroke, were similar between the groups.
Conclusions:
- In patients with acute myocardial infarction who underwent early coronary angiography and had preserved LVEF (≥50%), long-term beta-blocker treatment did not reduce the risk of death or new myocardial infarction compared to no beta-blocker use.
- These findings suggest that the role of beta-blockers in post-MI management may need re-evaluation in the context of modern therapeutic strategies and specific patient characteristics like preserved LVEF.
Background:
Most trials that have shown a benefit of beta-blocker treatment after myocardial infarction included patients with large myocardial infarctions and were conducted in an era before modern biomarker-based diagnosis of myocardial infarction and treatment with percutaneous coronary intervention, antithrombotic agents, high-intensity statins, and renin-angiotensin-aldosterone system antagonists.
Methods:
In a parallel-group, open-label trial performed at 45 centers in Sweden, Estonia, and New Zealand, we randomly assigned patients with an acute myocardial infarction who had undergone coronary angiography and had a left ventricular ejection fraction of at least 50% to receive either long-term treatment with a beta-blocker (metoprolol or bisoprolol) or no beta-blocker treatment. The primary end point was a composite of death from any cause or new myocardial infarction.
Results:
From September 2017 through May 2023, a total of 5020 patients were enrolled (95.4% of whom were from Sweden). The median follow-up was 3.5 years (interquartile range, 2.2 to 4.7). A primary end-point event occurred in 199 of 2508 patients (7.9%) in the beta-blocker group and in 208 of 2512 patients (8.3%) in the no-beta-blocker group (hazard ratio, 0.96; 95% confidence interval, 0.79 to 1.16; P = 0.64). Beta-blocker treatment did not appear to lead to a lower cumulative incidence of the secondary end points (death from any cause, 3.9% in the beta-blocker group and 4.1% in the no-beta-blocker group; death from cardiovascular causes, 1.5% and 1.3%, respectively; myocardial infarction, 4.5% and 4.7%; hospitalization for atrial fibrillation, 1.1% and 1.4%; and hospitalization for heart failure, 0.8% and 0.9%). With regard to safety end points, hospitalization for bradycardia, second- or third-degree atrioventricular block, hypotension, syncope, or implantation of a pacemaker occurred in 3.4% of the patients in the beta-blocker group and in 3.2% of those in the no-beta-blocker group; hospitalization for asthma or chronic obstructive pulmonary disease in 0.6% and 0.6%, respectively; and hospitalization for stroke in 1.4% and 1.8%.
Conclusions:
Among patients with acute myocardial infarction who underwent early coronary angiography and had a preserved left ventricular ejection fraction (≥50%), long-term beta-blocker treatment did not lead to a lower risk of the composite primary end point of death from any cause or new myocardial infarction than no beta-blocker use. (Funded by the Swedish Research Council and others; REDUCE-AMI ClinicalTrials.gov number, NCT03278509.).


Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
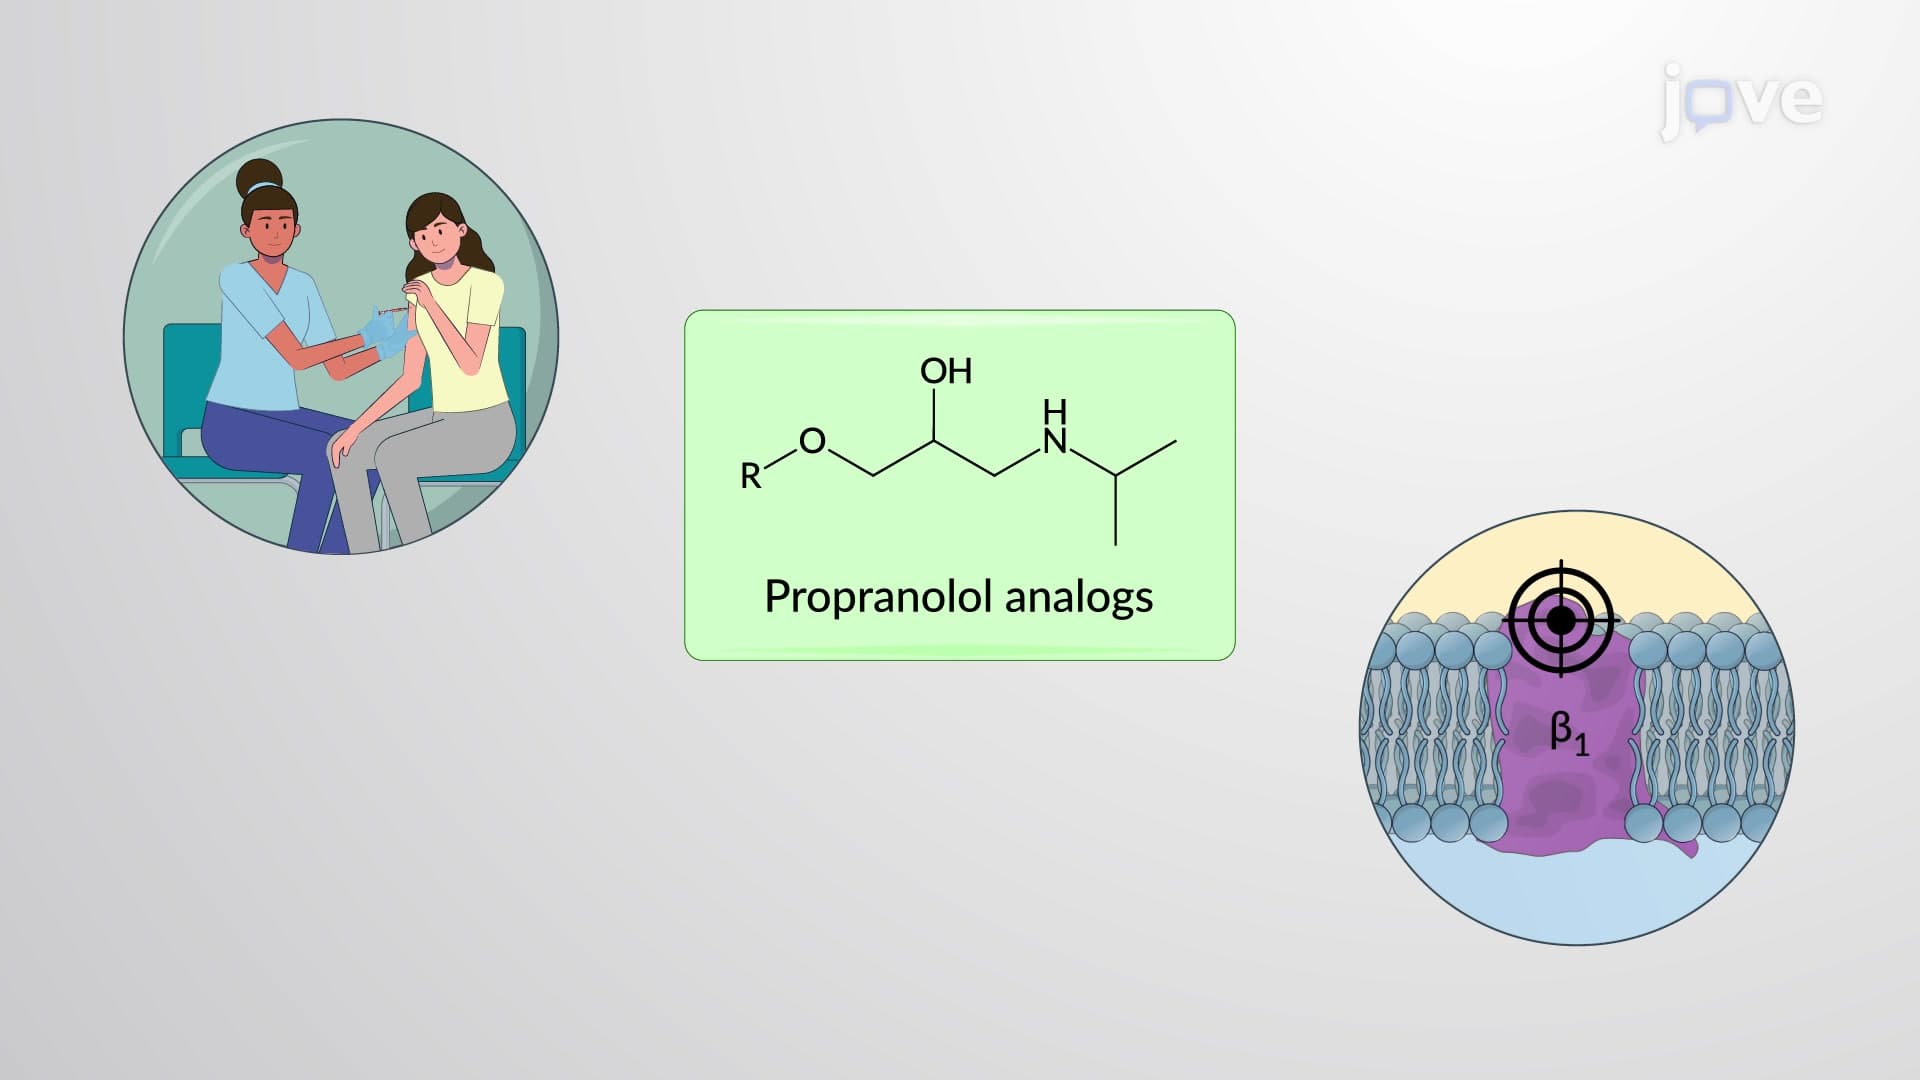 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers