Related Experiment Video
Updated: Jun 29, 2025


Rat Model of Right-Sided Cardiac Remodeling and Arrhythmia Using Pulmonary Artery Banding
Published on: August 30, 2024
Arrhythmic manifestations and outcomes of definite and probable cardiac sarcoidosis
Daniel Sykora1, Andrew N Rosenbaum1, Robert A Churchill2
1Department of Cardiovascular Medicine, Mayo Clinic, Rochester, Minnesota.

Insights
Patients with definite and probable cardiac sarcoidosis (CS) face similar risks of sudden cardiac death and mortality. However, definite CS patients experience a higher burden of arrhythmias, necessitating aggressive management for both groups.
Area of Science:
- Cardiology
- Electrophysiology
- Sarcoidosis Research
Background:
- The 2014 Heart Rhythm Society (HRS) consensus statement established diagnostic criteria for cardiac sarcoidosis (CS), categorizing it as definite (histological) or probable (clinical).
- Limited research has compared the distinct arrhythmic profiles and clinical outcomes between these two diagnostic categories of CS.
Purpose of the Study:
- To investigate and compare the electrophysiological and arrhythmic characteristics, as well as clinical outcomes, in patients diagnosed with definite versus probable cardiac sarcoidosis.
Main Methods:
- A single-center North American cohort of 388 patients diagnosed with definite (n=58) or probable (n=330) CS between 2000 and 2022 was analyzed.
- The study evaluated the arrhythmic/electrophysiological phenotype, with the primary composite outcome being survival to the first event of ventricular tachycardia/fibrillation (VT/VF) or sudden cardiac death.
Main Results:
- While the primary outcome (first VT/VF or sudden cardiac death) occurred in 38% of both definite and probable CS patients over a median follow-up of 3.1 years, definite CS patients showed a higher burden of device-treated VT/VF events.
- A higher ratio of myocardial to blood pool 18F-fluorodeoxyglucose maximum standardized uptake value was significantly associated with the primary outcome (HR 1.09; P=.003).
- Definite CS patients had a greater need for heart transplantation or left ventricular assist device implantation, but no significant difference in all-cause mortality was observed compared to probable CS patients.
Conclusions:
- Both definite and probable cardiac sarcoidosis patients exhibit a high risk for sustained ventricular arrhythmias/sudden cardiac death and all-cause mortality.
- Despite similar risks for initial life-threatening events, definite CS is associated with a greater overall arrhythmia burden.
- The findings underscore the need for proactive management strategies for both diagnostic categories of CS to mitigate arrhythmic complications.
Background:
The 2014 Heart Rhythm Society consensus statement defines histological (definite) and clinical (probable) diagnostic categories of cardiac sarcoidosis (CS), but few studies have compared their arrhythmic phenotypes and outcomes.
Objective:
The purpose of this study was to evaluate the electrophysiological/arrhythmic phenotype and outcomes of patients with definite and probable CS.
Methods:
We analyzed the arrhythmic/electrophysiological phenotype in a single-center North American cohort of 388 patients (median age 56 years; 39% female, n = 151) diagnosed with definite (n = 58) or probable (n = 330) CS (2000-2022). The primary composite outcome was survival to first ventricular tachycardia/fibrillation (VT/VF) event or sudden cardiac death. Key secondary outcomes were also assessed.
Results:
At index evaluation, in situ cardiac implantable electronic devices and antiarrhythmic drug use were more common in definite CS. At a median follow-up of 3.1 years, the primary outcome occurred in 22 patients with definite CS (38%) and 127 patients with probable CS (38%) (log-rank, P = .55). In multivariable analysis, only a higher ratio of the 18F-fluorodeoxyglucose maximum standardized uptake value of the myocardium to the maximum standardized uptake value of the blood pool (hazard ratio 1.09; 95% confidence interval 1.03-1.15; P = .003, per 1 unit increase) was associated with the primary outcome. During follow-up, patients with definite CS had a higher burden of device-treated VT/VF events (mean 2.86 events per patient-year vs 1.56 events per patient-year) and a higher rate of progression to heart transplant/left ventricular assist device implantation but no difference in all-cause mortality compared with patients with probable CS.
Conclusion:
Patients with definite and probable CS had similarly high risks of first sustained VT/VF/sudden cardiac death and all-cause mortality, though patients with definite CS had a higher overall arrhythmia burden. Both CS diagnostic groups as defined by the 2014 Heart Rhythm Society criteria require an aggressive approach to prevent arrhythmic complications.
More Related Videos
 09:36
Dual-Dye Optical Mapping of Hearts from RyR2R2474S Knock-In Mice of Catecholaminergic Polymorphic Ventricular Tachycardia
Published on: December 22, 2023
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:28
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow...
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:19
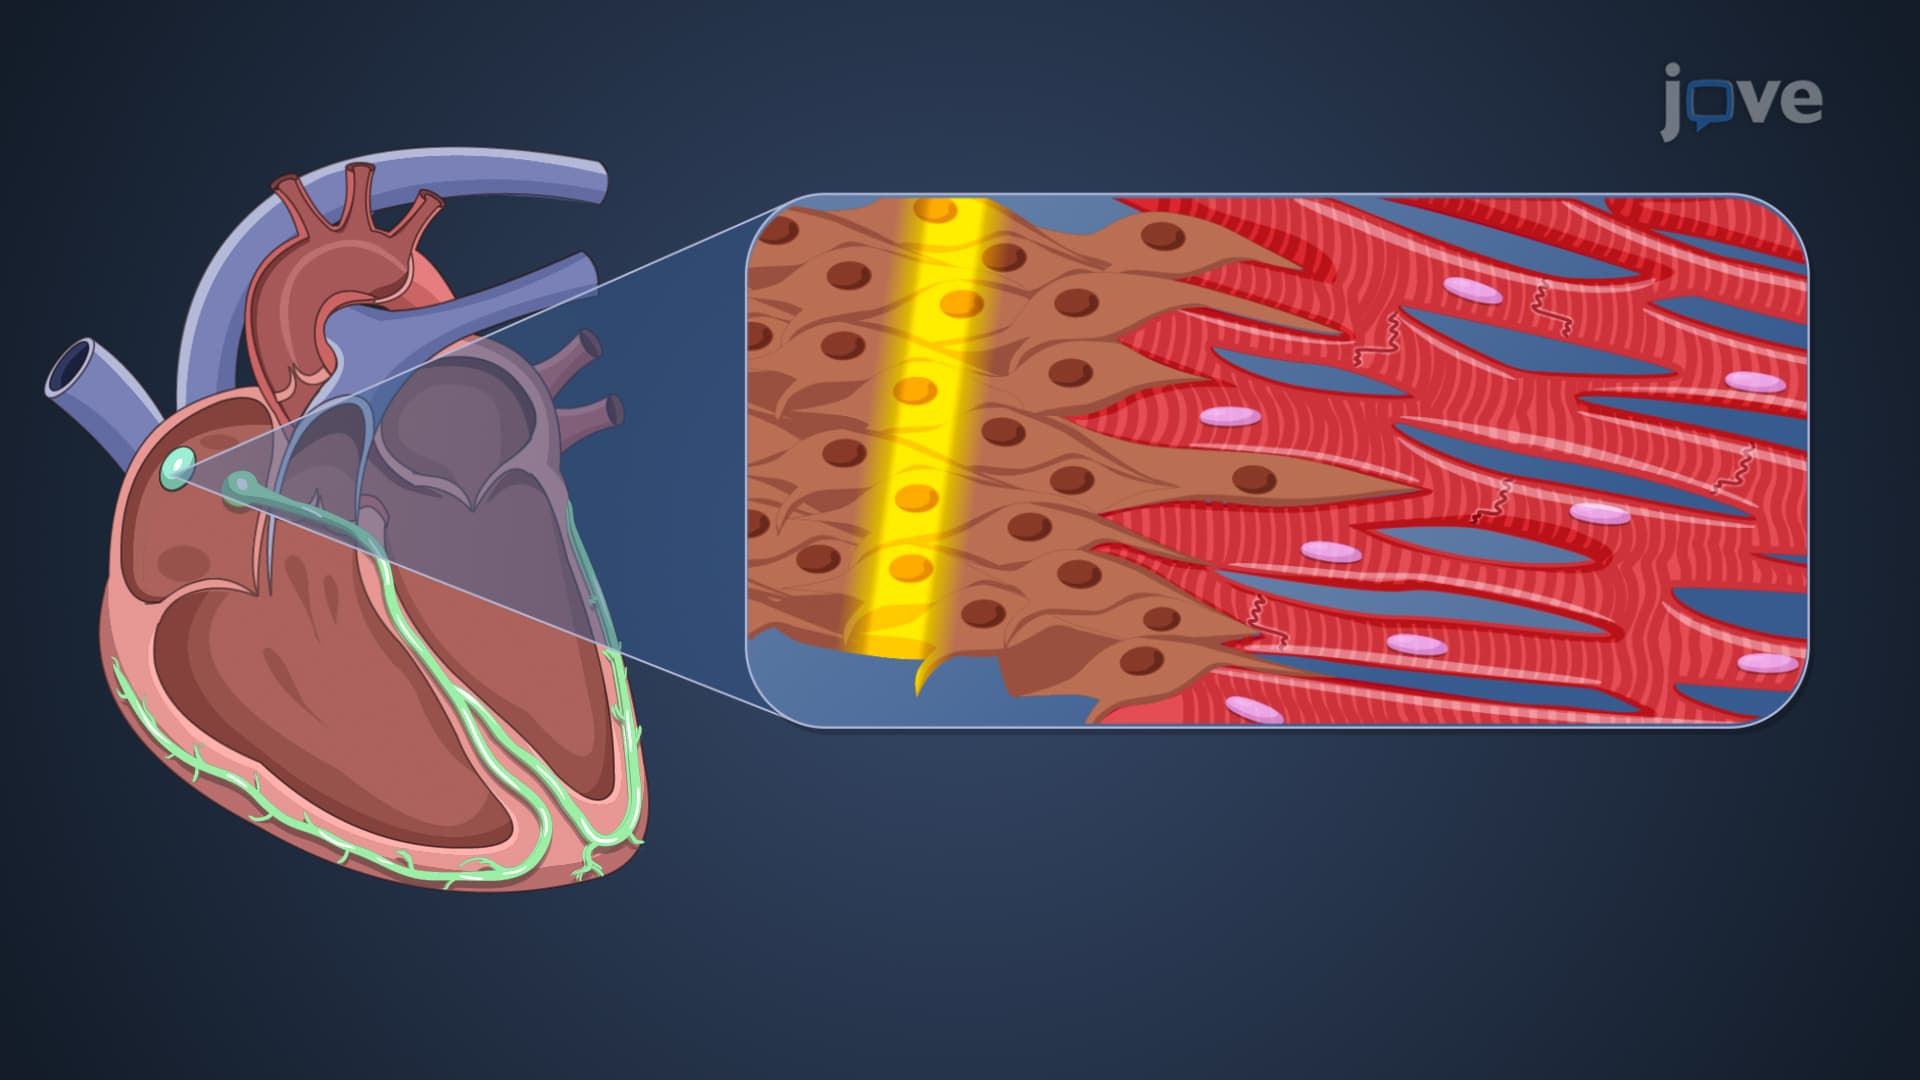
Electrophysiology of Normal Cardiac Rhythm
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...
 01:25
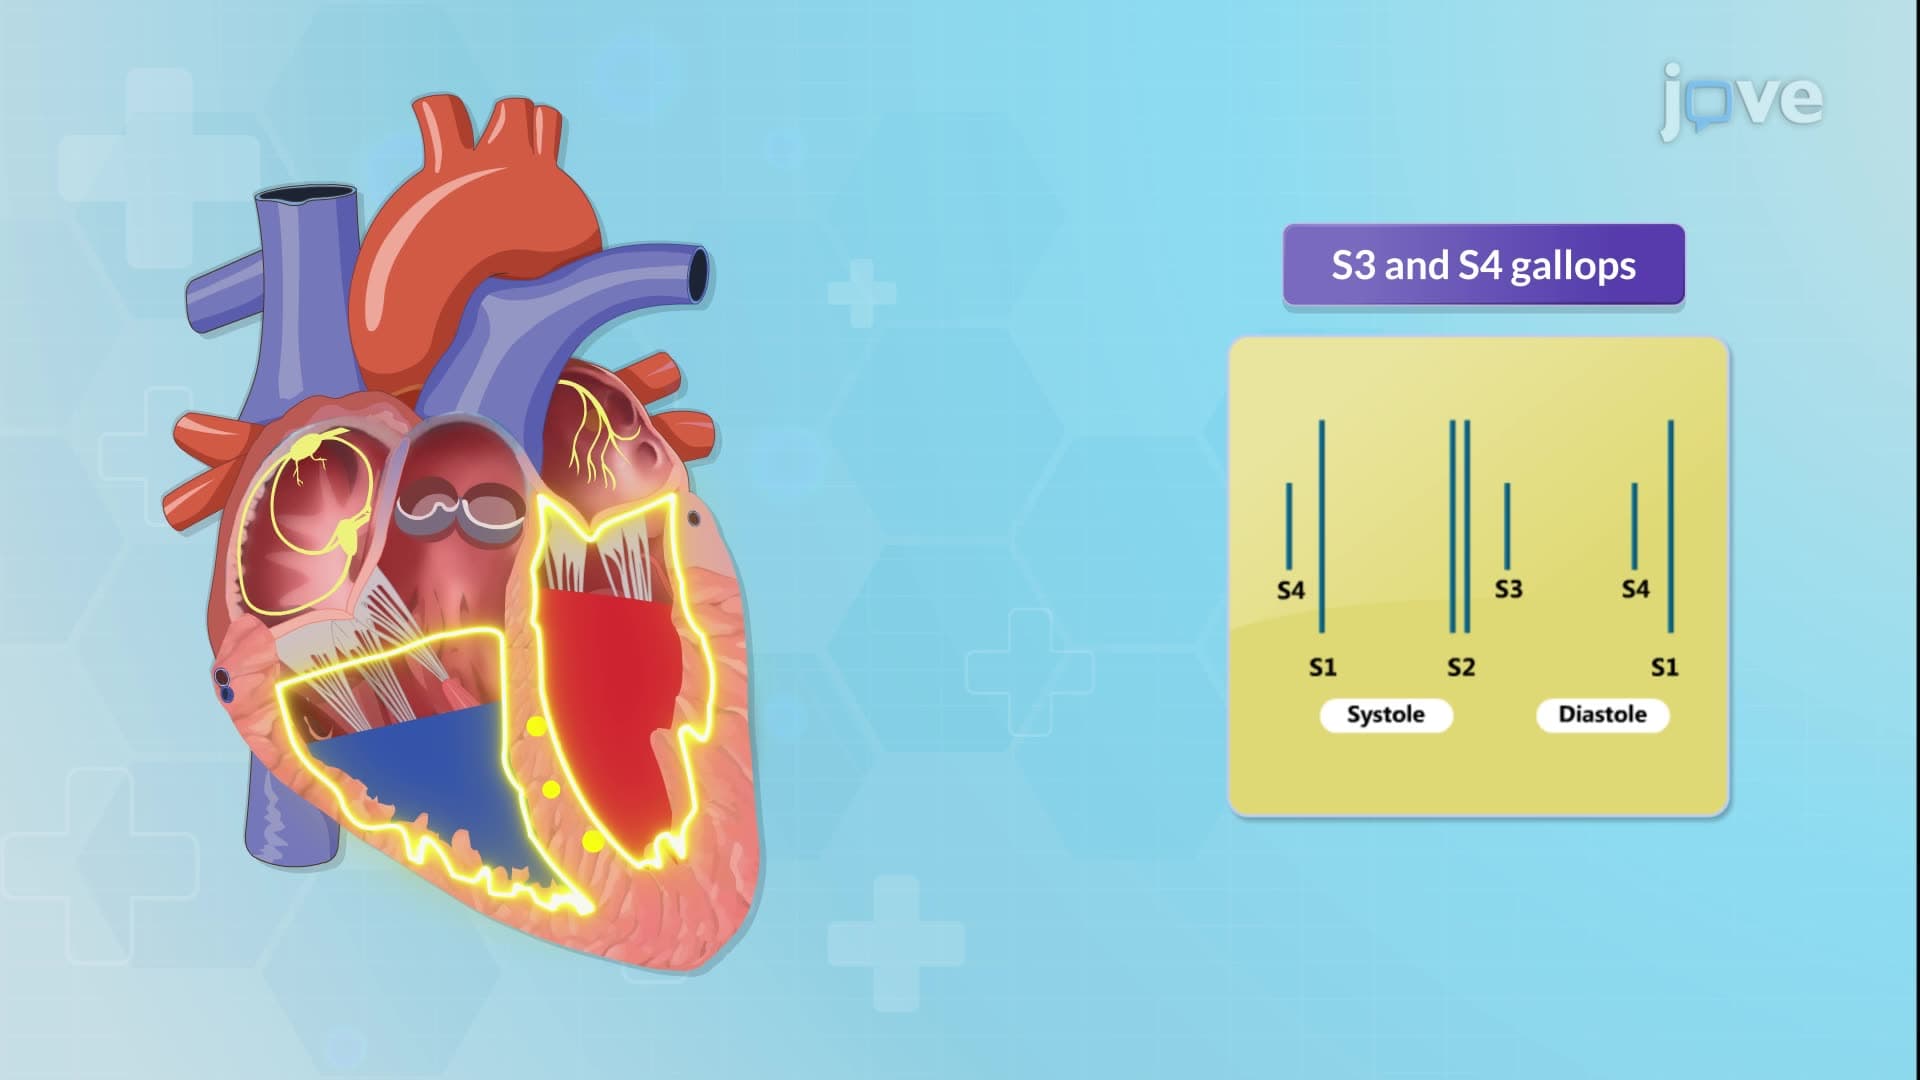
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops: