Related Experiment Video
Updated: Jun 29, 2025
Author Spotlight: Minimally Invasive Relief for Occipital Neuralgia at the Nuchal Line
Published on: September 13, 2024
Adult-onset Sacral Meningocele Causing a Specific Headache Triggered by Compression or Adoption of a Sitting or
Masaya Nishikata1, Masahito Kobayashi1, Takamitsu Fujimaki1
1Department of Neurosurgery, Saitama Medical University Hospital, Saitama, Japan.

We report a rare case of adult-onset sacral meningocele where compression triggered a specific headache. A 46-year-old woman presented with a headache, which worsened when she was in a sitting or supine position. A subcutaneous mass was observed on her left buttock, the compression of which also induced headache. No neurological deficits were evident. Lumbar and sacral magnetic resonance imaging demonstrated a meningocele in the left dorsal buttock, connecting to the sacral cerebrospinal fluid (CSF) space, and spinal computed tomography revealed sacral dysplasia. Initial meningocele resection improved the patient's headache, but the cyst recurred 2 years later. Following repeated surgery to reinforce the meningocele orifice, the headache was relieved and has been absent for more than 6 years. The headache was due to intracranial pressure fluctuations due to CSF influx into and drainage from the meningocele. Meningocele development in adulthood can be owing to a spinal bone defect and pressure load on the spinal dura. Surgical resection can improve symptoms resulting from meningocele, and reinforcement of the orifice using an artificial surgical membrane effectively prevents recurrence.
We report a rare case of adult-onset sacral meningocele where compression triggered a specific headache. A 46-year-old woman presented with a headache, which worsened when she was in a sitting or supine position. A subcutaneous mass was observed on her left buttock, the compression of which also induced headache. No neurological deficits were evident. Lumbar and sacral magnetic resonance imaging demonstrated a meningocele in the left dorsal buttock, connecting to the sacral cerebrospinal fluid (CSF) space, and spinal computed tomography revealed sacral dysplasia. Initial meningocele resection improved the patient's headache, but the cyst recurred 2 years later. Following repeated surgery to reinforce the meningocele orifice, the headache was relieved and has been absent for more than 6 years. The headache was due to intracranial pressure fluctuations due to CSF influx into and drainage from the meningocele. Meningocele development in adulthood can be owing to a spinal bone defect and pressure load on the spinal dura. Surgical resection can improve symptoms resulting from meningocele, and reinforcement of the orifice using an artificial surgical membrane effectively prevents recurrence.
More Related Videos
 04:33
Spinal Hernia Repair and Cauda Equina Repositioning After Lumbar Decompression under Three-Dimensional Microscopy: A Case Report and Literature Review
Published on: November 8, 2024
 10:39
3D-Neuronavigation In Vivo Through a Patient's Brain During a Spontaneous Migraine Headache
Published on: June 2, 2014
Related Concept Videos
 01:15
Equilibrium and Balance
 01:19
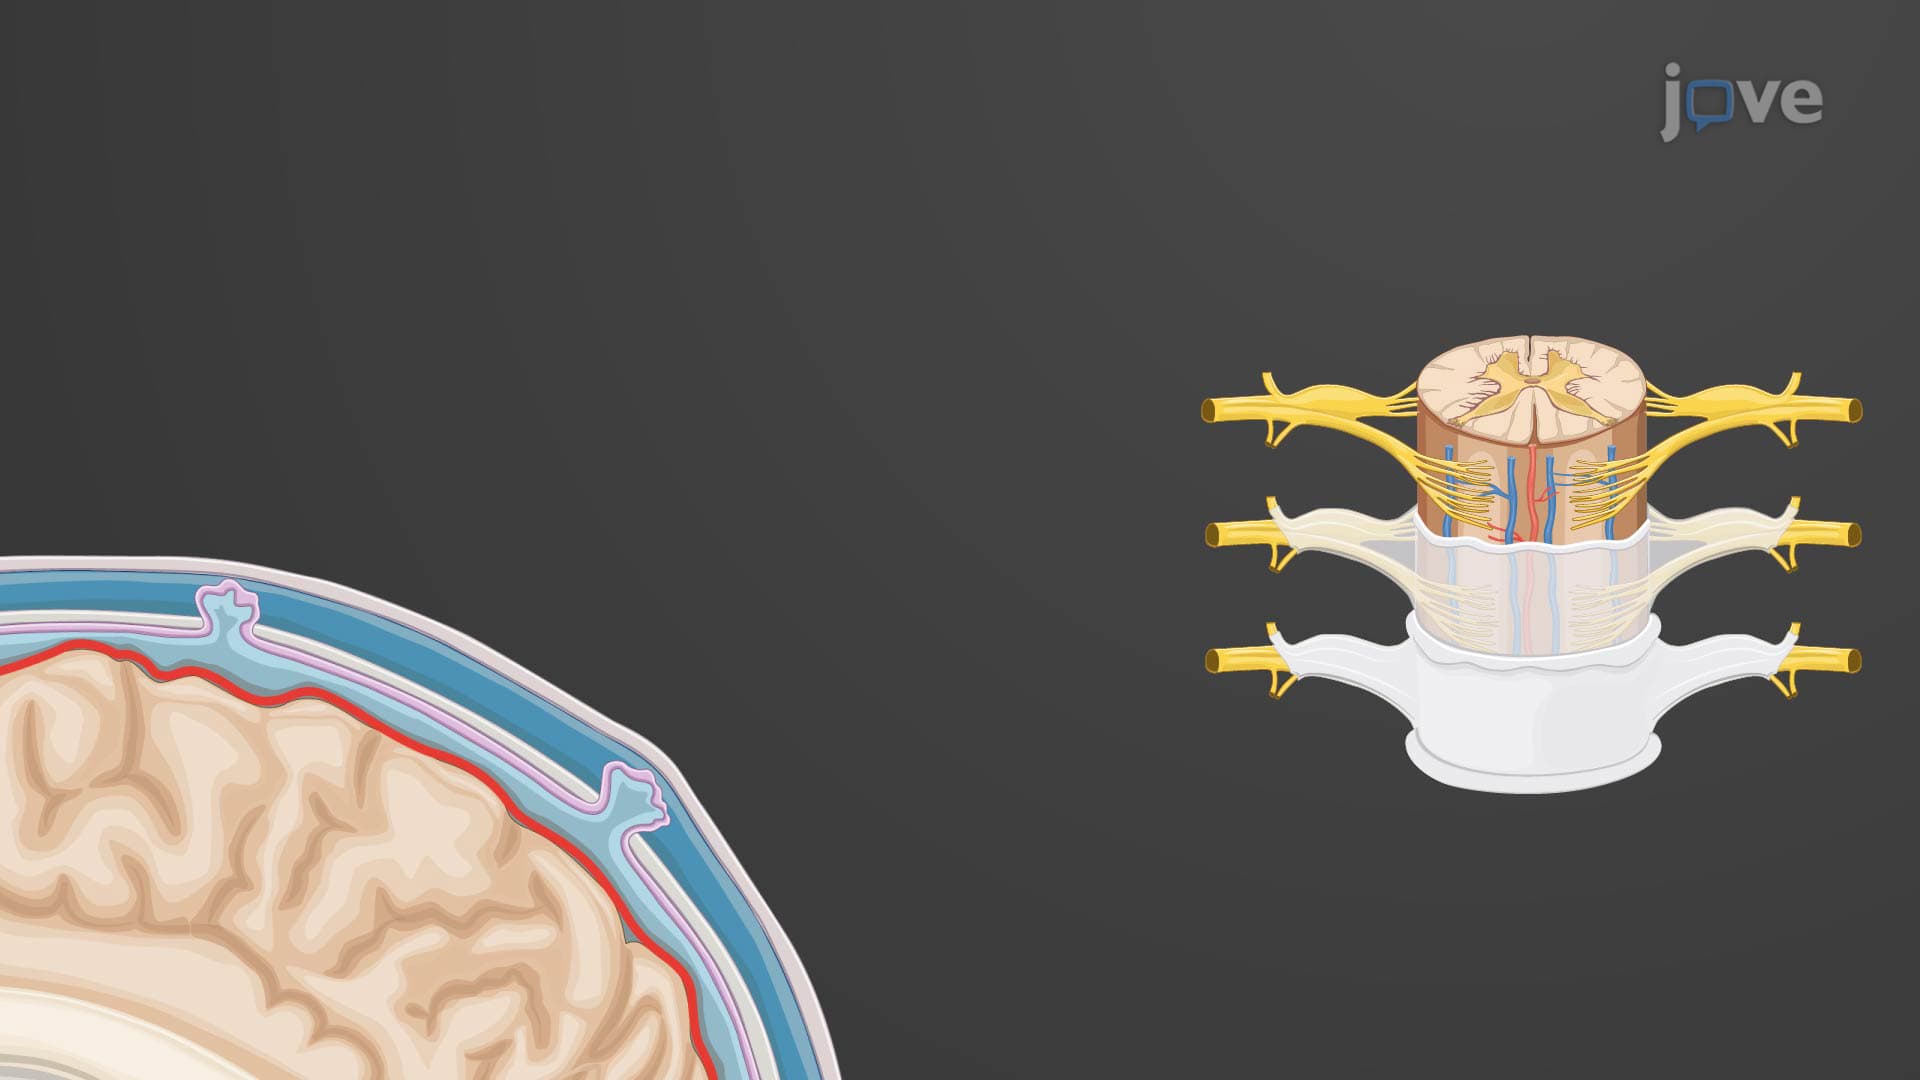
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...