Related Experiment Video
Updated: Jun 2, 2026
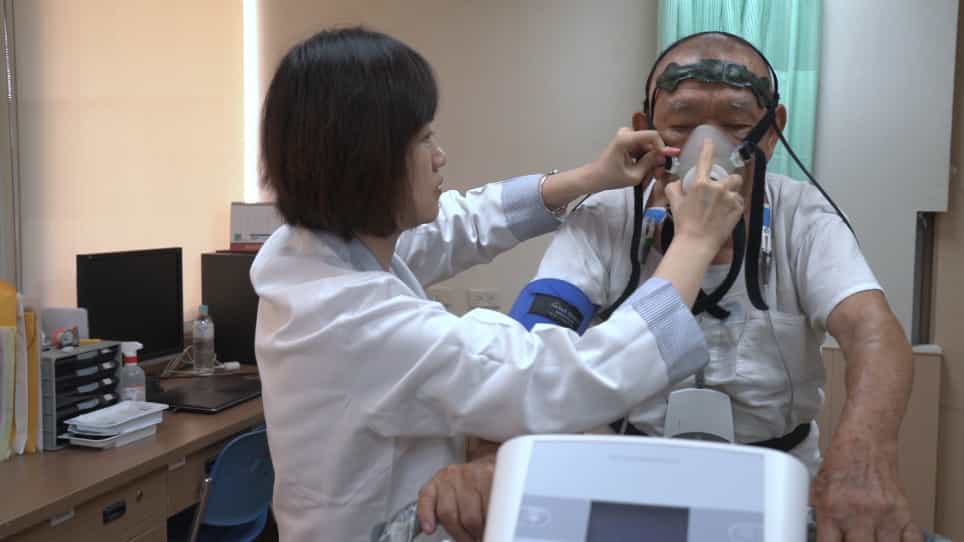

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cardiopulmonary Exercise Testing after Surgical Repair of Tetralogy of Fallot-Does Modality Matter?
Benedetta Leonardi1, Fabrizio Sollazzo2, Federica Gentili3
1Department of Pediatric Cardiology, Cardiac Surgery and Heart Lung Transplantation, Bambino Gesù Children's Hospital, IRCCS, 00165 Rome, Italy.

Background:
Despite a successful repair of tetralogy of Fallot (rToF) in childhood, residual lesions are common and can contribute to impaired exercise capacity. Although both cycle ergometer and treadmill protocols are often used interchangeably these approaches have not been directly compared. In this study we examined cardiopulmonary exercise test (CPET) measurements in rToF.
Methods:
Inclusion criteria were clinically stable rToF patients able to perform a cardiac magnetic resonance imaging (CMR) and two CPET studies, one on the treadmill (incremental Bruce protocol) and one on the cycle ergometer (ramped protocol), within 12 months. Demographic, surgical and clinical data; functional class; QRS duration; CMR measures; CPET data and international physical activity questionnaire (IPAQ) scores of patients were collected.
Results:
Fifty-seven patients were enrolled (53% male, 20.5 ± 7.8 years at CPET). CMR measurements included a right ventricle (RV) end-diastolic volume index of 119 ± 22 mL/m2, a RV ejection fraction (EF) of 55 ± 6% and a left ventricular (LV) EF of 56 ± 5%. Peak oxygen consumption (VO2)/Kg (25.5 ± 5.5 vs. 31.7 ± 6.9; p < 0.0001), VO2 at anaerobic threshold (AT) (15.3 ± 3.9 vs. 22.0 ± 4.5; p < 0.0001), peak O2 pulse (10.6 ± 3.0 vs. 12.1± 3.4; p = 0.0061) and oxygen uptake efficiency slope (OUES) (1932.2 ± 623.6 vs. 2292.0 ± 639.4; p < 0.001) were significantly lower on the cycle ergometer compared with the treadmill, differently from ventilatory efficiency (VE/VCO2) max which was significantly higher on the cycle ergometer (32.2 ± 4.5 vs. 30.4 ± 5.4; p < 0.001). Only the VE/VCO2 slope at the respiratory compensation point (RCP) was similar between the two methodologies (p = 0.150).
Conclusions:
The majority of CPET measurements differed according to the modality of testing, with the exception being the VE/VCO2 slope at RCP. Our data suggest that CPET parameters should be interpreted according to test type; however, these findings should be validated in larger populations and in a variety of institutions.
More Related Videos
Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management