Related Experiment Video
Updated: Jun 28, 2025


Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
[Diffuse thickening of bronchial walls with multiple nodular mucosal protrusions]
1Department of Pulmonary and Critical Care Medicine, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing 100730, China.

Abstract:
A 58-year-old woman presented with a six-month history of nasal congestion, sore throat and cough, and a five-month history of dyspnea. She had a history of xerostomia for one year. On examination, the bilateral submandibular gland and parotid glands were enlarged. Parotid and anterior cervical lymph nodes were palpable. There were rales in both lungs. The rest of the physical examination was unremarkable. Sialographic analysis showed normal caliber in the main duct, stenosis in secondary ducts, and dilation in the proximal ducts. Minor salivary gland biopsy demonstrated periductal lymphocytic infiltration. Chest computed tomography (CT) showed diffuse thickening of the tracheal and bilateral bronchial walls. Bronchoscopy revealed macroscopic multiple nodules mainly in the trachea and bilateral main bronchus. Endobronchial biopsy showed lymphocytic infiltration in the bronchial submucosa. She was diagnosed with Sjögren's syndrome and treated with glucocorticoids. The dose of prednisone was started at 30 mg/d and tapered gradually. Following treatment, the patient's clinical condition improved dramatically, with shrinkage of the enlarged lymph nodes, bilateral submandibular and parotid glands. A repeated chest CT scan revealed improvement of the tracheal and bilateral bronchial thickening. Multiple nodules in the airway regressed, as evidenced by repeated bronchoscopic examination. The final diagnosis was a large-airway disease associated with Sjögren's syndrome.Among airway diseases in Sjögren's syndrome, peripheral airway diseases including bronchiolitis and bronchiectasis are common; however, central airway lesions in Sjögren's syndrome, especially with macroscopic nodules, are rare. In this case, we demonstrated tracheal and endobronchial nodules in Sjögren's syndrome as determined by clinical features, CT scan, bronchoscopy, and response to therapy.
More Related Videos
 07:53
Author Spotlight: Advancing 3D Modeling for Enhanced Diagnosis and Treatment of Pulmonary Nodules in Early-Stage Lung Cancer
Published on: October 13, 2023
 11:02
Human Lung Dendritic Cells: Spatial Distribution and Phenotypic Identification in Endobronchial Biopsies Using Immunohistochemistry and Flow Cytometry
Published on: January 20, 2017
Related Concept Videos
 01:23
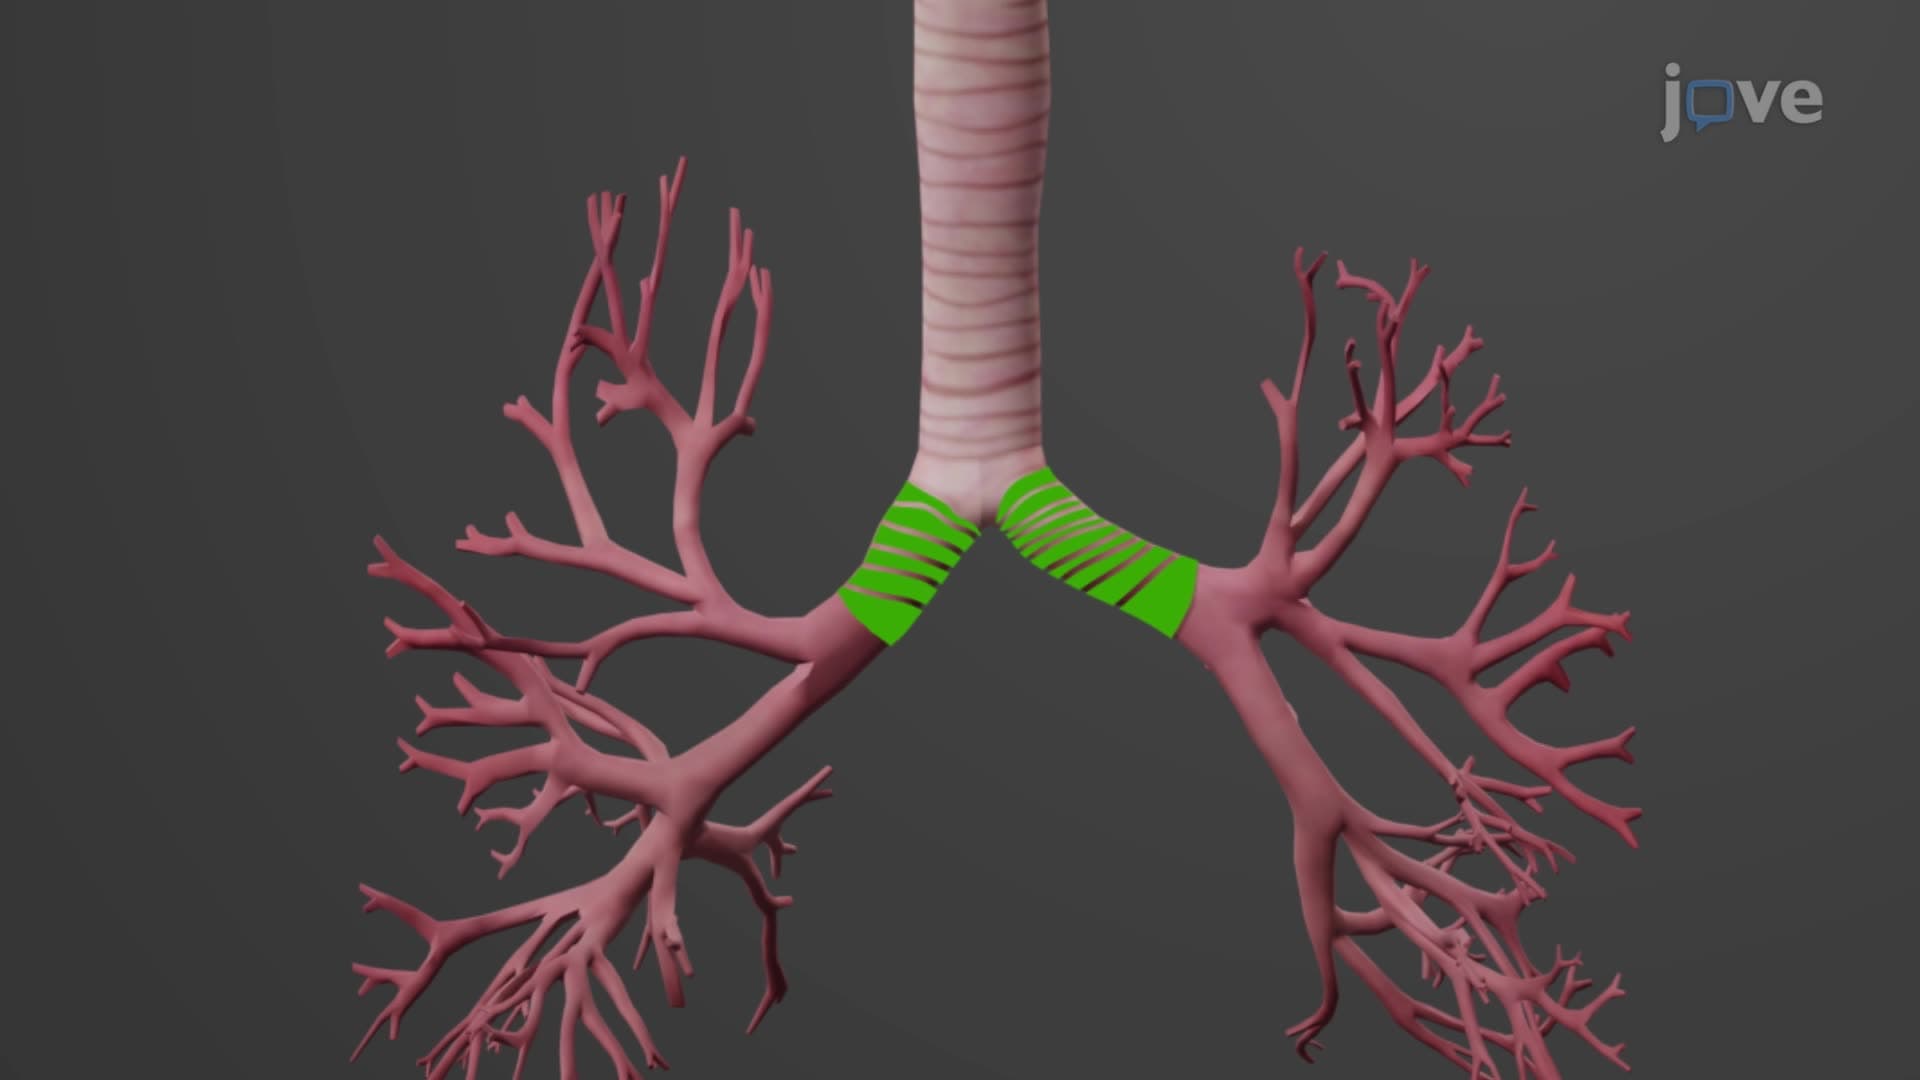
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...