Related Experiment Video
Updated: Jun 28, 2025


The Use of Thermal Infra-Red Imaging to Detect Delayed Onset Muscle Soreness
Published on: January 22, 2012
Physical Therapies for Delayed Onset Muscle Soreness: A Protocol for an Umbrella and Mapping Systematic Review with
Szczepan Wiecha1, Paweł Posadzki2,3, Robert Prill4,5
1Department of Physical Education and Health in Biala Podlaska, Faculty in Biala Podlaska, Jozef Pilsudski University of Physical Education, 00-968 Warsaw, Poland.

Background:
Delayed onset muscle soreness (DOMS), also known as exercise-induced muscle damage (EIMD), is typically caused by strenuous and/or unaccustomed physical exercise. DOMS/EIMD manifests itself in reduced muscle strength and performance levels, increased muscle soreness, swelling, and elevated levels of inflammatory biomarkers. Numerous randomised controlled trials (RCTs) and systematic reviews (SRs) of a wide variety of physiotherapy interventions for reducing the signs and symptoms of DOMS/EIMD have been published. However, these SRs often arrive at contradictory conclusions, impeding decision-making processes.
Objective:
We will systematically review the current evidence on clinical outcomes (efficacy, safety) of physiotherapy interventions for the treatment of DOMS/EIMD in healthy adults. We will also assess the quality of the evidence and identify, map, and summarise data from the available SRs.
Method:
Umbrella review with evidence map and meta-meta-analyses. MEDLINE, Embase, Cochrane Database of Systematic Reviews, Epistemonikos and PEDro will be searched from January 1998 until February 2024. SRs of RCTs of any treatment used by physiotherapists (e.g., low-level laser therapy, electrical stimulation, heat/cold therapy, ultrasound, magnets, massage, manual therapies) to treat DOMS/EIMD in healthy adults will be eligible. Narrative/non-systematic reviews, studies of adolescents/children and medically compromised individuals, of complementary therapies, dietary, nutritional, or pharmacological interventions, as well as self-administered interventions, or those published before 1998, will be excluded. AMSTAR 2 will be used to evaluate the methodological quality of the included SRs. Corrected covered area, will be computed for assessing overlaps among included SRs, and an evidence map will be prepared to describe the credibility of evidence for interventions analysed in the relevant SRs.
Discussion:
DOMS/EIMD is a complex condition, and there is no consensus regarding the standard of clinical/physiotherapeutic care. By critically evaluating the existing evidence, we aim to inform clinicians about the most promising therapies for DOMS/EIMD. This umbrella review has the potential to identify gaps in the existing evidence base that would inform future research. The protocol has been registered at PROSPERO (CRD42024485501].

Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:24
Muscle Recovery and Fatigue
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:24
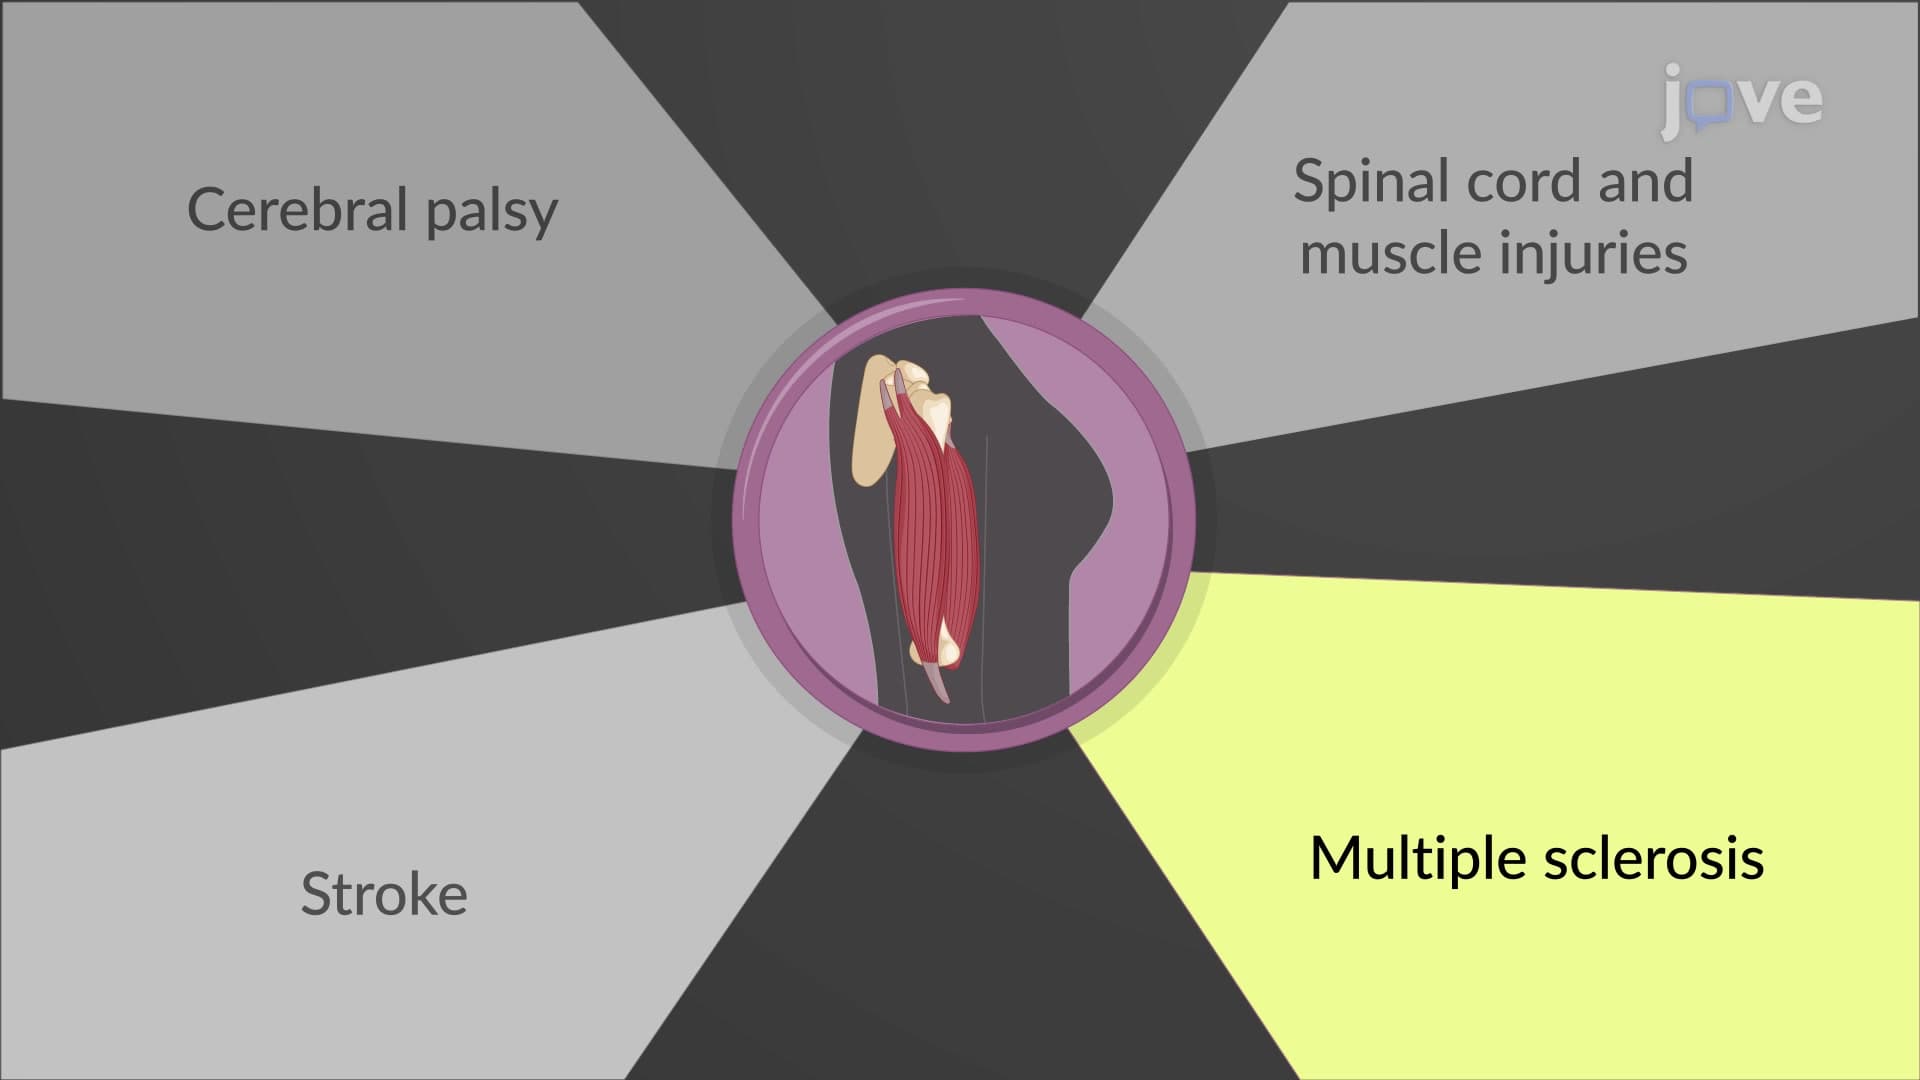
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...