Related Experiment Video
Updated: Jun 28, 2025
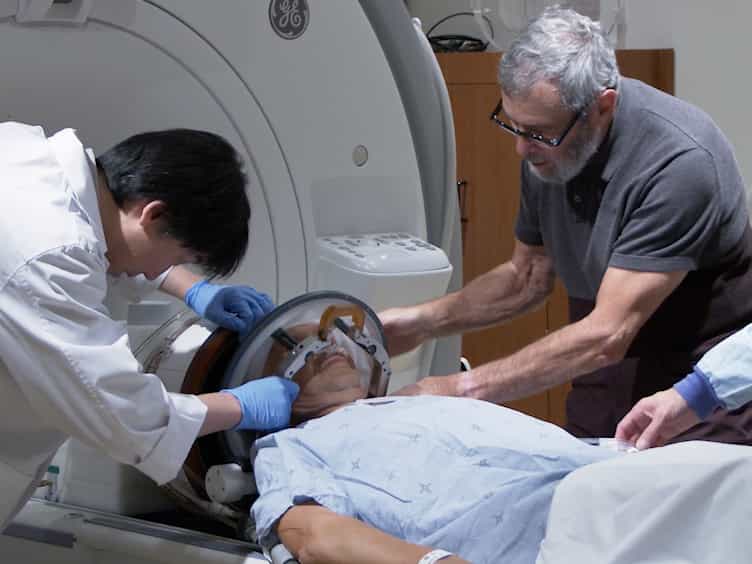

MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
TMS of the left primary motor cortex improves tremor intensity and postural control in primary orthostatic tremor
Florian Schoeberl1,2, James Dowsett3, Cauchy Pradhan2
1Department of Neurology and German Center for Vertigo and Balance Disorders (DSGZ), LMU University Hospital, LMU Munich, Marchioninistrasse 15, 81377, Munich, Germany.

Abstract:
A ponto-cerebello-thalamo-cortical network is the pathophysiological correlate of primary orthostatic tremor. Affected patients often do not respond satisfactorily to pharmacological treatment. Consequently, the objective of the current study was to examine the effects of a non-invasive neuromodulation by theta burst repetitive transcranial magnetic stimulation (rTMS) of the left primary motor cortex (M1) and dorsal medial frontal cortex (dMFC) on tremor frequency, intensity, sway path and subjective postural stability in primary orthostatic tremor. In a cross-over design, eight patients (mean age 70.2 ± 5.4 years, 4 female) with a primary orthostatic tremor received either rTMS of the left M1 leg area or the dMFC at the first study session, followed by the other condition (dMFC or M1 respectively) at the second study session 30 days later. Tremor frequency and intensity were quantified by surface electromyography of lower leg muscles and total sway path by posturography (foam rubber with eyes open) before and after each rTMS session. Patients subjectively rated postural stability on the posturography platform following each rTMS treatment. We found that tremor frequency did not change significantly with M1- or dMFC-stimulation. However, tremor intensity was lower after M1- but not dMFC-stimulation (p = 0.033/ p = 0.339). The sway path decreased markedly after M1-stimulation (p = 0.0005) and dMFC-stimulation (p = 0.023) compared to baseline. Accordingly, patients indicated a better subjective feeling of postural stability both with M1-rTMS (p = 0.007) and dMFC-rTMS (p = 0.01). In conclusion, non-invasive neuromodulation particularly of the M1 area can improve postural control and tremor intensity in primary orthostatic tremor by interference with the tremor network.


Related Concept Videos
 01:22
Indirect Motor Pathways
The vestibulospinal tract originates in the vestibular nuclei of the brainstem. The vestibular system detects changes in...
 01:24
Parkinson's Disease: Treatment
Parkinson's Disease is primarily a result of the loss of dopaminergic neurons in the substantia nigra pars compacta. The cornerstone of...