Related Experiment Video
Updated: Jun 28, 2025
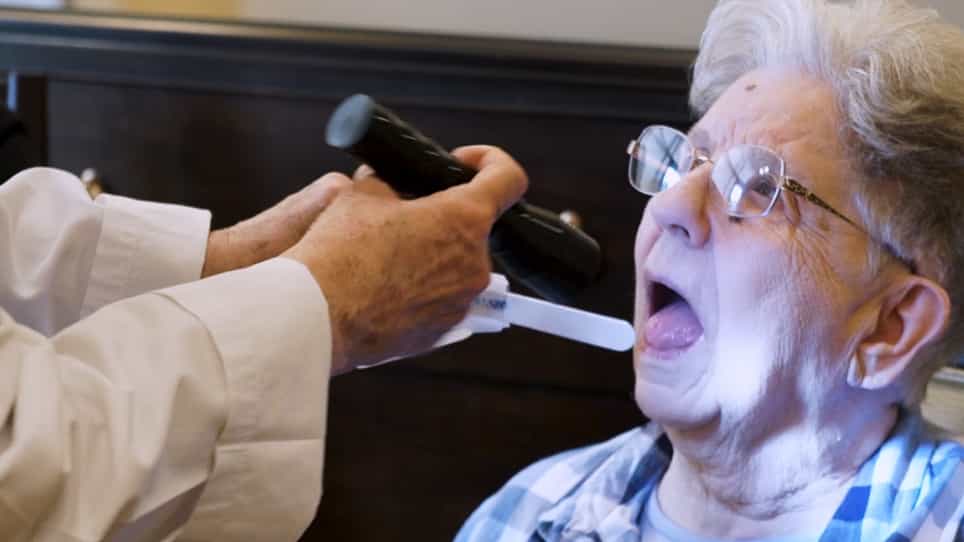
Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Barriers to dental utilization among Medicaid-enrolled young children from primary care practices in Northeast Ohio
David Selvaraj1,2, Neel Agarwal1, Jeffrey M Albert2
1Department of Community Dentistry, Case Western Reserve University School of Dental Medicine, Cleveland, Ohio, USA.

Objectives:
To evaluate the individual and community factors that contribute to dental utilization among young children on Medicaid utilizing the Anderson Model and the Socio-Ecological Framework.
Methods:
This observational cross-sectional study was conducted using baseline data (socio-demographics, clinical dental need) from a cluster-randomized hybrid effectiveness-implementation trial among 1021 child-parent dyads recruited from primary care practices across northeast Ohio. The baseline data were then linked to dental Medicaid claims data (categorized as any dental visit, volume, and type in the past 12 months) and ICD-10 codes from the child's EHR data (individual-level) together with Dental Health Provider Shortage Area (HPSA) status and Area Deprivation Index (ADI) which were obtained at the neighbourhood-level using home address of each dyad (community-level). Multivariable analyses using generalized estimating equations (GEE) accounted for clustering by practice, and models included individual-level alone, and individual + community-level factors to evaluate their effects on dental utilization.
Results:
Medicaid claims data indicated that among the 1021 children (mean age: 4.3 ± 1.1 years; 54.4% males; 43.8% Black, Non-Hispanic), a majority of children were seeing the dentist at least once a year by the age of 4 (56.1%). The mean ADI of their neighbourhoods was 109.22 (20.2) and 27.5% lived in a HPSA area. The GEE analyses revealed that individual factors such as older children, parents being married, and continuous Medicaid enrollment were associated with significantly higher dental utilization. Among community factors, being in a HPSA had an OR = 1.53 (CI: 1.03, 2.27) associated with higher dental utilization.
Conclusions:
Being in a HPSA was associated with higher dental utilization possibly due to dentists or safety net dental clinics in these areas accepting Medicaid-eligible children.
Related Concept Videos
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:30
Barriers to Effective Communication I
Communication barriers include the following:
Physiological barriers: They are limitations caused by a person's health condition or disability, such as hearing loss, poor eyesight, illness, or unconsciousness. An example to overcome this...
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or...
 01:18
Introduction To Health Care Delivery System
The Institute of Medicine (IOM) advocates for a patient-centered, effective, safe, timely, equitable, and effective healthcare system. The National Priorities...
 01:30
Preventive Healthcare Services