Related Experiment Video
Updated: Jun 28, 2025
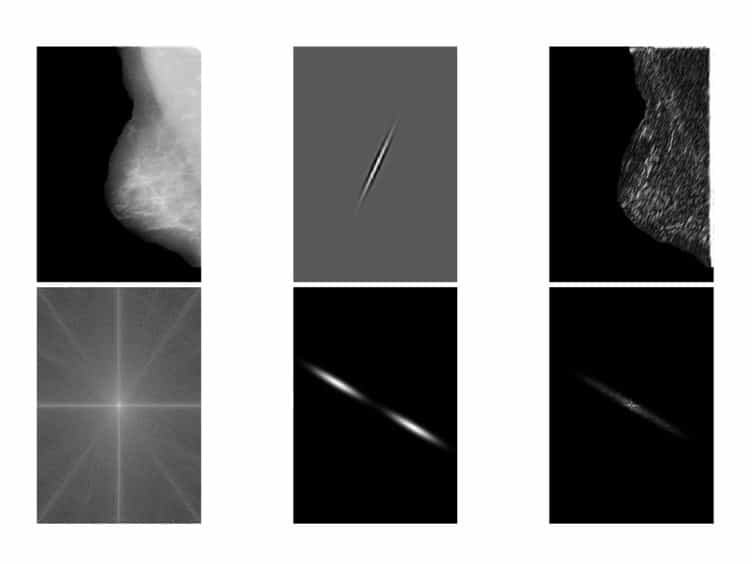

Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Screening mammography performance according to breast density: a comparison between radiologists versus standalone
Mi-Ri Kwon1, Yoosoo Chang2,3,4, Soo-Youn Ham1
1Department of Radiology, Kangbuk Samsung Hospital, Sungkyunkwan University School of Medicine, Seoul, South Korea.

Background:
Artificial intelligence (AI) algorithms for the independent assessment of screening mammograms have not been well established in a large screening cohort of Asian women. We compared the performance of screening digital mammography considering breast density, between radiologists and AI standalone detection among Korean women.
Methods:
We retrospectively included 89,855 Korean women who underwent their initial screening digital mammography from 2009 to 2020. Breast cancer within 12 months of the screening mammography was the reference standard, according to the National Cancer Registry. Lunit software was used to determine the probability of malignancy scores, with a cutoff of 10% for breast cancer detection. The AI's performance was compared with that of the final Breast Imaging Reporting and Data System category, as recorded by breast radiologists. Breast density was classified into four categories (A-D) based on the radiologist and AI-based assessments. The performance metrics (cancer detection rate [CDR], sensitivity, specificity, positive predictive value [PPV], recall rate, and area under the receiver operating characteristic curve [AUC]) were compared across breast density categories.
Results:
Mean participant age was 43.5 ± 8.7 years; 143 breast cancer cases were identified within 12 months. The CDRs (1.1/1000 examination) and sensitivity values showed no significant differences between radiologist and AI-based results (69.9% [95% confidence interval [CI], 61.7-77.3] vs. 67.1% [95% CI, 58.8-74.8]). However, the AI algorithm showed better specificity (93.0% [95% CI, 92.9-93.2] vs. 77.6% [95% CI, 61.7-77.9]), PPV (1.5% [95% CI, 1.2-1.9] vs. 0.5% [95% CI, 0.4-0.6]), recall rate (7.1% [95% CI, 6.9-7.2] vs. 22.5% [95% CI, 22.2-22.7]), and AUC values (0.8 [95% CI, 0.76-0.84] vs. 0.74 [95% CI, 0.7-0.78]) (all P < 0.05). Radiologist and AI-based results showed the best performance in the non-dense category; the CDR and sensitivity were higher for radiologists in the heterogeneously dense category (P = 0.059). However, the specificity, PPV, and recall rate consistently favored AI-based results across all categories, including the extremely dense category.
Conclusions:
AI-based software showed slightly lower sensitivity, although the difference was not statistically significant. However, it outperformed radiologists in recall rate, specificity, PPV, and AUC, with disparities most prominent in extremely dense breast tissue.
More Related Videos
 15:48
Tracking the Mammary Architectural Features and Detecting Breast Cancer with Magnetic Resonance Diffusion Tensor Imaging
Published on: December 15, 2014
 12:57
X-Ray Visualization of Intraductal Ethanol-Based Ablative Treatment for Prevention of Breast Cancer in Rat Models
Published on: December 9, 2022
