Related Experiment Video
Updated: Jun 28, 2025


A Large Animal Model for Acute Kidney Injury by Temporary Bilateral Renal Artery Occlusion
Published on: February 2, 2021
How to use meropenem in pediatric patients undergoing CKRT? Integrated meropenem pharmacokinetic model for critically
Laura Butragueño-Laiseca1,2,3,4, Iñaki F Troconiz5,6, Santiago Grau7
1Pediatric Intensive Care Unit, Hospital General Universitario Gregorio Marañón, Madrid, Spain.

Insights
Standard meropenem dosing is often inadequate for critically ill children, risking toxicity or sub-therapeutic levels. Continuous or extended infusions, especially in patients with kidney issues, are recommended for optimal meropenem (a broad-spectrum antibiotic) dosing.
Area of Science:
- Pharmacokinetics and Pharmacodynamics
- Pediatric Critical Care Medicine
- Infectious Diseases
Background:
- Standard meropenem dosing regimens may not achieve therapeutic systemic concentrations in critically ill children.
- Sub-therapeutic levels or toxicity are concerns in pediatric intensive care unit (ICU) patients, particularly those with acute kidney injury (AKI).
- Optimizing meropenem dosing is crucial for effective treatment of severe infections in vulnerable pediatric populations.
Purpose of the Study:
- To characterize the pharmacokinetic properties of meropenem in critically ill children.
- To evaluate the probability of achieving target pharmacokinetic/pharmacodynamic (PK/PD) endpoints (e.g., fT > MIC) with various meropenem dosing strategies.
- To provide evidence-based recommendations for individualized meropenem dosing in pediatric ICU patients, including those on continuous kidney replacement therapy (CKRT).
Main Methods:
- Population pharmacokinetic (Pop-PK) analysis integrating diverse meropenem concentration data (plasma, filter, urine).
- Monte Carlo simulations to estimate the probability of target attainment (PTA) for different intermittent and continuous infusion regimens.
- Inclusion of 16 critically ill children, with 7 undergoing CKRT, to assess dosing in specific subpopulations.
Main Results:
- Only 33% of children without CKRT achieved the target 90% time above minimum inhibitory concentration (MIC) of 2 mg/L with standard dosing.
- Simulations indicated continuous infusions (60-120 mg/kg/24h) were necessary for patients <30 kg without CKRT.
- For patients on CKRT, extended infusions (40 mg/kg every 8h or 3-4h infusions) were sufficient for those >10 kg, while continuous infusions were needed for <10 kg. Dosing for patients >30 kg required 60 mg/kg/24h continuous infusion.
Conclusions:
- Current meropenem dosing is frequently insufficient in critically ill children, necessitating dose adjustments.
- Extended or continuous meropenem infusions are superior to standard intermittent dosing for achieving therapeutic targets in this population.
- A population pharmacokinetic model supports individualized meropenem dosing strategies for critically ill children, with or without CKRT, to optimize efficacy and minimize toxicity.
Abstract:
Standard dosing could fail to achieve adequate systemic concentrations in ICU children or may lead to toxicity in children with acute kidney injury. The population pharmacokinetic analysis was used to simultaneously analyze all available data (plasma, prefilter, postfilter, effluent, and urine concentrations) and provide the pharmacokinetic characteristics of meropenem. The probability of target fT > MIC attainment, avoiding toxic levels, during the entire dosing interval was estimated by simulation of different intermittent and continuous infusions in the studied population. A total of 16 critically ill children treated with meropenem were included, with 7 of them undergoing continuous kidney replacement therapy (CKRT). Only 33% of children without CKRT achieved 90% of the time when the free drug concentration exceeded the minimum inhibitory concentration (%fT > MIC) for an MIC of 2 mg/L. In dose simulations, only continuous infusions (60-120 mg/kg in a 24-h infusion) reached the objective in patients <30 kg. In patients undergoing CKRT, the currently used schedule (40 mg/kg/12 h from day 2 in a short infusion of 30 min) was clearly insufficient in patients <30 kg. Keeping the dose to 40 mg/kg q8h without applying renal adjustment and extended infusions (40 mg/kg in 3- or 4-h infusion every 12 h) was sufficient to reach 90% fT > MIC (>2 mg/L) in patients >10 kg. In patients <10 kg, only continuous infusions reached the objective. In patients >30 kg, 60 mg/kg in a 24-h infusion is sufficient and avoids toxicity. This population model could help with an individualized dosing approach that needs to be adopted in critically ill pediatric patients. Critically ill patients subjected to or not to CKRT may benefit from the administration of meropenem in an extended or continuous infusion.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:11
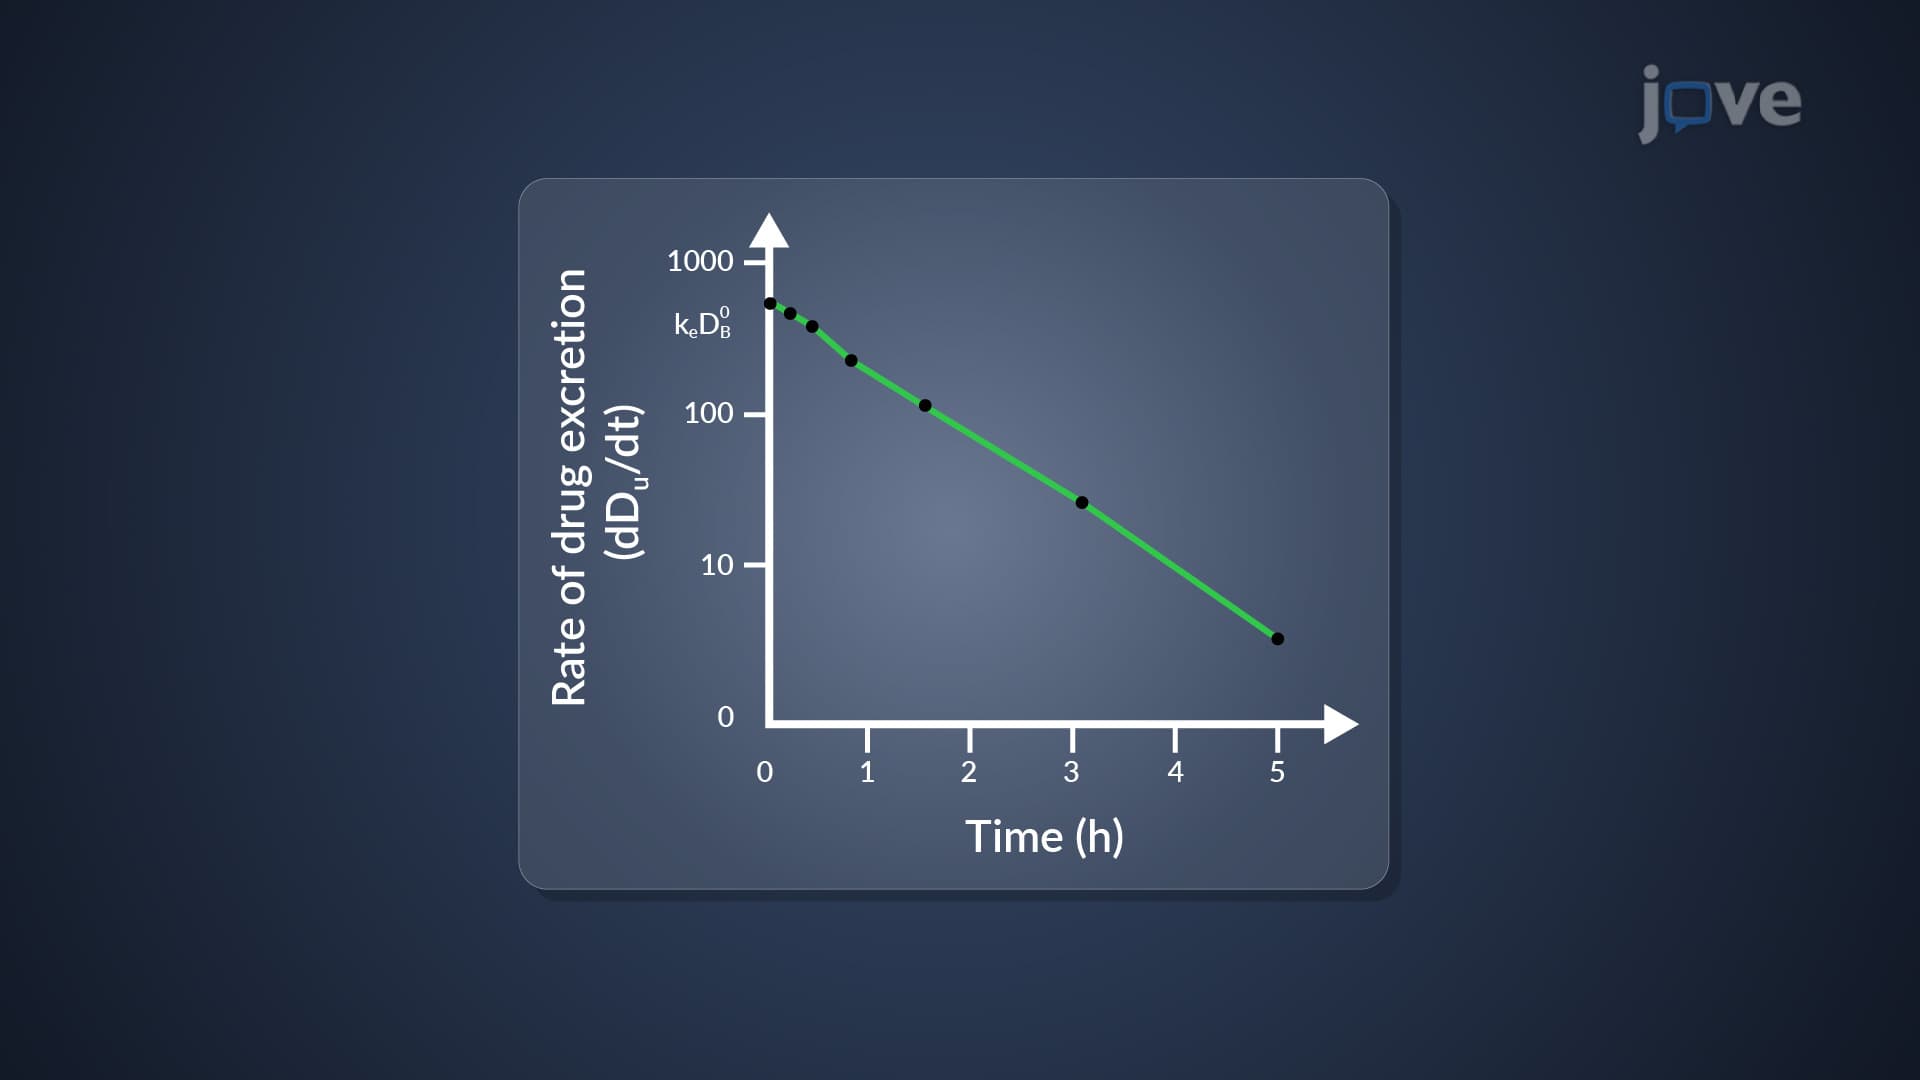
One-Compartment Open Model: Urinary Excretion Data and Determination of k
 01:09
One-Compartment Model: IV Infusion
The one-compartment model for IV infusion uses mathematical equations to describe the rate of change in drug quantity in the body. At steady-state or infusion equilibrium, the drug input...
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 00:59
Model-Independent Approaches for Pharmacokinetic Data: Noncompartmental Analysis
One important characteristic of noncompartmental analyses is that drug exposure increases proportionally with increasing doses. This...