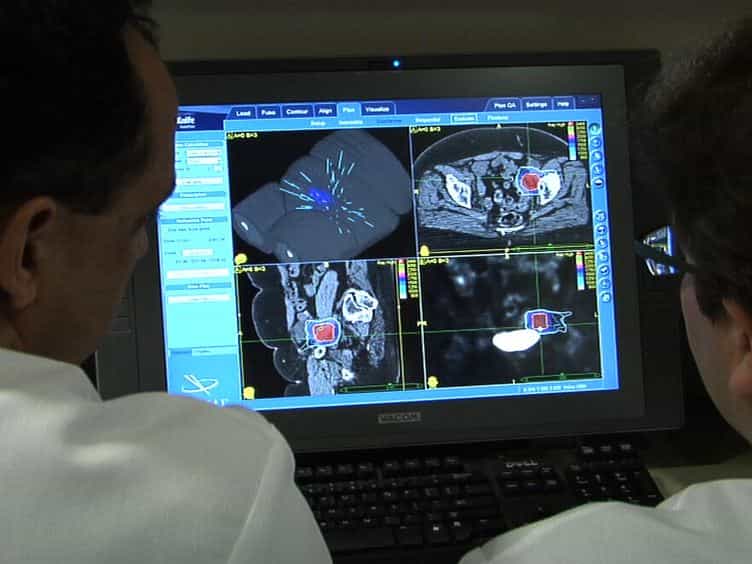
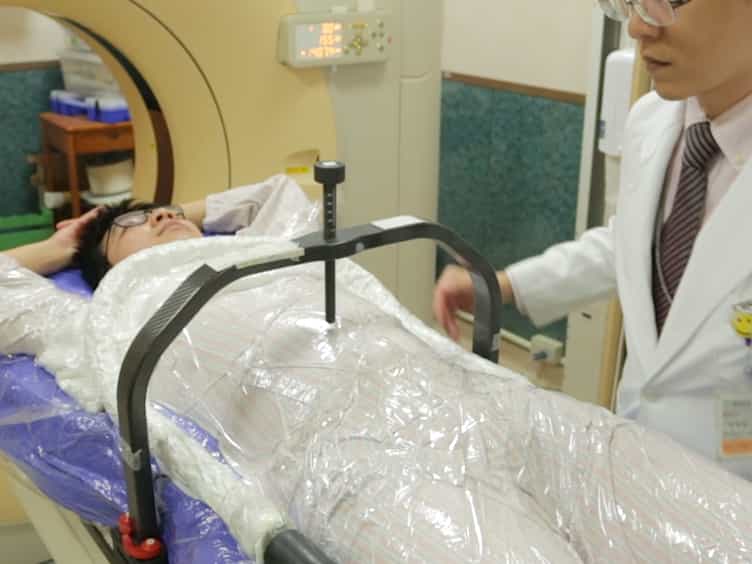
Phase I trial of dose escalation for preoperative stereotactic radiosurgery for patients with large brain metastases
Related Experiment Video
Updated: Jul 29, 2026
Stem Cell Transplantation Strategies for the Restoration of Cognitive Dysfunction Caused by Cranial Radiotherapy
Published on: October 18, 2011
Erin S Murphy1,2,3, Kailin Yang3, John H Suh1,2,3
1Cleveland Clinic Lerner College of Medicine of Case Western Reserve University, Cleveland, Ohio, USA.

Background:
Single-session stereotactic radiosurgery (SRS) or surgical resection alone for brain metastases larger than 2 cm results in unsatisfactory local control. We conducted a phase I trial for brain metastases(>2 cm) to determine the safety of preoperative SRS at escalating doses.
Methods:
Radiosurgery dose was escalated at 3 Gy increments for 3 cohorts based on maximum tumor dimension starting at: 18 Gy for >2-3 cm, 15 Gy for >3-4 cm, and 12 Gy for >4-6 cm. Dose-limiting toxicity was defined as grade III or greater acute toxicity.
Results:
A total of 35 patients/36 lesions were enrolled. For tumor size >2-3 cm, patients were enrolled up to the second dose level (21 Gy); for >3-4 cm and >4-6 cm cohorts the third dose level (21 and 18 Gy, respectively) was reached. There were 2 DLTs in the >3-4 cm arm at 21 Gy. The maximum tolerated dose of SRS for >2-3 cm was not reached; and was 18 Gy for both >3-4 cm arm and >4-6 cm arm. With a median follow-up of 64.0 months, the 6- and 12-month local control rates were 85.9% and 76.6%, respectively. One patient developed grade 3 radiation necrosis at 5 months. The 2-year rate of leptomeningeal disease (LMD) was 0%.
Conclusions:
Preoperative SRS with dose escalation followed by surgical resection for brain metastases greater than 2 cm in size demonstrates acceptable acute toxicity. The phase II portion of the trial will be conducted at the maximum tolerated SRS doses.