Related Experiment Video
Updated: Jun 27, 2025


An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Estrangulated obturatory hernia. Case report of a challenging diagnosis of obstructive syndrome
T A Furtado1, A C Carvalho1, D P C Garcia2
1General Surgery at Hospital Felício Rocho, Belo Horizonte, MG, Brazil.

Introduction And Importance:
Obturator hernia accounts for less than 1 % of all documented cases of pelvic hernias. It most commonly presents as an obstructive syndrome in elderly, multiparous, slim women, characterized by a wider pelvis that facilitates the passage of the hernia sac through the obturator foramen alongside the obturator nerve. In this case, adhering to the SCARE (Updating Consensus Surgical CAse REport) checklist criteria, we present a typical scenario involving an elderly woman who was initially misdiagnosed with a fecaloma, concealing an obturator hernia.
Case Report:
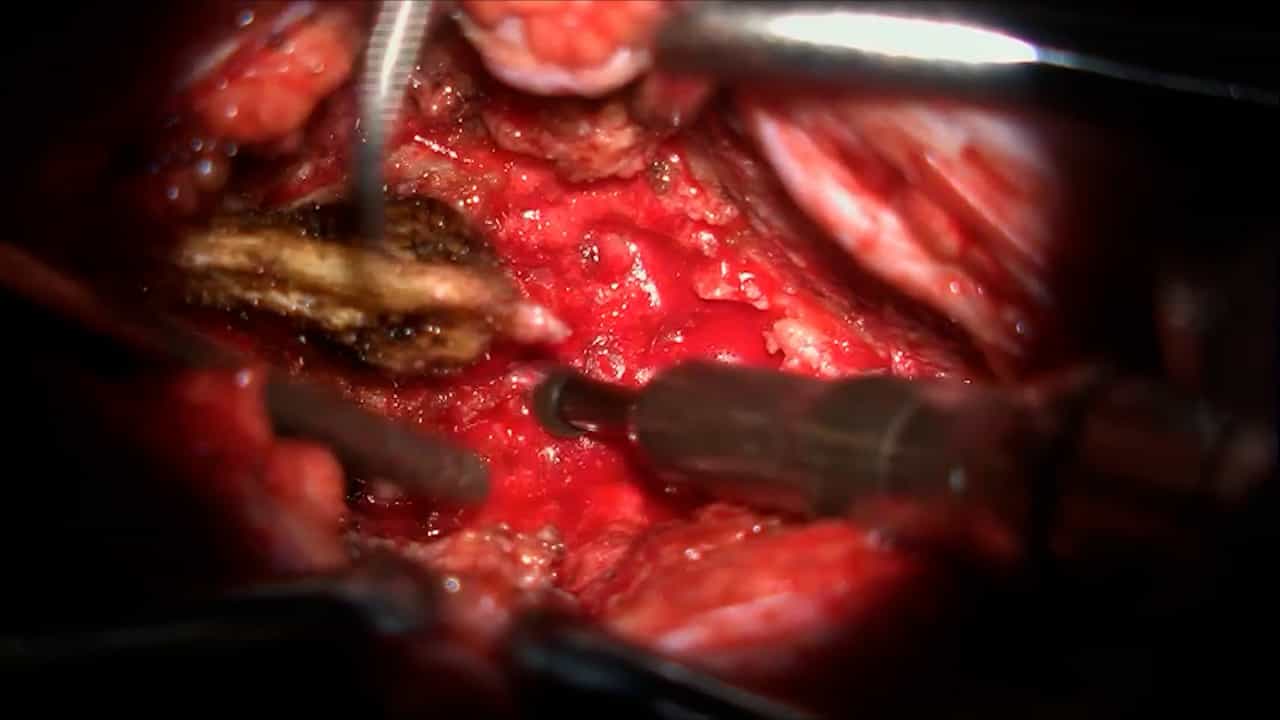
An 85-year-old patient, displaying prodromal signs of senile disease, presented for medical attention with incapacitating abdominal pain in the right iliac fossa, accompanied by nausea and vomiting. Rectal examination revealed the presence of a fecaloma, and glycerin administration was performed rectally. The patient's condition worsened with the development of mental confusion and hyperactive delirium. Abdominal Computer tomography scan (CT scan) revealed right obturator hernia with enteral segment insinuation and dilation of the proximal bowel. An infraumbilical laparotomy was performed. The herniation of an ileal segment and the right ovary through the obturator foramen was identified. The content proved irreducible to manual maneuvers, leading to obturator muscle section following the dissection of the Retzius space. The right round ligament of the uterus was sectioned, and we manage to preserve the Obturatory branch of the lumbar plexus throughout dissection. A polypropylene mesh was positioned and secured with non-absorbable sutures on the Cooper's ligament, iliac crest, and obturator muscle and segmental enterectomy with primary anastomosis using a linear stapler was performed.
Clinical Discussion:
This demanding case brings to the spotlight the importance of reevaluating even the usual cases. We provide our experience bringing together an unusual diagnosis after the conduction of a once diagnosed fecaloma that almost went down to a perforated acute abdomen. Hence the importance of suspect obturator hernia in unknown obstructive abdomen in elderly women.
Conclusion:
With this report we aim to raise awareness of careful propaedeutic inquiry of acute abdomen. We provide our experience bringing together the diagnosis that agrees with our literature review. Elderly patients commonly challenge the clinical evaluation, especially those with signs of senile disease. Thereby, inkling hidden diagnosis in typical scenarios can improve the patient's care in emergency settings.

Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:27
Pneumothorax-II
Clinical Manifestations: