Related Experiment Video
Updated: Jun 27, 2025
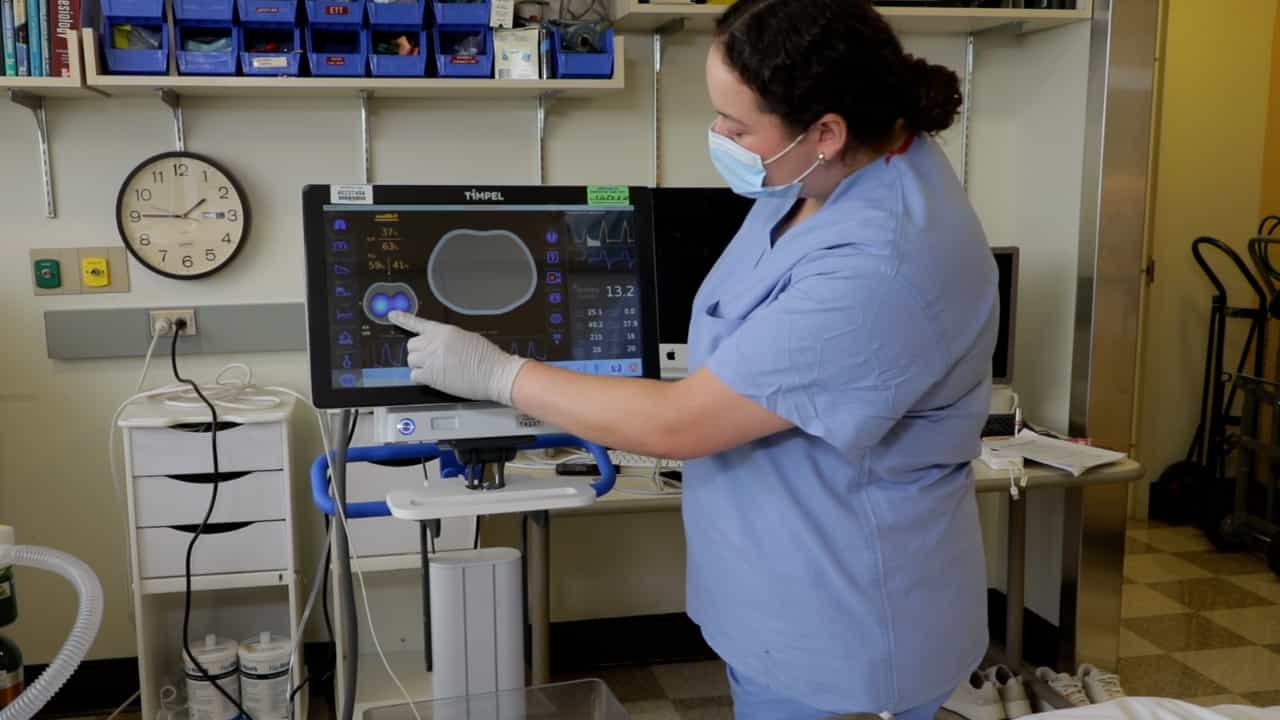
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Determination of optimal positive end-expiratory pressure using electrical impedance tomography in infants under
Ji-Hyun Lee1, Pyoyoon Kang1, Jung-Bin Park1
1Department of Anesthesiology and Pain Medicine, Seoul National University Hospital, Seoul National University College of Medicine, Seoul, South Korea.

Insights
Mechanically ventilated infants require higher positive end-expiratory pressure in the prone position compared to the supine position. Electrical impedance tomography (EIT) aids in individualizing this optimal pressure.
Area of Science:
- Anesthesiology
- Pediatric Critical Care
- Respiratory Physiology
Background:
- Optimizing mechanical ventilation in infants undergoing surgery is crucial for patient outcomes.
- Positive end-expiratory pressure (PEEP) management requires careful consideration of patient positioning.
- Electrical impedance tomography (EIT) offers real-time, non-invasive assessment of lung ventilation distribution.
Purpose of the Study:
- To determine the optimal PEEP levels in infants in both supine and prone positions under general anesthesia.
- To evaluate the utility of EIT in guiding PEEP titration in different positions.
- To compare ventilation parameters between supine and prone positions.
Main Methods:
- Prospective observational study in infants undergoing prone surgery.
- Application of EIT sensor after general anesthesia induction.
- Decremental PEEP trials in supine position to determine optimal settings based on EIT and compliance.
- Continuous monitoring of EIT parameters (e.g., inhomogeneity index, ventilation delay, opening pressure, center of ventilation, pendelluft volume) after prone positioning.
- Determination of optimal PEEP in the prone position using similar methodology.
Main Results:
- The mean EIT-based optimal PEEP was significantly higher in the prone position (10.9 cmH2O) than in the supine position (6.1 cmH2O) (p < .001).
- Significant differences were noted between EIT- and compliance-based optimal PEEP.
- Airway pressures (peak, mean, plateau, driving) increased 1 hour after prone positioning.
- Ventilation balance between ventral and dorsal regions improved in the prone position, indicated by the center of ventilation.
Conclusions:
- The prone position necessitates a higher PEEP compared to the supine position in mechanically ventilated infants under general anesthesia.
- EIT is a valuable tool for identifying individualized optimal PEEP settings.
- Further research may explore the long-term implications of these findings.
Aims:
This study determined the optimal positive end-expiratory pressure levels in infants in supine and prone positions under general anesthesia using electrical impedance tomography (EIT).
Methods:
This prospective observational single-centre study included infants scheduled for surgery in the prone position. An electrical impedance tomography sensor was applied after inducing general anesthesia. The optimal positive end-expiratory pressure in the supine position was determined in a decremental trial based on EIT and compliance. Subsequently, the patient's position was changed to prone. Electrical impedance tomography parameters, including global inhomogeneity index, regional ventilation delay, opening pressure, the centre of ventilation, and pendelluft volume, were continuously obtained up to 1 h after prone positioning. The optimal positive end-expiratory pressure in the prone position was similarly determined.
Results:
Data from 30 infants were analyzed. The mean value of electrical impedance tomography-based optimal positive end-expiratory pressure in the prone position was significantly higher than that in the supine position [10.9 (1.6) cmH2O and 6.1 (0.9) cmH2O, respectively (p < .001)]. Significant differences were observed between electrical impedance tomography- and compliance-based optimal positive end-expiratory pressure. Peak and mean airway, plateau, and driving pressures increased 1 h after prone positioning compared with those in the supine position. In addition, the centre of ventilation for balance in ventilation between the ventral and dorsal regions improved.
Conclusion:
The prone position required higher positive end-expiratory pressure than the supine position in mechanically ventilated infants under general anesthesia. EIT is a promising tool to find the optimal positive end-expiratory pressure, which needs to be individualized.
More Related Videos


Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...