Related Experiment Video
Updated: Jun 27, 2025
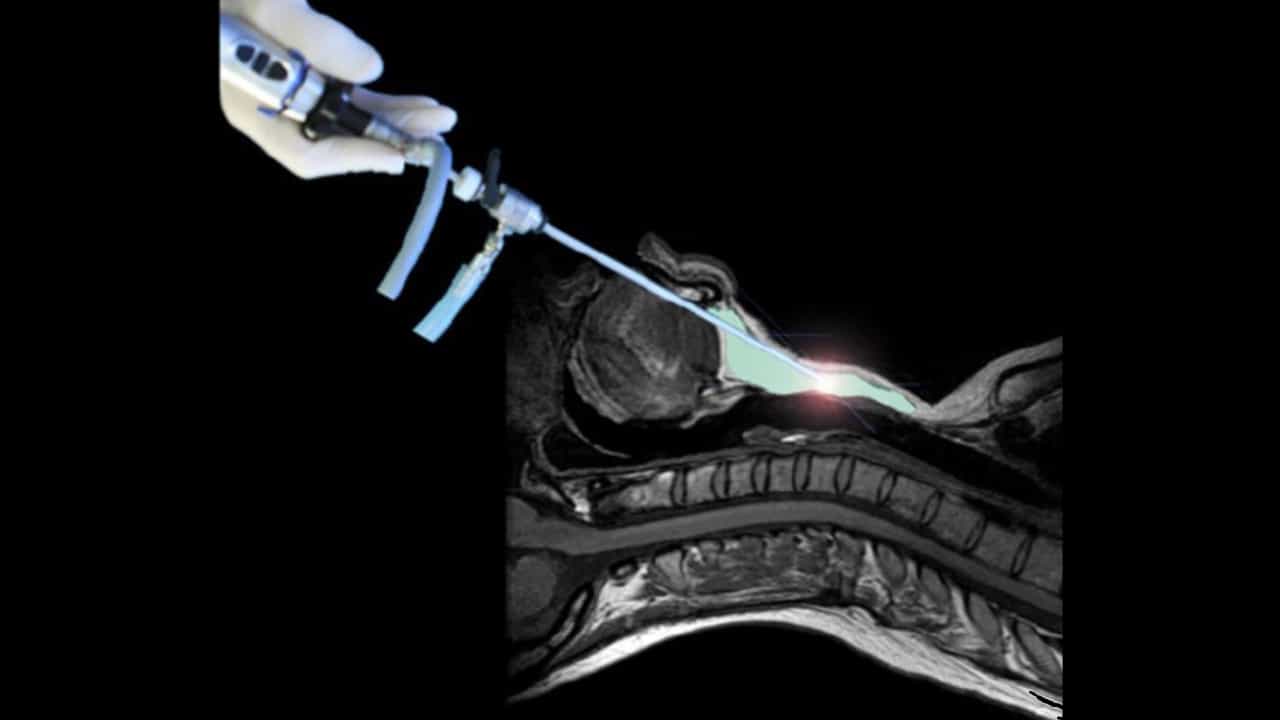

Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Perioperative Management of Paraneoplastic Necrotizing Myopathy in Thyroidectomy: A Case Report
1Anaesthesiology and Perioperative Medicine, Singapore General Hospital, Singapore, SGP.

Abstract:
Perioperative management of patients with myopathies can be challenging due to the increased risk of malignant hyperthermia (MH) and anesthesia-induced rhabdomyolysis (AIR). However, currently, there is no evidence regarding the optimal anesthetic management for paraneoplastic necrotizing myopathy (PNM) (total intravenous anesthetic vs. volatile anesthetics). Here, I report a case where anesthesia was administered safely using volatile anesthetics. A 63-year-old female presented with PNM associated with papillary thyroid carcinoma, necessitating urgent thyroidectomy. The patient, previously diagnosed with anti-3-hydroxy-3-methylglutaryl coenzyme A reductase (HMGCR) antibody-associated myopathy, exhibited progressive weakness and dysphagia, prompting suspicion of PNM. The patient's compromised respiratory status, attributed to tracheal compression by a large goiter, necessitated an urgent thyroidectomy. Anesthetic management considerations included the potential effect of HMGCR-M on respiratory muscles and the need for careful planning to mitigate postoperative complications. The patient underwent total thyroidectomy, left central compartment clearance, and tracheostomy. The surgery proceeded uneventfully, with meticulous monitoring and adjustment of anesthetic agents to maintain hemodynamic stability. Postoperatively, the patient recovered well, demonstrating complete resolution of neurological symptoms during a three-month follow-up. The case underscores the importance of recognizing paraneoplastic syndromes in the context of thyroid surgery and highlights potential challenges faced by anesthesiologists. Despite the lack of established safety data for anesthetic drugs in HMGCR-M necrotizing myopathy, the case demonstrates the successful use of sevoflurane and rocuronium.
Insights
Anesthesia using volatile agents was safely administered to a patient with paraneoplastic necrotizing myopathy (PNM) and anti-HMGCR antibody-associated myopathy. This case provides evidence for safe anesthetic management in rare myopathies.
Area of Science:
- Anesthesiology
- Neurology
- Oncology
Background:
- Perioperative management of myopathies poses challenges due to risks of malignant hyperthermia and anesthesia-induced rhabdomyolysis.
- Optimal anesthetic strategies for paraneoplastic necrotizing myopathy (PNM), particularly anti-3-hydroxy-3-methylglutaryl coenzyme A reductase (HMGCR) antibody-associated myopathy, remain undefined.
- This study addresses the lack of evidence regarding anesthetic choices (total intravenous vs. volatile anesthetics) in PNM.
Observation:
- A 63-year-old female with PNM secondary to papillary thyroid carcinoma required urgent thyroidectomy.
- The patient had a history of anti-HMGCR antibody-associated myopathy, presenting with progressive weakness and dysphagia.
- Respiratory compromise due to tracheal compression necessitated surgical intervention and careful anesthetic planning.
Findings:
- Anesthesia was successfully administered using volatile anesthetics (sevoflurane) and rocuronium during thyroidectomy and tracheostomy.
- Hemodynamic stability was maintained throughout the procedure with meticulous monitoring and adjustments.
- The patient experienced an uneventful recovery with complete resolution of neurological symptoms at three-month follow-up.
Implications:
- This case demonstrates the safe use of volatile anesthetics in a patient with anti-HMGCR antibody-associated necrotizing myopathy.
- It highlights the importance of recognizing paraneoplastic syndromes in patients undergoing thyroid surgery.
- Findings suggest that volatile anesthetics can be a viable option for managing PNM, despite limited existing data.
More Related Videos

Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics