Related Experiment Video
Updated: Jun 27, 2025
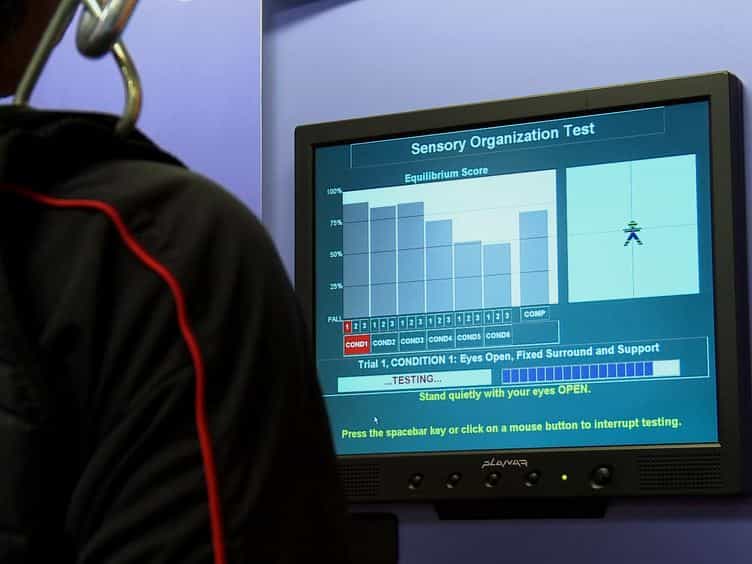

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Effects of additional exercise therapy after a successful vascular intervention for people with symptomatic
Gabriel Cucato1, Paulo Pl Longano2, Daniel Perren3
1Department of Sport, Exercise, and Rehabilitation, Northumbria University, Newcastle-upon-Tyne, UK.

Background:
Peripheral arterial disease (PAD) is characterised by obstruction or narrowing of the large arteries of the lower limbs, usually caused by atheromatous plaques. Most people with PAD who experience intermittent leg pain (intermittent claudication) are typically treated with secondary prevention strategies, including medical management and exercise therapy. Lower limb revascularisation may be suitable for people with significant disability and those who do not show satisfactory improvement after conservative treatment. Some studies have suggested that lower limb revascularisation for PAD may not confer significantly more benefits than supervised exercise alone for improved physical function and quality of life. It is proposed that supervised exercise therapy as adjunctive treatment after successful lower limb revascularisation may confer additional benefits, surpassing the effects conferred by either treatment alone.
Objectives:
To assess the effects of a supervised exercise programme versus standard care following successful lower limb revascularisation in people with PAD.
Search Methods:
We searched the Cochrane Vascular Specialised Register, CENTRAL, MEDLINE, Embase, two other databases, and two trial registers, most recently on 14 March 2023.
Selection Criteria:
We included randomised controlled trials which compared supervised exercise training following lower limb revascularisation with standard care following lower limb revascularisation in adults (18 years and older) with PAD.
Data Collection And Analysis:
We used standard Cochrane methods. Our primary outcomes were maximum walking distance or time (MWD/T) on the treadmill, six-minute walk test (6MWT) total distance, and pain-free walking distance or time (PFWD/T) on the treadmill. Our secondary outcomes were changes in the ankle-brachial index, all-cause mortality, changes in health-related quality-of-life scores, reintervention rates, and changes in subjective measures of physical function. We analysed continuous data by determining the mean difference (MD) and 95% confidence interval (CI), and dichotomous data by determining the odds ratio (OR) with corresponding 95% CI. We used GRADE to assess the certainty of evidence for each outcome.
Main Results:
We identified seven studies involving 376 participants. All studies involved participants who received either additional supervised exercise or standard care after lower limb revascularisation. The studies' exercise programmes varied, and included supervised treadmill walking, combined exercise, and circuit training. The duration of exercise therapy ranged from six weeks to six months; follow-up time ranged from six weeks to five years. Standard care also varied between studies, including no treatment or advice to stop smoking, lifestyle modifications, or best medical treatment. We classified all studies as having some risk of bias concerns. The certainty of the evidence was very low due to the risk of bias, inconsistency, and imprecision. The meta-analysis included only a subset of studies due to concerns regarding data reporting, heterogeneity, and bias in most published research. The evidence was of very low certainty for all the review outcomes. Meta-analysis comparing changes in maximum walking distance from baseline to end of follow-up showed no improvement (MD 159.47 m, 95% CI -36.43 to 355.38; I2 = 0 %; 2 studies, 89 participants). In contrast, exercise may improve the absolute maximum walking distance at the end of follow-up compared to standard care (MD 301.89 m, 95% CI 138.13 to 465.65; I2 = 0 %; 2 studies, 108 participants). Moreover, we are very uncertain if there are differences in the changes in the six-minute walk test total distance from baseline to treatment end between exercise and standard care (MD 32.6 m, 95% CI -17.7 to 82.3; 1 study, 49 participants), and in the absolute values at the end of follow-up (MD 55.6 m, 95% CI -2.6 to 113.8; 1 study, 49 participants). Regarding pain-free walking distance, we are also very uncertain if there are differences in the mean changes in PFWD from baseline to treatment end between exercise and standard care (MD 167.41 m, 95% CI -11 to 345.83; I2 = 0%; 2 studies, 87 participants). We are very uncertain if there are differences in the absolute values of ankle-brachial index at the end of follow-up between the intervention and standard care (MD 0.01, 95% CI -0.11 to 0.12; I2 = 62%; 2 studies, 110 participants), in mortality rates at the end of follow-up (OR 0.92, 95% CI 0.42 to 2.00; I2 = 0%; 6 studies, 346 participants), health-related quality of life at the end of follow-up for the physical (MD 0.73, 95% CI -5.87 to 7.33; I2 = 64%; 2 studies, 105 participants) and mental component (MD 1.04, 95% CI -6.88 to 8.95; I2 = 70%; 2 studies, 105 participants) of the 36-item Short Form Health Survey. Finally, there may be little to no difference in reintervention rates at the end of follow-up between the intervention and standard care (OR 0.91, 95% CI 0.23 to 3.65; I2 = 65%; 5 studies, 252 participants).
Authors' Conclusions:
There is very uncertain evidence that additional exercise therapy after successful lower limb revascularisation may improve absolute maximal walking distance at the end of follow-up compared to standard care. Evidence is also very uncertain about the effects of exercise on pain-free walking distance, six-minute walk test distance, quality of life, ankle-brachial index, mortality, and reintervention rates. Although it is not possible to confirm the effectiveness of supervised exercise compared to standard care for all outcomes, studies did not report any harm to participants from this intervention after lower limb revascularisation. Overall, the evidence incorporated into this review was very uncertain, and additional evidence is needed from large, well-designed, randomised controlled studies to more conclusively demonstrate the role additional exercise therapy has after lower limb revascularisation in people with PAD.
More Related Videos
 13:48
Reduction of Radiation Exposure during Endovascular Treatment of Peripheral Arterial Disease Combining Fiber Optic RealShape Technology and Intravascular Ultrasound
Published on: April 21, 2023
 09:01
Vascular Occlusion Training for Inclusion Body Myositis: A Novel Therapeutic Approach
Published on: June 5, 2010
Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...