Related Experiment Video
Updated: Jun 27, 2025
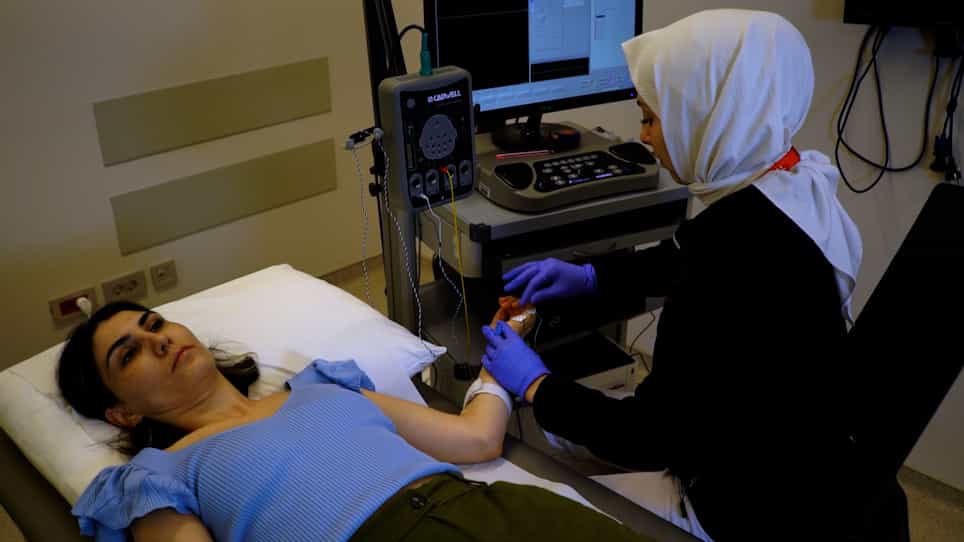
Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
Diagnosis and management of thoracic outlet syndrome in athletes
Andrea T Fisher1, Jason T Lee1
1Division of Vascular Surgery, Stanford University School of Medicine, 780 Welch Road CJ350, Palo Alto, 94304, CA.

Abstract:
The physical demands of sports can place patients at elevated risk of use-related pathologies, including thoracic outlet syndrome (TOS). Overhead athletes in particular (eg, baseball and football players, swimmers, divers, and weightlifters) often subject their subclavian vessels and brachial plexuses to repetitive trauma, resulting in venous effort thrombosis, arterial occlusions, brachial plexopathy, and more. This patient population is at higher risk for Paget-Schroetter syndrome, or effort thrombosis, although neurogenic TOS (nTOS) is still the predominant form of the disease among all groups. First-rib resection is almost always recommended for vascular TOS in a young, active population, although a surgical benefit for patients with nTOS is less clear. Practitioners specializing in upper extremity disorders should take care to differentiate TOS from other repetitive use-related disorders, including shoulder orthopedic injuries and nerve entrapments at other areas of the neck and arm, as TOS is usually a diagnosis of exclusion. For nTOS, physical therapy is a cornerstone of diagnosis, along with response to injections. Most patients first undergo some period of nonoperative management with intense physical therapy and training before proceeding with rib resection. It is particularly essential for ensuring that athletes can return to their baselines of flexibility, strength, and stamina in the upper extremity. Botulinum toxin and lidocaine injections in the anterior scalene muscle might predict which patients will likely benefit from first-rib resection. Athletes are usually satisfied with their decisions to undergo first-rib resection, although the risk of rare but potentially career- or life-threatening complications, such as brachial plexus injury or subclavian vessel injury, must be considered. Frequently, they are able to return to the same or a higher level of play after full recovery.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:26
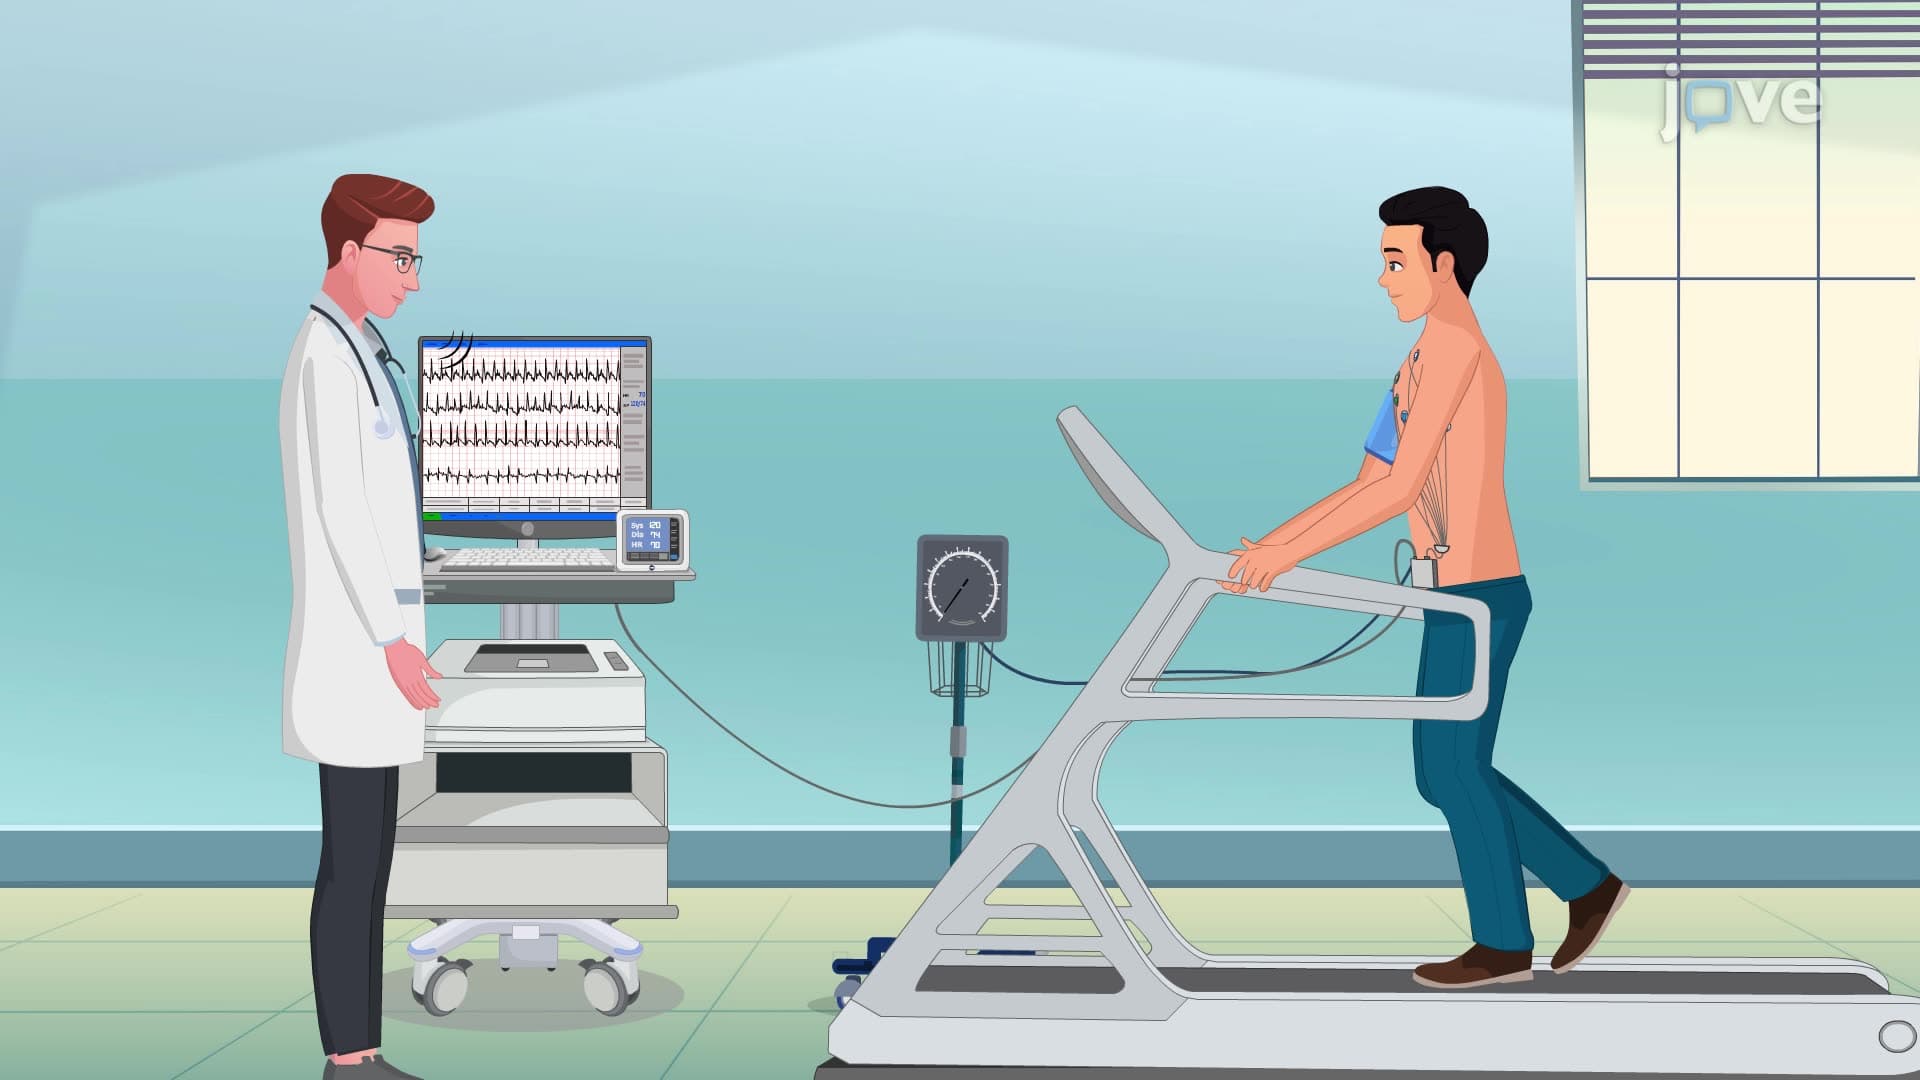
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...