Related Experiment Video
Updated: May 10, 2026
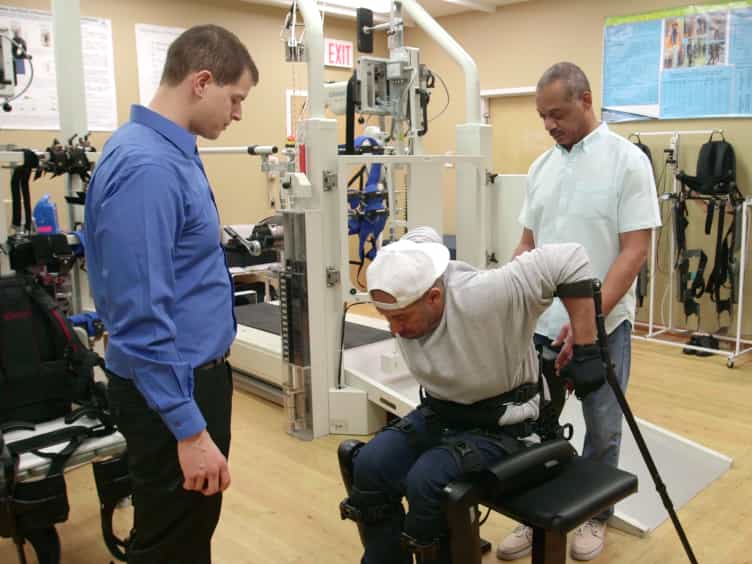

Training Persons with Spinal Cord Injury to Ambulate Using a Powered Exoskeleton
Published on: June 16, 2016
Residual Acetabular Dysplasia at Walking Age: A Study of 470 Hips Treated With Pavlik Harness
Luckshman Bavan1, Thomas Lloyd, Lucy Llewellyn-Stanton
1Oxford University Hospitals NHS Foundation Trust, Oxford, UK.

Insights
Residual acetabular dysplasia (RAD) risk is significant in children treated for developmental dysplasia of the hip (DDH) with a Pavlik harness. Many cases improve spontaneously, suggesting delayed surgical intervention and long-term follow-up are crucial.
Area of Science:
- Pediatric Orthopedics
- Developmental Dysplasia of the Hip (DDH)
- Radiology
Background:
- Developmental Dysplasia of the Hip (DDH) is a common condition requiring effective treatment in infants.
- The Pavlik harness is a widely used method for treating DDH.
- Residual acetabular dysplasia (RAD) can persist or develop after initial DDH treatment.
Purpose of the Study:
- To evaluate acetabular indices in children with a history of DDH treated successfully with a Pavlik harness.
- To identify risk factors associated with the development or persistence of RAD.
- To inform long-term management strategies for children treated for DDH.
Main Methods:
- Retrospective review of 305 children (470 hips) treated for DDH between 2015 and 2020.
- Acetabular indices (AI) measured on radiographs at 2- and 4-year follow-ups, compared to age-matched norms.
- Residual acetabular dysplasia (RAD) defined as AI ≥90th percentile; Level III case-control study.
Main Results:
- RAD was present in 27% of hips at 2-year follow-up and 19% at 4-year follow-up (P=0.032).
- Factors predicting RAD at 2 years included longer treatment duration and lower final ultrasound alpha angles.
- Predictors for RAD at 4 years included older age at treatment initiation, lower alpha angles, and prior RAD at 2 years.
Conclusions:
- The risk of RAD after successful Pavlik harness treatment for DDH is notable.
- A significant proportion of children with RAD at 2 years showed spontaneous improvement by 4 years.
- Routine long-term radiologic follow-up is recommended; surgical intervention for RAD should be considered after age 4.
Background:
This study aims to report on the acetabular indices of walking age children following successful DDH treatment with Pavlik harness and investigate risk factors for residual acetabular dysplasia (RAD).
Methods:
We retrospectively reviewed the data for children treated for DDH at a single centre between 2015 and 2020. Acetabular indices (AI) measured on pelvic radiographs taken at 2- and 4-year follow-up visits were referenced against age-matched and sex-matched normal data. Values ≥90th percentile were considered to represent RAD.
Results:
A total of 305 children with 470 hips were suitable for inclusion. The mean age at treatment initiation was 7.0±4.5 weeks and mean treatment duration was 15.9±4.3 weeks. Overall, 27% and 19% of hips were found to have RAD at 2- (n=448) and 4-year (n=206) follow-up, respectively. The χ 2 test for independence demonstrated that the difference in the proportion of hips with RAD at both time points was significant ( P =0.032). Patients with RAD at 2 years were found to have been treated for longer ( P =0.028) and had lower alpha angles on final ultrasound assessment ( P <0.001). Patients with RAD at 4 years were older at initiation of treatment ( P =0.041), had lower alpha angles on final ultrasound assessment ( P <0.001) and were more likely to have had RAD at 2 years ( P <0.001). Multivariate analysis identified lower alpha angles on final ultrasound to be predictive for RAD at 2 years ( P =0.011), and presence of RAD at 2 years to be predictive for RAD at 4 years ( P <0.001).
Conclusions:
The risk of RAD beyond walking age in children successfully treated with Pavlik harness is not negligible. However, we observed that a significant proportion of children with RAD at 2-year follow-up had spontaneously improved without any intervention. This data suggests that routine long-term radiologic follow-up of children treated with Pavlik harness is necessary, and surgical intervention to address RAD should be delayed until at least 4 years of age.
Level Of Evidence:
Level III-case-control study.