Related Experiment Video
Updated: May 23, 2026
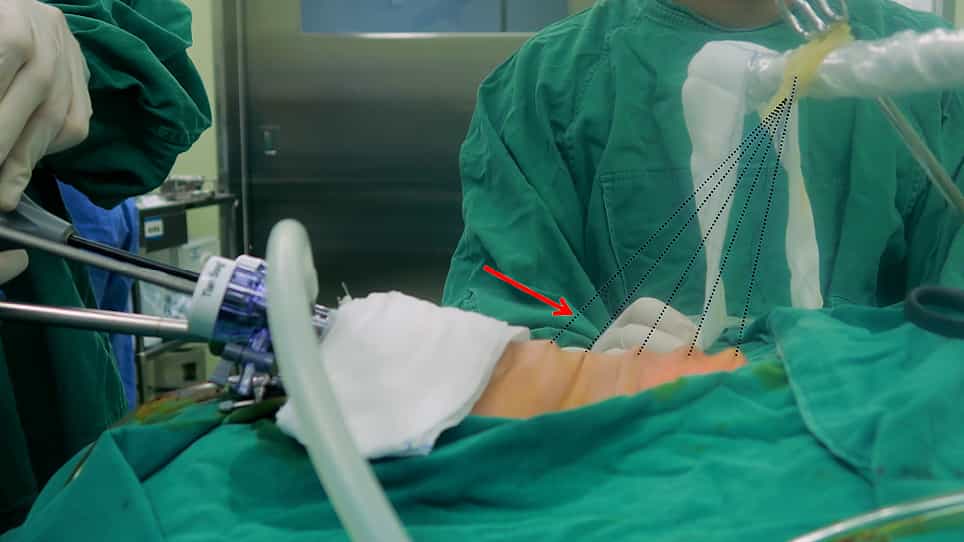
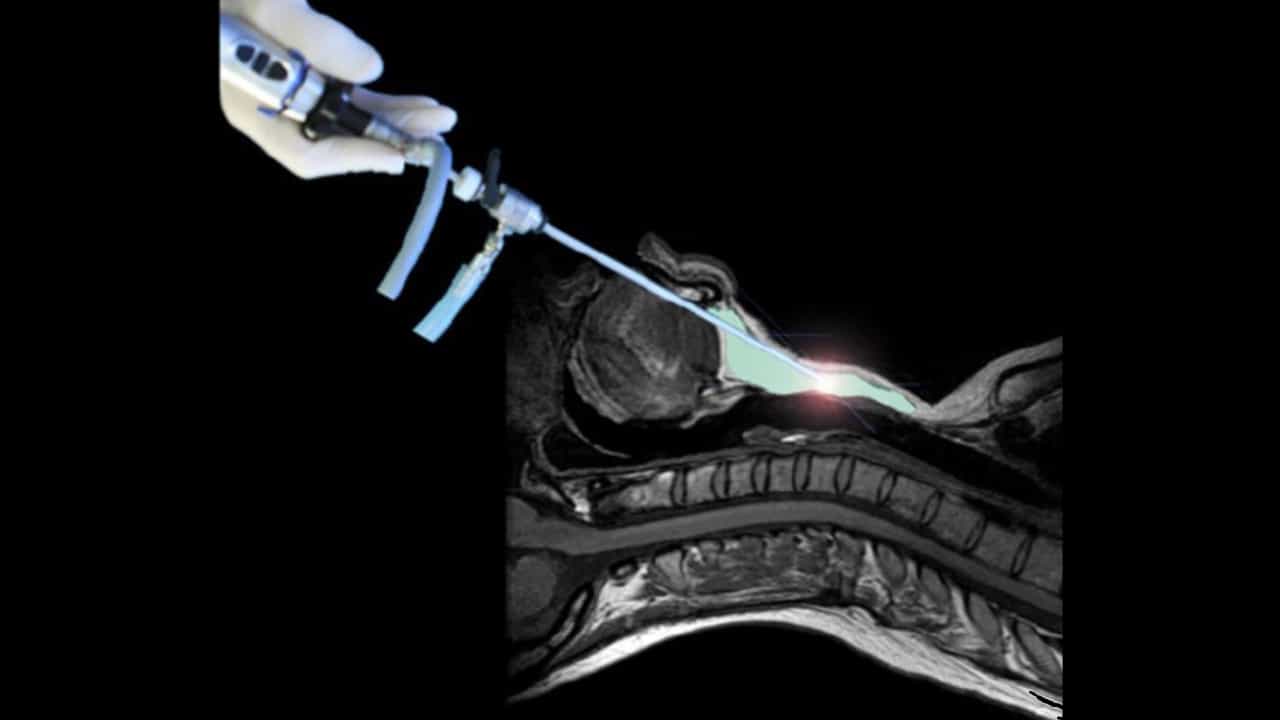
Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Incorporating Microdebrider Use in a Community-Based Thyroidectomy Practice
Keith R Conti1, Jason F Ohlstein1,2, David M Brown1,2
1Division of Otolaryngology, Department of Surgery, St. Luke's University Health Network, Bethlehem, PA, USA.

Abstract:
Objectives: Substernal goiters often require surgery, yet their location presents challenges. Most can be removed via transcervical approach, but extent and relationship to mediastinal structures can merit consideration of sternotomy and assistance of colleagues. Despite widespread use in sinus surgery and previous literature reports, microdebrider use to facilitate transcervical removal of substernal goiters has not been broadly adopted. Our objective was to report our experience with use of the soft tissue shaver to facilitate substernal goiter deliver through a cervical incision in a community-based thyroidectomy practice. Methods: We reviewed thyroidectomy cases performed by a general otolaryngologist (D.M.Y.) in a community setting from January 2017 through December 2019. Four patients required microdebrider use for intracapsular debulking of substernal goiter to allow for transcervical removal. We discuss pre- and perioperative considerations, present computed tomography (CT) and operative images, review surgical technique, and report estimated blood loss (EBL), surgical time (T), complications, and length of stay. Results: Average EBL was 237.5 ml (range 100-500 ml). Average T was 137 minutes (range 121-170 minutes). No patients required sternotomy. One patient developed postoperative hematoma requiring evacuation and cautery of a bleeding site. No other complications were encountered, all patients were discharged after overnight observation. Conclusions: The microdebrider can be safely utilized by general otolaryngologists to facilitate transcervical removal of substernal goiters. Adoption of this familiar tool for a different surgical application can reduce the need for sternotomy, assistance of colleagues, or referral to a tertiary care center, with associated decrease in risk, morbidity, surgical time, length of stay, and cost, and improved patient convenience and satisfaction.
Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...