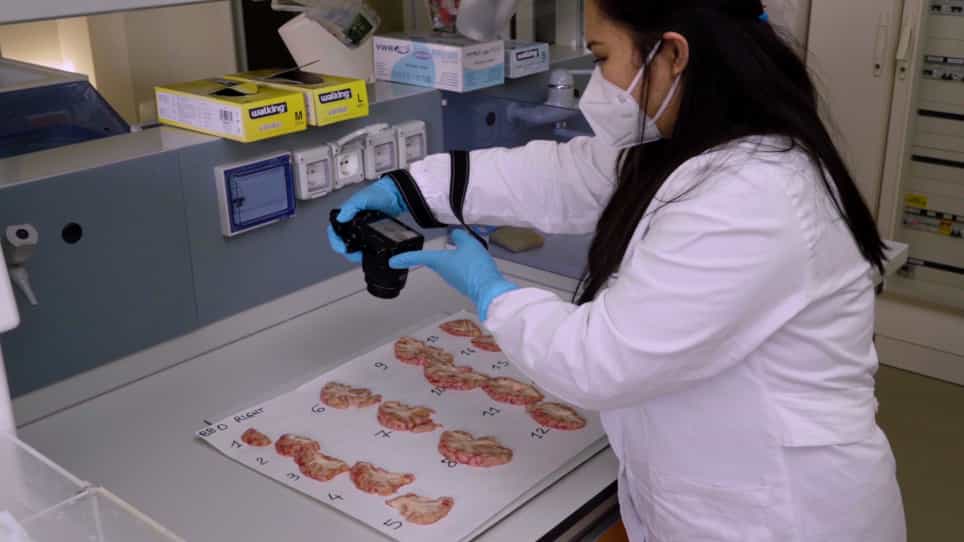
Related Experiment Video
Updated: May 2, 2026


Assessing Cortical Cerebral Microinfarcts on High Resolution MR Images
Published on: November 20, 2015
Boston Criteria v2.0 for Cerebral Amyloid Angiopathy Without Hemorrhage: An MRI-Neuropathologic Validation Study
Aaron R Switzer1, Andreas Charidimou1, Stuart McCarter1
1From the Department of Neurology (A.R.S., S.M., A.A.R., R.D.B., D.S.K., R.C.P., J.G.-R.), Mayo Clinic Rochester, MN; Department of Neurology (A.R.S.), University of Calgary, Canada; Department of Neurology (A.C.), Boston University Chobanian & Avedisian School of Medicine; and Department of Radiology (P.V., C.R.J.), Department of Pathology (A.T.N., R.R.R.), Department of Quantitative Health Sciences (S.A.P.), and Health Sciences Research (T.G.L.), Mayo Clinic Rochester, MN.

Background And Objectives:
Updated criteria for the clinical-MRI diagnosis of cerebral amyloid angiopathy (CAA) have recently been proposed. However, their performance in individuals without symptomatic intracerebral hemorrhage (ICH) presentations is less defined. We aimed to assess the diagnostic performance of the Boston criteria version 2.0 for CAA diagnosis in a cohort of individuals ranging from cognitively normal to dementia in the community and memory clinic settings.
Methods:
Fifty-four participants from the Mayo Clinic Study of Aging or Alzheimer's Disease Research Center were included if they had an antemortem MRI with gradient-recall echo sequences and a brain autopsy with CAA evaluation. Performance of the Boston criteria v2.0 was compared with v1.5 using histopathologically verified CAA as the reference standard.
Results:
The median age at MRI was 75 years (interquartile range 65-80) with 28/54 participants having histopathologically verified CAA (i.e., moderate-to-severe CAA in at least 1 lobar region). The sensitivity and specificity of the Boston criteria v2.0 were 28.6% (95% CI 13.2%-48.7%) and 65.3% (95% CI 44.3%-82.8%) for probable CAA diagnosis (area under the receiver operating characteristic curve [AUC] 0.47) and 75.0% (55.1-89.3) and 38.5% (20.2-59.4) for any CAA diagnosis (possible + probable; AUC 0.57), respectively. The v2.0 Boston criteria were not superior in performance compared with the prior v1.5 criteria for either CAA diagnostic category.
Discussion:
The Boston criteria v2.0 have low accuracy in patients who are asymptomatic or only have cognitive symptoms. Additional biomarkers need to be explored to optimize CAA diagnosis in this population.
Insights
The Boston criteria v2.0 show low accuracy for diagnosing cerebral amyloid angiopathy (CAA) in individuals without symptomatic hemorrhage. New biomarkers are needed for improved diagnosis in this population.
Area of Science:
- Neurology
- Radiology
- Pathology
Background:
- Cerebral amyloid angiopathy (CAA) diagnosis relies on clinical and MRI criteria.
- Updated criteria, Boston criteria version 2.0 (v2.0), have been proposed.
- Their diagnostic performance in non-hemorrhagic, cognitively impaired individuals is less understood.
Purpose of the Study:
- To evaluate the diagnostic accuracy of the Boston criteria v2.0 for CAA.
- To compare v2.0 performance against the previous version (v1.5).
- To assess performance in a cohort with a spectrum of cognitive function.
Main Methods:
- Retrospective analysis of 54 participants from longitudinal aging studies.
- Inclusion criteria: antemortem MRI with gradient-echo sequences and autopsy-confirmed CAA.
- Comparison of Boston criteria v2.0 and v1.5 against histopathological findings.
Main Results:
- Boston criteria v2.0 showed low sensitivity (28.6%) and specificity (65.3%) for probable CAA.
- Performance for any CAA (possible + probable) was also suboptimal (sensitivity 75.0%, specificity 38.5%).
- Version 2.0 did not outperform version 1.5 in diagnostic accuracy.
Conclusions:
- The Boston criteria v2.0 demonstrate limited accuracy in diagnosing CAA in asymptomatic or cognitively impaired individuals.
- Current criteria are insufficient for this population.
- Development of additional biomarkers is crucial for enhancing CAA diagnosis in non-symptomatic cases.