Related Experiment Video
Updated: Jun 11, 2026
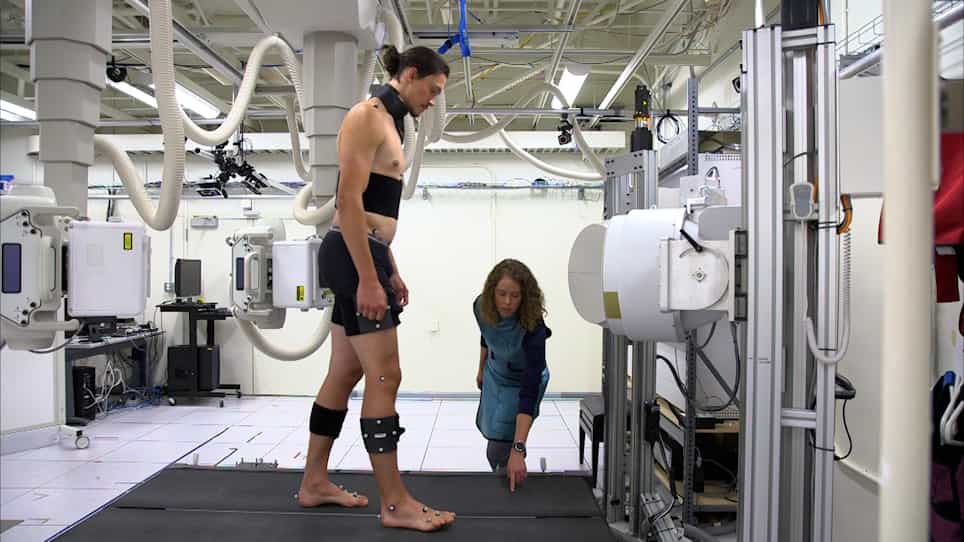

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Understanding the Influence of Single Payer Health Insurance on Socioeconomic Disparities in Total Hip Arthroplasty
Bella Mehta1, Kaylee Ho, J Alex B Gibbons
1From the Department of Medicine, Hospital for Special Surgery, New York, NY (Mehta, Goodman, and Parks), the Department of Medicine, Weill Cornell Medicine, New York, NY (Mehta, Ho, Goodman, Parks, and Wang), the Columbia University Vagelos College of Physicians & Surgeons, New York, NY (Gibbons), the Ontario Institute for Cancer Research, Toronto, ON (Ling), the Sunnybrook Health Sciences Centre, Toronto, ON (Ravi), the Northwell Health, New York, NY (Ibrahim), the The University of Texas Medical Branch, Galveston, TX (Cram), and the Faculty of Medicine, University of Toronto, Toronto, ON (Cram).

Objective:
Access to care varies between countries. It is theorized that income-based disparities in access may be reduced in countries with universal health insurance relative to the United States, but data are currently limited. We hypothesized that income-based differences in total hip arthroplasty (THA) utilization and outcomes would be larger in the United States than in Canada.
Methods:
We retrospectively compared all patients undergoing THA from 2012 to 2018 in Pennsylvania, the United States, and Ontario, Canada. We compared age-standardized and sex-standardized per-capita THA utilization in the United States and Canada overall and across different income strata, where income strata were defined by neighborhood income quintile. We also examined income-based differences in rates of 1-year revision, 90-day mortality, and 90-day readmission.
Results:
Overall THA utilization per 10,000 people per year was higher across all income groups in Pennsylvania compared with Ontario (15.1 versus 8.8, P < 0.001 in lowest-income quintile; 21.4 versus 12.6, P < 0.001 in highest-income quintile). Income-based differences in utilization in the highest-income vs lowest-income quintile groups were greater in Ontario (43.2%) than Pennsylvania (41.7%). The adjusted odds for the lowest-income group compared with the highest-income group of 1-year revision were greater in Ontario compared with Pennsylvania ( P = 0.03), and risk of 90-day mortality and 90-day readmission was similar between the regions.
Conclusion:
Income-based differences in THA utilization were more notable in Ontario than in Pennsylvania. In addition, patients in low-income communities in Ontario were at equal or greater risk relative to high-income community patients for adverse outcomes compared with patients in Pennsylvania. Income-based disparities in THA utilization and outcomes were smaller in the United States than in Canada, in contrast to what might be expected.
Level Of Evidence:
III.
More Related Videos

Related Concept Videos
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:20
Integrated Healthcare System
 01:19
Standards of Care II