Related Experiment Video
Updated: Jun 27, 2025
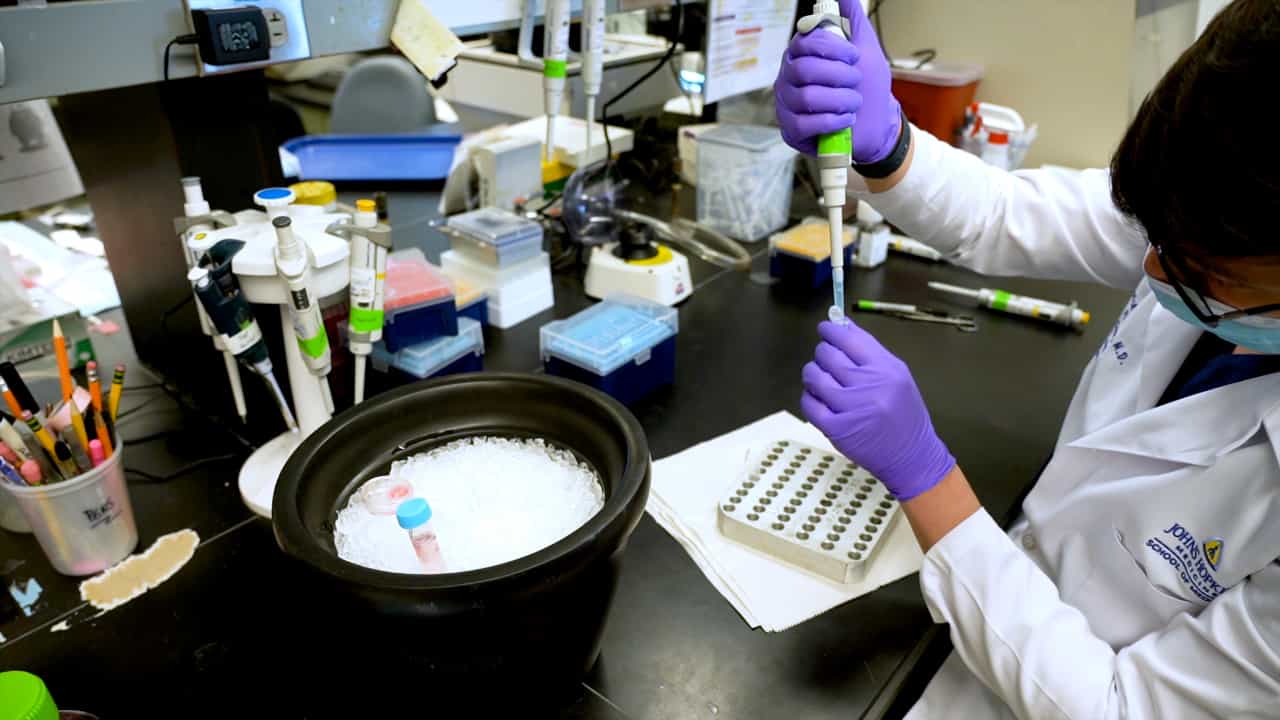
Experimental Model to Evaluate Resolution of Pneumonia
Published on: February 17, 2023
Inflammatory subphenotypes previously identified in ARDS are associated with mortality at intensive care unit
Marleen A Slim1,2, Rombout B E van Amstel3, Lieuwe D J Bos3
1Center for Experimental and Molecular Medicine, Amsterdam University Medical Center, Amsterdam Institute for Infection and Immunity, University of Amsterdam, Meibergdreef 9, 1105 AZ, Amsterdam, The Netherlands. m.a.slim@amsterdamumc.nl.

Background:
Intensive care unit (ICU)-survivors have an increased risk of mortality after discharge compared to the general population. On ICU admission subphenotypes based on the plasma biomarker levels of interleukin-8, protein C and bicarbonate have been identified in patients admitted with acute respiratory distress syndrome (ARDS) that are prognostic of outcome and predictive of treatment response. We hypothesized that if these inflammatory subphenotypes previously identified among ARDS patients are assigned at ICU discharge in a more general critically ill population, they are associated with short- and long-term outcome.
Methods:
A secondary analysis of a prospective observational cohort study conducted in two Dutch ICUs between 2011 and 2014 was performed. All patients discharged alive from the ICU were at ICU discharge adjudicated to the previously identified inflammatory subphenotypes applying a validated parsimonious model using variables measured median 10.6 h [IQR, 8.0-31.4] prior to ICU discharge. Subphenotype distribution at ICU discharge, clinical characteristics and outcomes were analyzed. As a sensitivity analysis, a latent class analysis (LCA) was executed for subphenotype identification based on plasma protein biomarkers at ICU discharge reflective of coagulation activation, endothelial cell activation and inflammation. Concordance between the subphenotyping strategies was studied.
Results:
Of the 8332 patients included in the original cohort, 1483 ICU-survivors had plasma biomarkers available and could be assigned to the inflammatory subphenotypes. At ICU discharge 6% (n = 86) was assigned to the hyperinflammatory and 94% (n = 1397) to the hypoinflammatory subphenotype. Patients assigned to the hyperinflammatory subphenotype were discharged with signs of more severe organ dysfunction (SOFA scores 7 [IQR 5-9] vs. 4 [IQR 2-6], p < 0.001). Mortality was higher in patients assigned to the hyperinflammatory subphenotype (30-day mortality 21% vs. 11%, p = 0.005; one-year mortality 48% vs. 28%, p < 0.001). LCA deemed 2 subphenotypes most suitable. ICU-survivors from class 1 had significantly higher mortality compared to class 2. Patients belonging to the hyperinflammatory subphenotype were mainly in class 1.
Conclusions:
Patients assigned to the hyperinflammatory subphenotype at ICU discharge showed significantly stronger anomalies in coagulation activation, endothelial cell activation and inflammation pathways implicated in the pathogenesis of critical disease and increased mortality until one-year follow up.


Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: