Related Experiment Video
Updated: Jun 26, 2025

A Patient-Derived Xenograft Model for Venous Malformation
Published on: June 15, 2020
A proposal for a revision of the phlebographic classification of congenital venous malformations
Sarah M Bernhard1,2, Franz R Kammer1,2, Marie C Roumet3
1Division of Angiology, Swiss Cardiovascular Center, Inselspital, Bern University Hospital, University of Bern, Bern, Switzerland.

Background:
Venous malformation (VM) is the most frequent type of congenital vascular malformation. In terms of functional outcome local sclerotherapy remains the most important therapeutic tool. For planning and correct estimation and prevention of complications, an exact anatomical classification of the VM is crucial. Not only the drainage, as assessed in the established classification, but also the phlebographic aspect of the internal VM structure itself plays a decisive role. In order to integrate this aspect, we aim to validate a proposal for a revised phlebographic VM classification distinguishing non-lacunar (a) and lacunar (b) types.
Methods:
We retrospectively analyzed all patients with VM in whom a direct puncture phlebography was performed in our clinic between 2009 and 2018 to assess morphology and flow characteristics. Phlebographic assessment included: (I) differentiation of non-lacunar vs. lacunar type; (II) drainage assignment according to the existing classification; (III) adjusted classification combining both. Inter-reader agreement was measured in percentage as well as by the Cohen's kappa coefficient (κ).
Results:
Overall 26 patients were classified as non-lacunar (a) and 41 patients as lacunar (b) VM. For this categorization, inter-reader agreement was 96% (κ=0.91). Classical Puig classification into types I, II, III and IV showed 87% inter-reader agreement (κ=0.78). For the adjusted classification adding the non-lacunar or lacunar characteristic to type I-IV an agreement of 82% (κ=0.77) was achieved.
Conclusions:
Phlebographic differentiation into non-lacunar and lacunar VM is feasible and reliable to distinguish phenotypic subgroups of patients with VM. We therefore propose to integrate this parameter of the internal VM structure into the existing classification.
More Related Videos
 08:05
Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
 14:58
Comprehensive Endovascular and Open Surgical Management of Cerebral Arteriovenous Malformations
Published on: October 20, 2017
Related Concept Videos
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
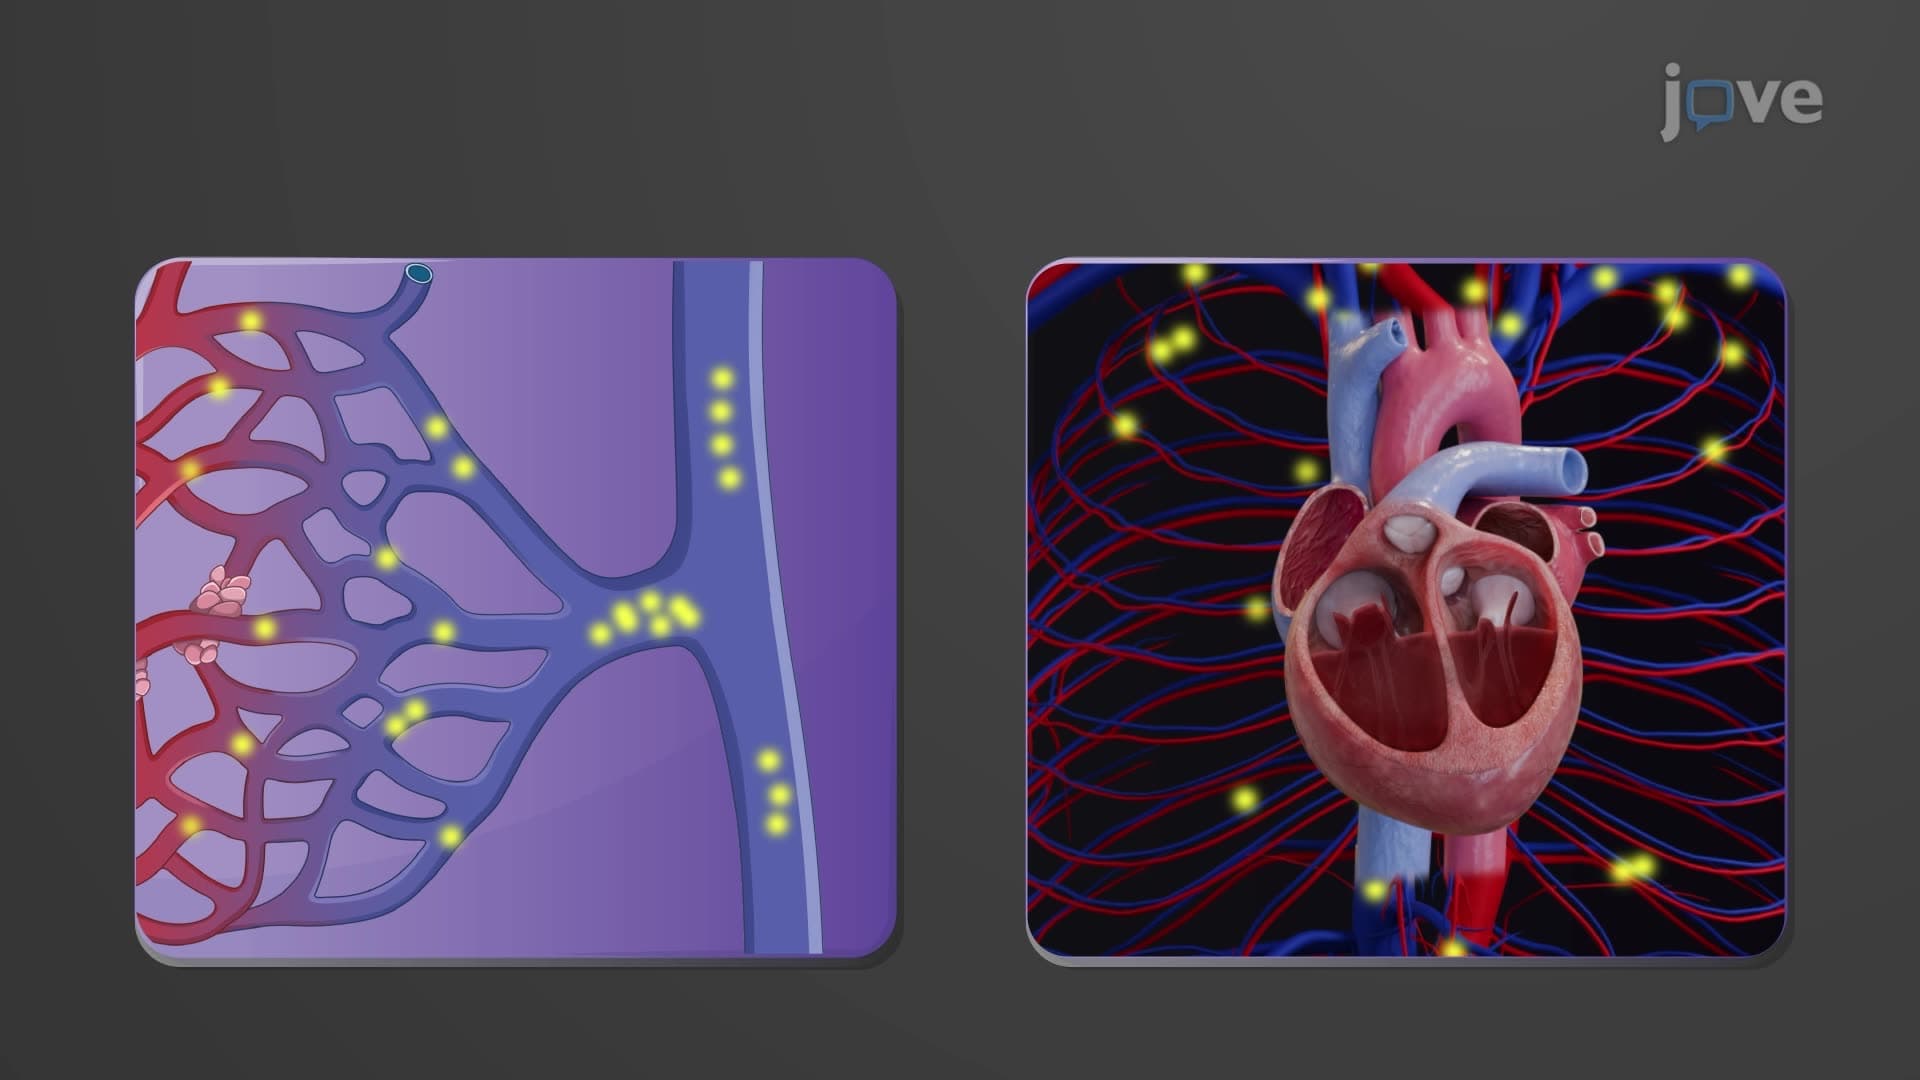 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
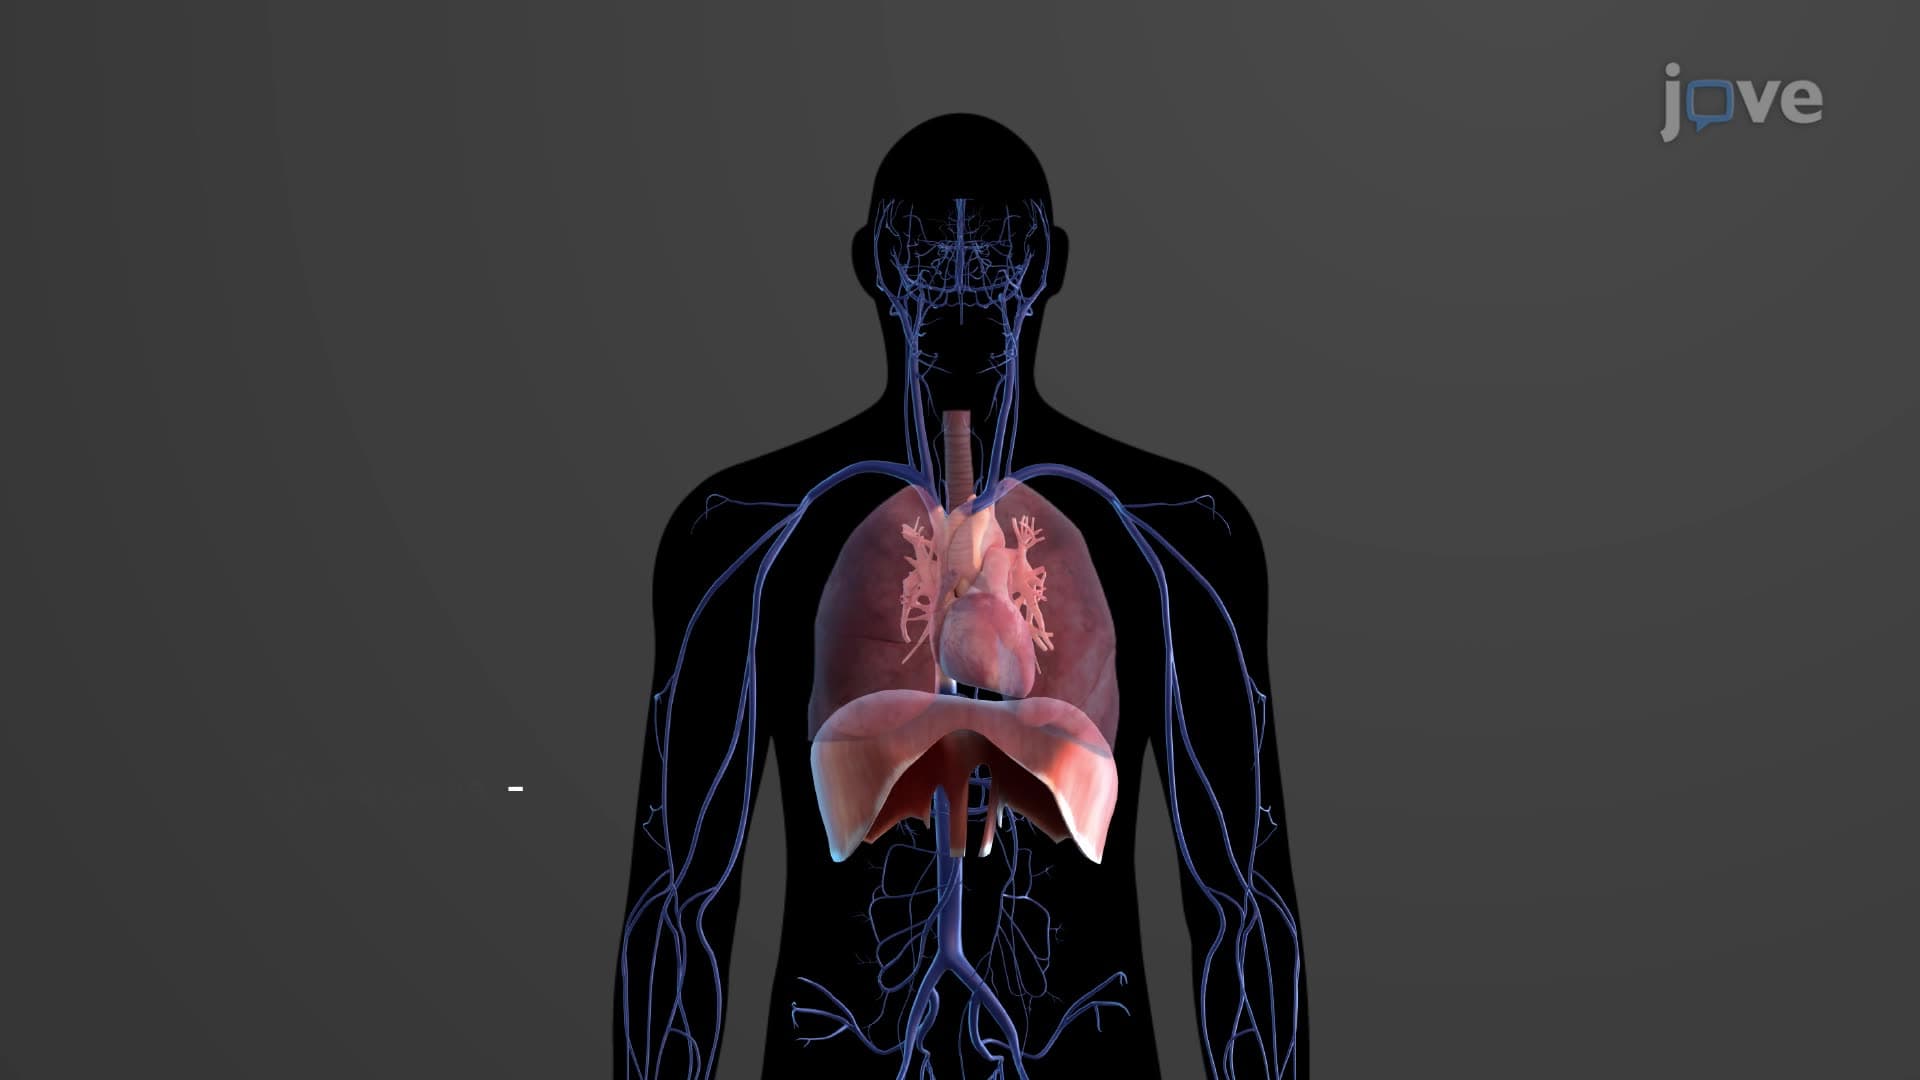 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
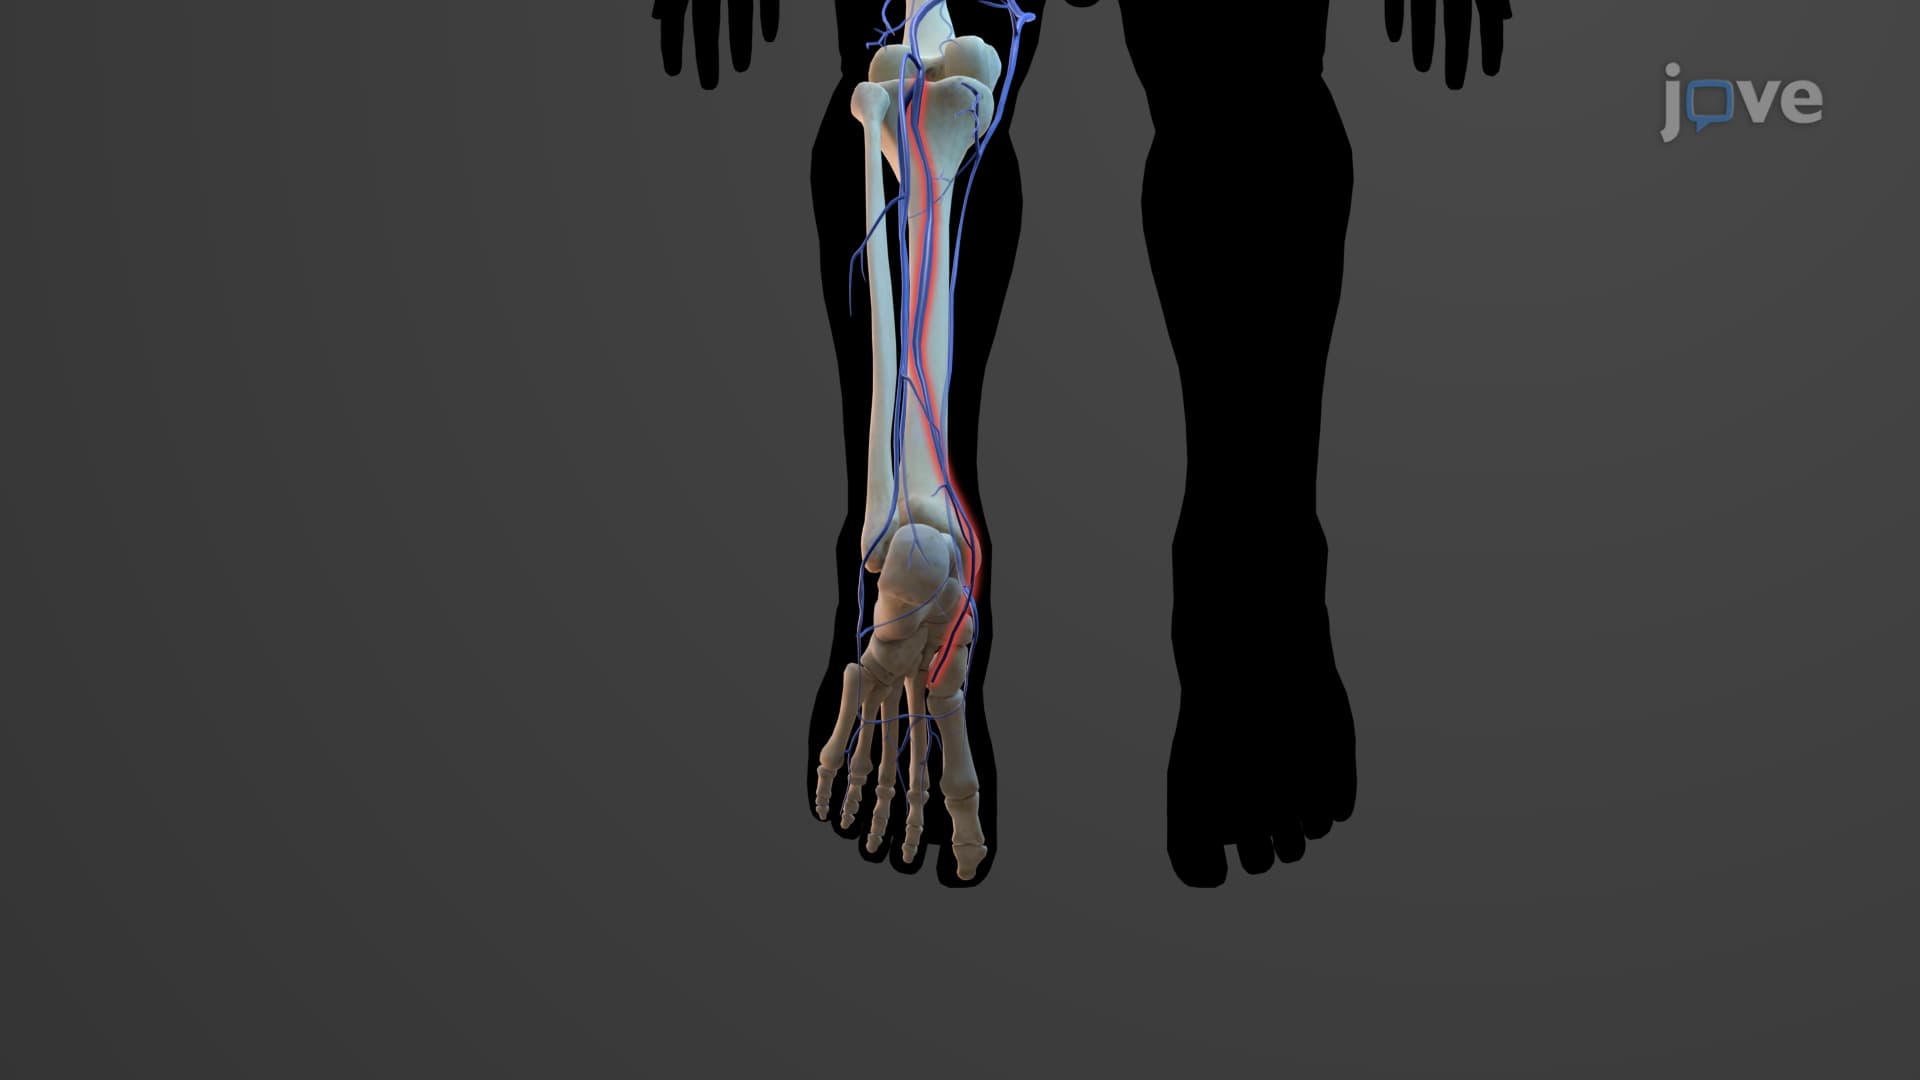 01:15
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...