Related Experiment Video
Updated: Jun 26, 2025
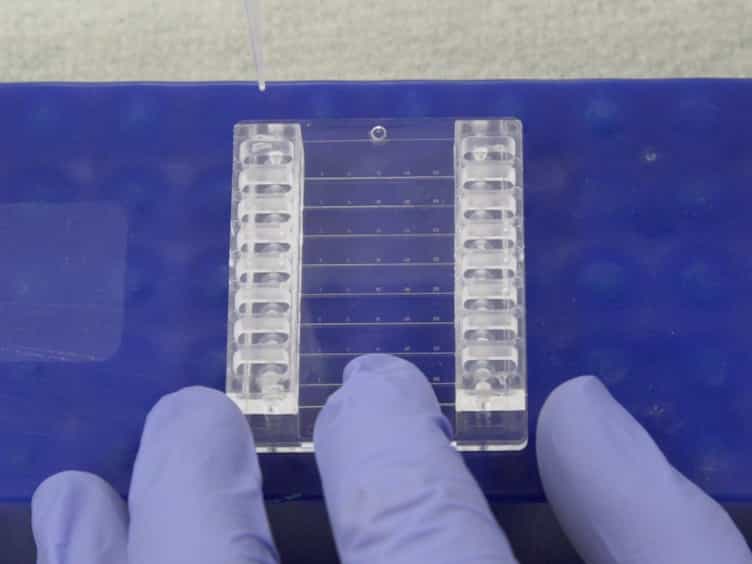

A Microfluidic Flow Chamber Model for Platelet Transfusion and Hemostasis Measures Platelet Deposition and Fibrin Formation in Real-time
Published on: February 14, 2017
Activated clotting time value as an independent predictor of postoperative bleeding and transfusion
Rafael Maniés Pereira1,2, Diogo Magueijo3, Nuno Carvalho Guerra1
1Department of Cardiothoracic Surgery, Hospital de Santa Maria, Centro Hospitalar Lisboa Norte, Lisbon, Portugal.

Objectives:
Activated clotting time (ACT) is commonly used to monitor anticoagulation during cardiac surgeries. Final ACT values may be essential to predict postoperative bleeding and transfusions, although ideal values remain unknown. Our aim was to evaluate the utility of ACT as a predictor of postoperative bleeding and transfusion use.
Methods:
Retrospective study (722 patients) submitted to surgery between July 2018-October 2021. We compared patients with final ACT < basal ACT and final ACT ≥ basal ACT and final ACT < 140 s with ≥140 s. Continuous variables were analysed with the Wilcoxon rank-sum test; categorical variables using Chi-square or Fisher's exact test. A linear mixed regression model was used to analyse bleeding in patients with final ACT < 140 and ≥140. Independent variables were analysed with binary logistic regression models to investigate their association with bleeding and transfusion.
Results:
Patients with final ACT ≥ 140 s presented higher postoperative bleeding than final ACT < 140 s at 12 h (P = 0.006) and 24 h (**P = 0.004). Cardiopulmonary bypass (CPB) time [odds ratio (OR) 1.009, 1.002-1.015, 95% confidence interval (CI)] and masculine sex (OR 2.842,1.721-4.821, 95% CI) were significant predictors of bleeding. Patients with final ACT ≥ 140 s had higher risk of UT (OR 1.81, 1.13-2.89, 95% CI; P = 0.0104), compared to final ACT < 140 s. CPB time (OR 1.019,1.012-1.026, 95% CI) and final ACT (OR 1.021,1.010-1.032, 95% CI) were significant predictors of transfusion. Female sex was a predictor of use of transfusion, with a probability for use of 27.23% (21.84-33.39%, 95% CI) in elective surgeries, and 60.38% (37.65-79.36%, 95% CI) in urgent surgeries, higher than in males.
Conclusions:
Final ACT has a good predictive value for the use of transfusion. Final ACT ≥ 140 s correlates with higher risk of transfusion and increased bleeding. The risk of bleeding and transfusion is higher with longer periods of CPB. Males have a higher risk of bleeding, but females have a higher risk of transfusion.


Related Concept Videos
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:09
Coagulation
During the coagulation phase, clotting factors, or procoagulants, play a vital role in initiating and progressing the coagulation cascade. This cascade is a series of reactions...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...