Related Experiment Video
Updated: Jun 26, 2025


Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
Mitral annular disjunction and its progression during childhood in Marfan syndrome
Tam T Doan1,2, Alejandra Iturralde Chavez1,2, Santiago O Valdes1,2
1Division of Cardiology, Texas Children's Hospital, 6651 Main Street MC-E1920, Houston, TX 77030, USA.

Aims:
Data on mitral annular disjunction (MAD) in children with Marfan syndrome (MFS) are sparse. To investigate the diagnostic yield of MAD by echocardiography and cardiac magnetic resonance imaging (CMR), its prevalence and progression during childhood.
Methods And Results:
We included patients <21 years old with MFS, defined by 2010 Ghent criteria and a pathogenic FBN1 variant or ectopia lentis. Two readers measured systolic separation between the mitral valve (MV) posterior hinge point and left ventricular (LV) myocardium on initial and subsequent imaging. MAD was defined as MV-LV separation ≥2 mm, MV prolapse (MVP) as atrial displacement ≥2 mm. Kappa coefficients evaluated echocardiogram-CMR agreement. Bland-Altman and intraclass correlation coefficients (ICCs) assessed inter-rater and inter-modality reliability. Univariable mixed-effects linear regression was used to evaluate longitudinal changes of MAD. MAD was detected in 60% (110/185) eligible patients. MVP was present in 48% (53/110) of MAD and MAD in 90% (53/59) of MVP. MAD detection by CMR and echocardiography had 96% overall agreement (Kappa = 0.89, P < 0.001) and a 0.32 mm estimate bias (95% CI 0.00, 0.65). ICC by echocardiography, CMR, and between modalities were 0.97 (95% CI 0.93, 0.98), 0.92 (95% CI 0.79, 0.97), and 0.91 (95% CI 0.85, 0.94), respectively. MAD was associated with aortic root dilation (P < 0.001). MAD was found in children of all ages, increased +0.18 mm/year (95% CI +0.14, +0.22) during a median duration of 5.5 years (IQR 3.1, 7.5 years). MAD indexed by height yielded a constant value +0.0002 mm/m/year (95% CI -0.0002, +0.0005 mm/m/year).
Conclusion:
MAD was common in pediatric MFS and was associated with aortic root dilation. MAD detection by echocardiography and CMR was highly reliable, suggesting that routine assessment in MFS is feasible. MAD was present in neonates and progressed over time but remained constant when indexing by height. Further studies are needed to evaluate MAD as a biomarker for clinical outcomes in pediatric MFS.
Insights
Mitral annular disjunction (MAD) is common in children with Marfan syndrome (MFS), affecting 60% of patients and associating with aortic root dilation. Echocardiography and cardiac magnetic resonance imaging (CMR) reliably detect MAD, which progresses with age but normalizes when indexed by height.
Area of Science:
- Cardiology
- Pediatric Cardiology
- Medical Imaging
Background:
- Data on mitral annular disjunction (MAD) in pediatric Marfan syndrome (MFS) are limited.
- Understanding MAD's prevalence, progression, and diagnostic methods in MFS is crucial for early intervention.
Purpose of the Study:
- To investigate the diagnostic yield of MAD using echocardiography and cardiac magnetic resonance imaging (CMR) in children with MFS.
- To determine the prevalence and progression of MAD throughout childhood in MFS patients.
Main Methods:
- Retrospective analysis of pediatric MFS patients (<21 years) diagnosed by 2010 Ghent criteria and FBN1 variant or ectopia lentis.
- Two readers measured mitral valve (MV)-left ventricular (LV) myocardial separation (MAD) and MV prolapse (MVP) on initial and follow-up echocardiograms and CMRs.
- Statistical analysis included agreement (Kappa, ICC) and longitudinal change (mixed-effects linear regression) evaluation.
Main Results:
- MAD was detected in 60% of eligible MFS patients.
- Echocardiography and CMR showed high agreement (Kappa=0.89) and reliability (ICC=0.91-0.97) for MAD detection.
- MAD was associated with aortic root dilation and progressed by +0.18 mm/year, but remained constant when indexed by height.
Conclusions:
- Mitral annular disjunction is a common finding in pediatric Marfan syndrome, frequently associated with aortic root dilation.
- Echocardiography and CMR are reliable modalities for routine MAD assessment in pediatric MFS.
- MAD progresses with age but normalizes when height-indexed, suggesting potential as a clinical outcome biomarker.


Related Concept Videos
 01:27
Development of the Heart
As the embryo undergoes lateral folding, these paired tubes approach each other, merging into a single primitive heart...
 01:25
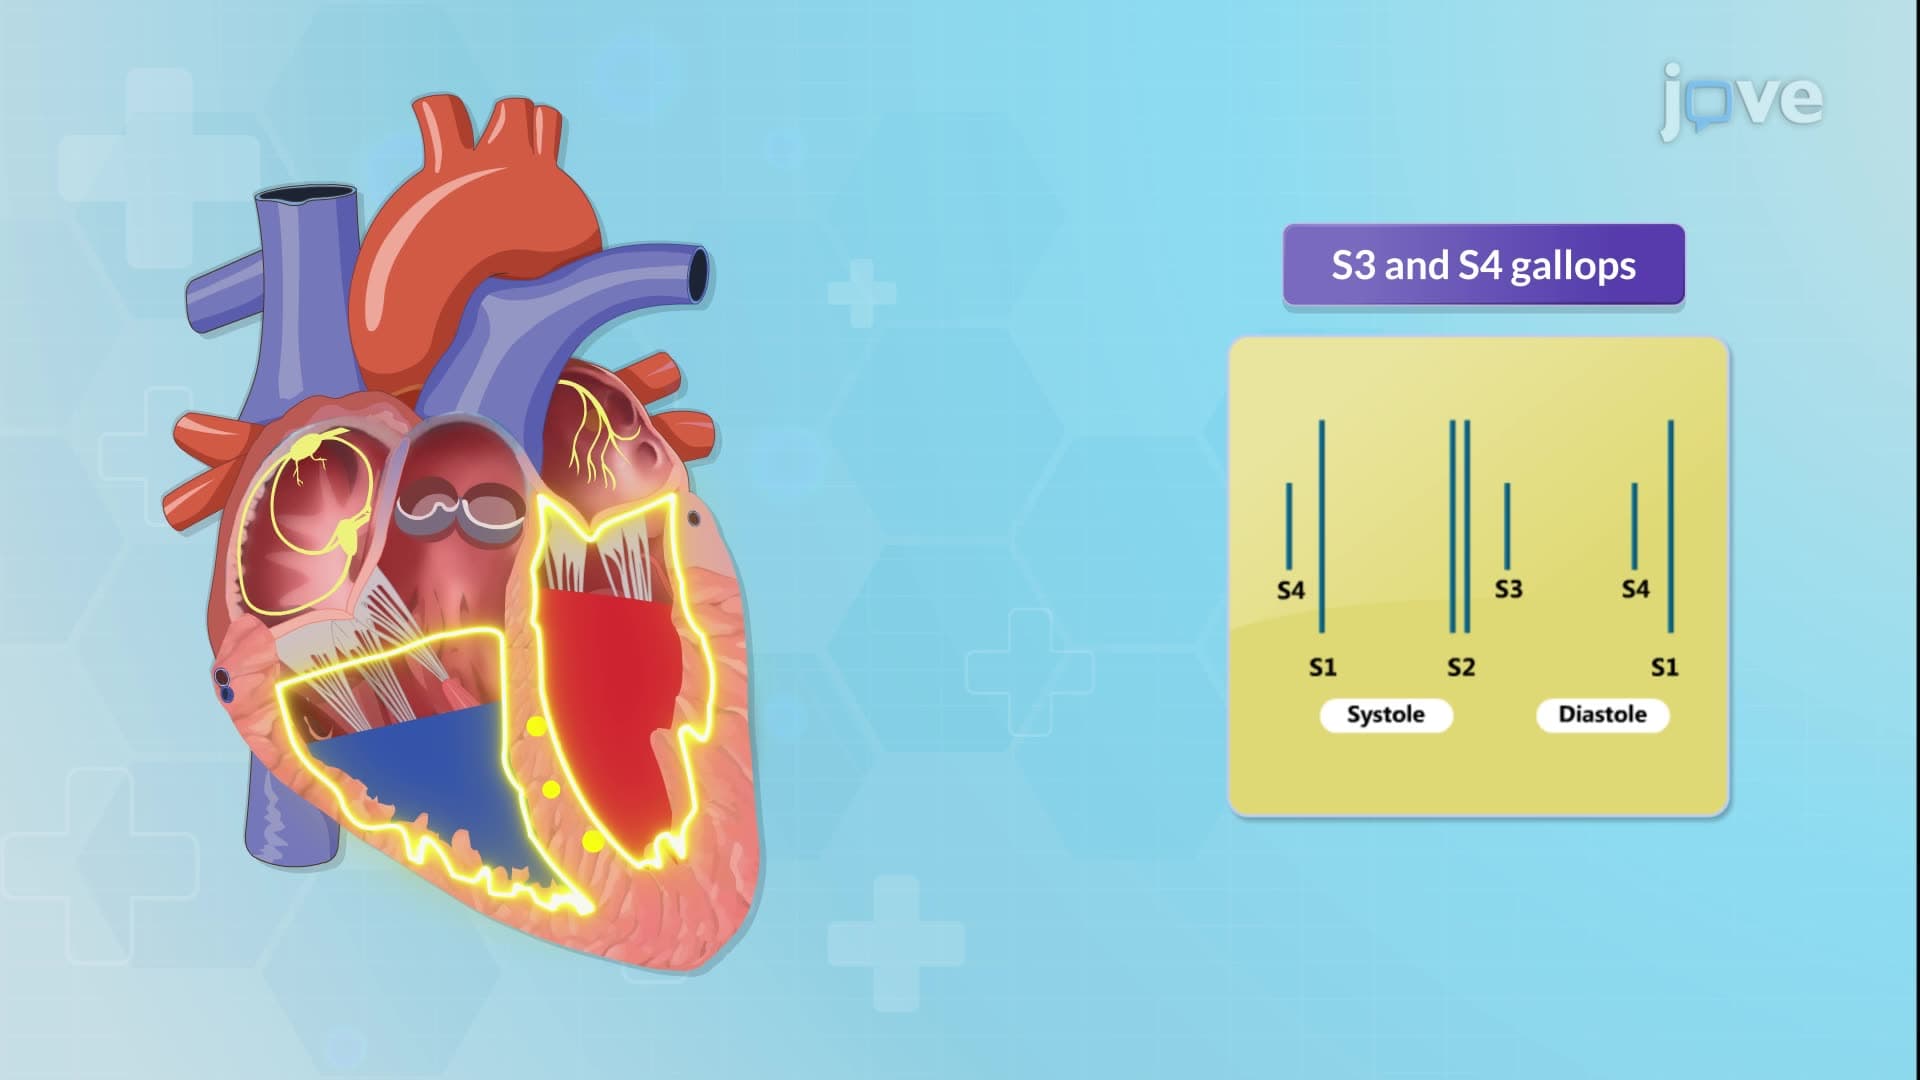
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops: