Related Experiment Video
Updated: Jun 26, 2025
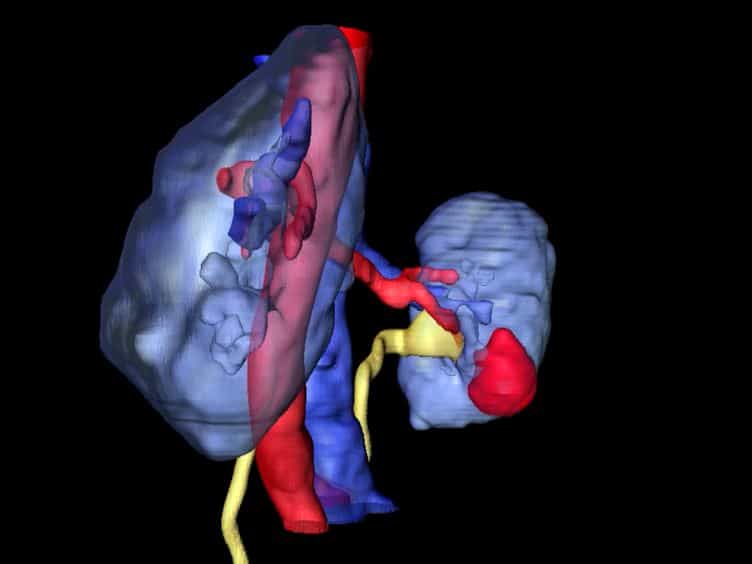

In Vivo, Percutaneous, Needle Based, Optical Coherence Tomography of Renal Masses
Published on: March 30, 2015
Parenchymal obliteration by renal masses: Functional and oncologic implications
Akira Kazama1, Carlos Munoz-Lopez2, Worapat Attawettayanon3
1Glickman Urological and Kidney Institute, Cleveland Clinic, Cleveland, OH; Department of Urology, Molecular Oncology, Niigata University Graduate School of Medical and Dental Sciences, Niigata, Japan.

Objectives:
Most renal tumors merely displace nephrons while others can obliterate parenchyma in an invasive manner. Substantial parenchymal volume replacement (PVR) by renal cell carcinoma (RCC) may have oncologic implications; however, studies regarding PVR remain limited. Our objective was to evaluate the oncologic implications associated with PVR using improved methodology including more accurate and objective tools.
Patients/Methods:
A total of 1,222 patients with non-metastatic renal tumors managed with partial nephrectomy (PN) or radical nephrectomy (RN) at Cleveland Clinic (2011-2014) with necessary studies were retrospectively evaluated. Parenchymal volume analysis via semiautomated software was used to estimate split renal function and preoperative parenchymal volumes. Using the contralateral kidney as a control, %PVR was defined: (parenchymal volumecontralateral-parenchymal volumeipsilateral) normalized by parenchymal volumecontralateral x100%. PVR was determined preoperatively and not altered by management. Patients were grouped by degree of PVR: minimal (<5%, N = 566), modest (5%-25%, N = 414), and prominent (≥25%, N = 142). Kaplan-Meier was used to evaluate survival outcomes relative to degree of PVR. Multivariable Cox-regression models evaluated predictors of recurrence-free survival (RFS).
Results:
Of 1,122 patients, 801 (71%) were selected for PN and 321 (29%) for RN. Overall, median tumor size was 3.1 cm and 6.8 cm for PN and RN, respectively, and median follow-up was 8.6 years. Median %PVR was 15% (IQR = 6%-29%) for patients selected for RN and negligible for those selected for PN. %PVR correlated inversely with preoperative ipsilateral GFR (r = -0.49, P < 0.01) and directly with advanced pathologic stage, high tumor grade, clear cell histology, and sarcomatoid features (all P < 0.01). PVR≥25% associated with shortened recurrence-free, cancer-specific, and overall survival (all P < 0.01). Male sex, ≥pT3a, tumor grade 4, positive surgical margins, and PVR≥25% independently associated with reduced RFS (all P < 0.02).
Conclusions:
Obliteration of normal parenchyma by RCC substantially impacts preoperative renal function and patient selection. Our data suggests that increased PVR is primarily driven by aggressive tumor characteristics and independently associates with reduced RFS, although further studies will be needed to substantiate our findings.
Insights
Significant parenchymal volume replacement (PVR) in renal cell carcinoma (RCC) is linked to poorer survival outcomes. Higher PVR, especially over 25%, independently predicts reduced recurrence-free survival in kidney cancer patients.
Area of Science:
- Urology
- Oncology
- Nephrology
Background:
- Renal tumors can invade and replace normal kidney tissue.
- Substantial parenchymal volume replacement (PVR) by renal cell carcinoma (RCC) may impact oncologic outcomes.
- Previous studies on PVR are limited, necessitating further investigation with advanced methodologies.
Purpose of the Study:
- To evaluate the oncologic implications of PVR in patients with non-metastatic renal tumors.
- To utilize accurate and objective tools for quantifying PVR.
- To assess the association between PVR and patient survival outcomes.
Main Methods:
- Retrospective evaluation of 1,222 patients with non-metastatic renal tumors treated with partial or radical nephrectomy.
- Semiautomated software used for parenchymal volume analysis to estimate split renal function and preoperative volumes.
- Calculation of %PVR using contralateral kidney as a control, with patients grouped by PVR degree: minimal (<5%), modest (5%-25%), and prominent (≥25%).
Main Results:
- PVR correlated inversely with preoperative ipsilateral GFR and directly with advanced pathologic stage, high tumor grade, clear cell histology, and sarcomatoid features.
- Prominent PVR (≥25%) was associated with shortened recurrence-free, cancer-specific, and overall survival.
- Male sex, ≥pT3a stage, tumor grade 4, positive surgical margins, and PVR≥25% were independent predictors of reduced recurrence-free survival.
Conclusions:
- Obliteration of normal renal parenchyma by RCC significantly affects preoperative renal function and influences patient selection.
- Increased PVR is associated with aggressive tumor characteristics.
- Higher PVR independently predicts reduced recurrence-free survival, warranting further investigation.


Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...
 01:10
Nephrons
 01:21
External Anatomy of the Kidney
The kidneys are located in the retroperitoneal space on either side of the vertebral column, protected posteriorly by the 11th and 12th ribs. The right kidney sits slightly lower than the left owing to the presence of the liver...