Related Experiment Video
Updated: Jun 26, 2025

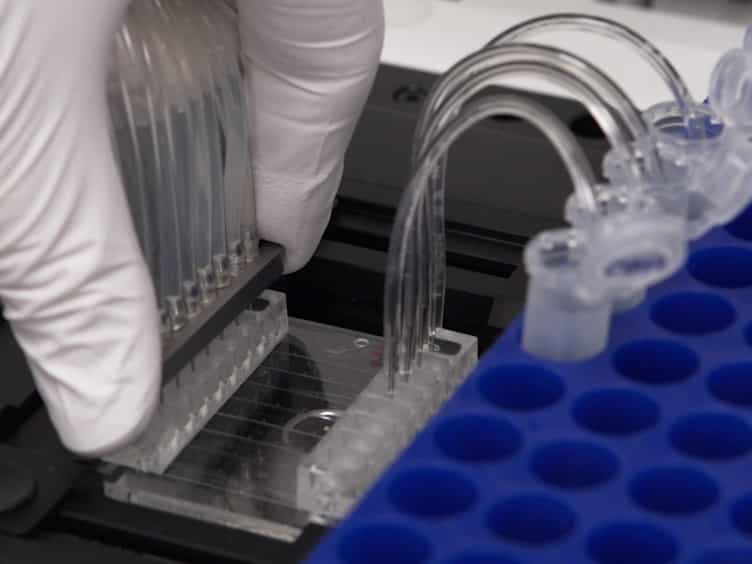
Microfluidics in Assessing Platelet Function
Published on: November 8, 2024
Is there a need for fresh frozen plasma and platelet transfusion in trauma patients receiving submassive transfusion?
Faisal Jehan1, Bardiya Zangbar1, Aryan Rafieezadeh1
1Surgery, Westchester Medical Center, Valhalla, New York, USA.

Background:
Blood transfusions have become a vital intervention in trauma care. There are limited data on the safety and effectiveness of submassive transfusion (SMT), that is defined as receiving less than 10 units packed red blood cells (PRBCs) in the first 24 hours. This study aimed to evaluate the efficacy and safety of fresh frozen plasma (FFP) and platelet transfusions in patients undergoing SMT.
Methods:
This is a retrospective cohort, reviewing the Trauma Quality Improvement Program database spanning 3 years (2016 to 2018). Adult patients aged 18 years and older who had received at least 1 unit of PRBC within 24 hours were included in the study. We used a multivariate regression model to analyze the cut-off units of combined resuscitation (CR) (which included PRBCs along with at least one unit of FFP and/or platelets) that leads to survival improvement. Patients were then stratified into two groups: those who received PRBC alone and those who received CR. Propensity score matching was performed in a 1:1 ratio.
Results:
The study included 85 234 patients. Based on the multivariate regression model, transfusion of more than 3 units of PRBC with at least 1 unit of FFP and/or platelets demonstrated improved mortality compared with PRBC alone. Among 66 319 patients requiring SMT and >3 units of PRBCs, 25 978 received PRBC alone, and 40 341 received CR. After propensity matching, 4215 patients were included in each group. Patients administered CR had a lower rate of complications (15% vs 26%), acute respiratory distress syndrome (3% vs 5%) and acute kidney injury (8% vs 11%). Rates of sepsis and venous thromboembolism were similar between the two groups. Multivariate regression analysis indicated that patients receiving 4 to 7 units of PRBC alone had significantly higher ORs for mortality than those receiving CR.
Conclusion:
Trauma patients requiring more than 3 units of PRBCs who received CR with FFP and platelets experienced improved survival and reduced complications.
Level Of Evidence:
Level III retrospective study.

Related Concept Videos
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:18
Structure and Function of Platelets
Platelets are continually replenished, circulating in the bloodstream for 9-12 days before being removed by phagocytes, primarily in the spleen. A microliter of circulating blood contains between 150,000 and 450,000...
 01:16
Clot Retraction and Fibrinolysis
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins