Related Experiment Video
Updated: May 3, 2026
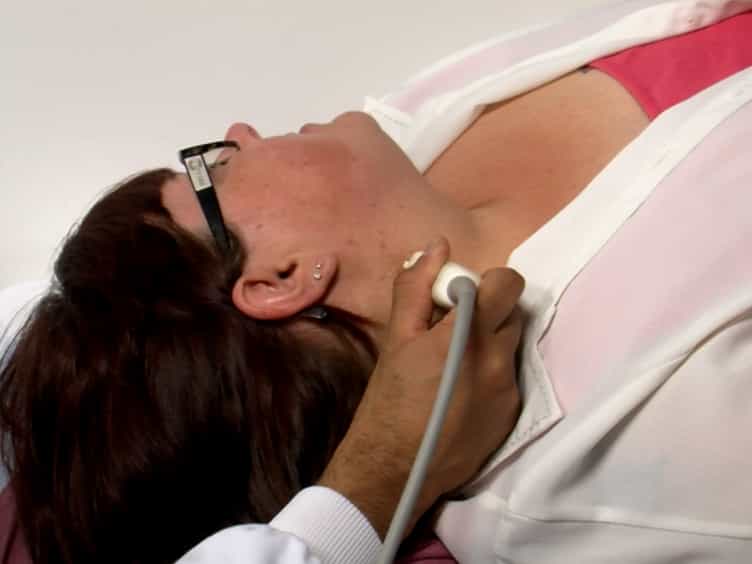

A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
Carotid intima media thickness in multiple sclerosis: A CLSA study
Ruth Ann Marrie1, Ronak Patel2, Stephen Allan Schaffer3
1Department of Internal Medicine, Max Rady College of Medicine, Rady Faculty of Health Sciences, University of Manitoba, Winnipeg, Can; Department of Community Health Sciences, Max Rady College of Medicine, Rady Faculty of Health Sciences, University of Manitoba, Winnipeg, Can.

Insights
People with multiple sclerosis (MS) do not show higher rates of subclinical atherosclerosis compared to controls. Cardiovascular risk scores, not MS itself, predict atherosclerosis in this population.
Area of Science:
- Neurology
- Cardiology
- Vascular Medicine
Background:
- Multiple sclerosis (MS) is linked to increased atherosclerotic disease incidence, including heart disease and stroke.
- Carotid intima media thickness (CIMT) serves as a key surrogate marker for atherosclerosis.
- This study investigates CIMT in MS patients compared to rheumatoid arthritis (RA) patients and healthy controls.
Purpose of the Study:
- To compare carotid intima media thickness (CIMT) between individuals with multiple sclerosis (MS) and those without MS.
- To assess subclinical atherosclerosis rates in MS patients.
- To determine if MS is an independent predictor of atherosclerosis beyond established cardiovascular risk factors.
Main Methods:
- Utilized data from the Canadian Longitudinal Study on Aging (CLSA) excluding participants with pre-existing vascular disease.
- Measured CIMT via carotid ultrasound in participants with MS, RA, and controls.
- Employed logistic regression, adjusting for Framingham Risk Score (FRS) and other covariates, to analyze associations between cohort membership and atherosclerosis (CIMT ≥75th percentile).
Main Results:
- No significant difference in average CIMT was found between MS, RA, and control groups.
- Cohort membership (MS, RA, controls) was not associated with subclinical atherosclerosis based on CIMT.
- A higher Framingham Risk Score (FRS) was significantly associated with increased odds of atherosclerosis.
Conclusions:
- Average CIMT does not differ between individuals with MS, RA, or neither condition.
- Subclinical atherosclerosis in MS patients is not elevated beyond predictions based on the FRS.
- Further research is required to elucidate mechanisms behind increased cardiovascular disease and stroke rates in MS.
Background:
People with multiple sclerosis (MS) have an increased incidence of atherosclerotic disease, including ischemic heart disease and stroke, compared to people without MS even after accounting for risk factors such as hypertension, dyslipidemia, diabetes and smoking. We compared carotid intima media thickness (CIMT), a surrogate of atherosclerosis, in people with MS and in two groups of people without MS (rheumatoid arthritis [RA]; all other participants).
Methods:
We used data from participants in the Canadian Longitudinal Study on Aging (CLSA) who did not have known vascular disease (ischemic heart disease, stroke, transient ischemic attack, peripheral vascular disease) and who underwent carotid ultrasound for assessment of CIMT. We selected participants with MS, RA and controls who did not have MS or RA. Using age and gender-stratified norms for average CIMT in the CLSA, we identified participants in each cohort with a CIMT ≥75th percentile (subclinical atherosclerosis). We also calculated ten-year level of cardiovascular risk using the Framingham Risk Score (FRS). We tested the association between cohort membership (MS, RA, controls) and atherosclerosis using logistic regression, adjusted for FRS, abdominal obesity, excess alcohol intake, education and elevated symptoms of depression. We adjusted all analyses for the stratified sampling design.
Results:
We included 78 participants with MS, 364 participants with RA and 13,891 controls. Overall, the average (SE) CIMT was 0.699 (0.002), and this did not differ between cohorts. Logistic regression analyses revealed that cohort membership was not associated with atherosclerosis based on the average CIMT in unadjusted or adjusted models. However, a 1-point higher FRS was associated with 1.032 (95 %CI: 1.021, 1.043) increased odds of atherosclerosis.
Conclusion:
Average CIMT does not differ between people with MS, people with RA and people without these diseases. Subclinical atherosclerosis as defined by a CIMT ≥75 % is not observed in people with MS at an increased rate beyond what FRS would predict. Further evaluation is needed to determine what mechanisms underlie the increased rates of cardiovascular disease and stroke in MS.


Related Concept Videos
 01:30
Atherosclerosis I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:19
Multiple Sclerosis l: Introduction